Related Experiment Video
Updated: Mar 17, 2026
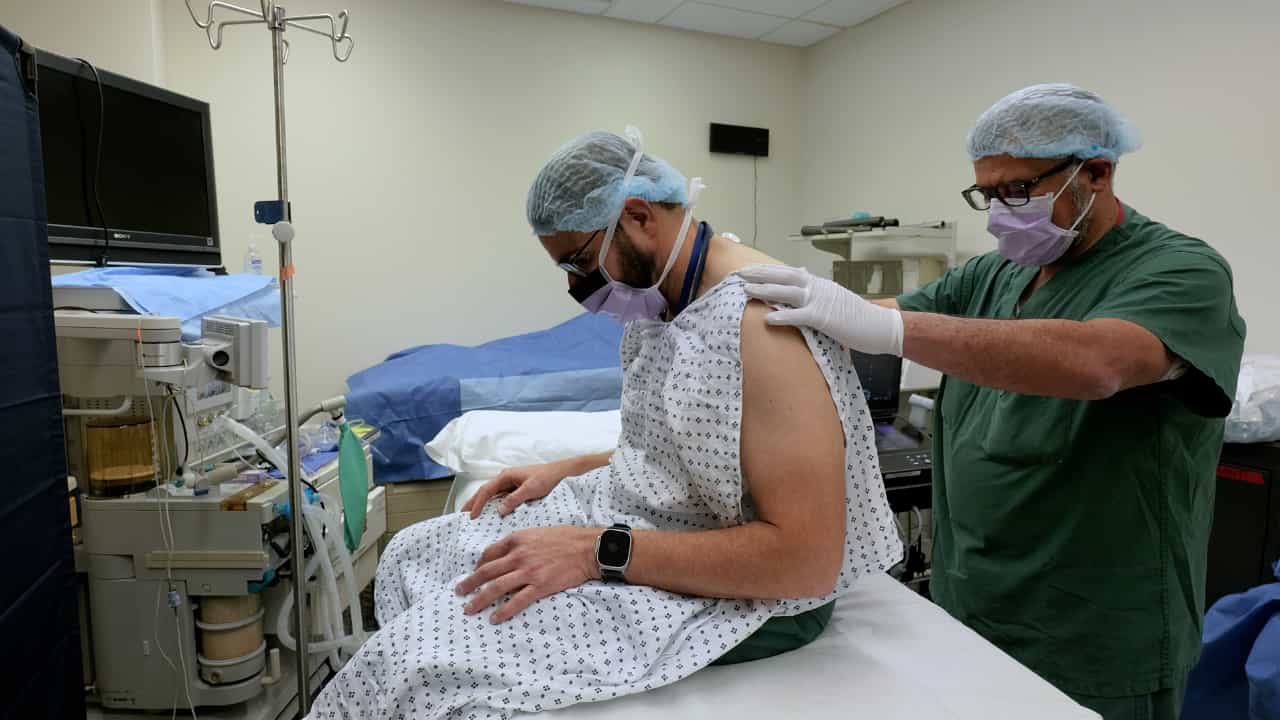

Author Spotlight: Enhancing Success of Ultrasound-Guided Neuraxial Anesthesia in Cases with Difficult Anatomy
Published on: January 31, 2025
Intravenous Bolus Phenylephrine and Intravenous Bolus Norepinephrine for Treatment of Maternal Hypotension in Spinal
Danish Jamal Ansari1, Manoj K Chaurasiya1, Manish Singh1
1Department of Anaesthesiology, King George's Medical University, Lucknow, IND.

Background A fall in maternal blood pressure is frequently encountered following spinal anesthesia for cesarean delivery. This hemodynamic disturbance primarily results from reduced venous return, leading to a decline in cardiac output and/or systemic vascular resistance. The primary objective of this study was to estimate the efficacy and safety of norepinephrine and phenylephrine for the treatment of maternal post-spinal hypotension during cesarean section. The secondary objective was to compare the hemodynamics and neonatal APGAR scores between the two vasopressors. Methodology This prospective, randomized trial included 72 parturients scheduled for cesarean section. Before the administration of spinal anesthesia, participants were allocated using computer-generated randomization into the following two groups: norepinephrine (Group A) and phenylephrine (Group B). Group A received an intravenous bolus of norepinephrine 4 μg (4 μg/mL), while Group B was administered an intravenous bolus of phenylephrine 50 μg (50 μg/mL). Both study drugs were prepared by dilution with normal saline. Results The mean systolic blood pressure showed a decline in both groups for up to the initial two minutes and a gradual elevation later. A significantly greater decline in heart rate was noted in the phenylephrine group (Group B) compared with the norepinephrine group (Group A) at multiple time points during observation. In addition, patients receiving phenylephrine required fewer rescue bolus doses than those receiving norepinephrine, with the difference reaching high statistical significance (p < 0.0001). Both groups showed no statistically significant difference (p = 0.3938) in neonatal outcome, assessed by the one-minute APGAR score. The majority of neonates in both groups had APGAR scores in the moderate range (4-6), accounting for 88.89% in Group A and 94.44% in Group B. There was a statistically insignificant difference in APGAR score in both groups (p = 0.3139) at five minutes, with 100% and 97.22% of patients falling under the reassuring category of score 7-9 in Group A and Group B, respectively. Conclusions An intermittent bolus of norepinephrine is as effective as an intermittent bolus of phenylephrine for the treatment of maternal hypotension in spinal anesthesia during cesarean section. However, the incidence of heart rate reduction was much higher with phenylephrine than with norepinephrine. The number of bolus doses required was higher with norepinephrine than with phenylephrine.
Background A fall in maternal blood pressure is frequently encountered following spinal anesthesia for cesarean delivery. This hemodynamic disturbance primarily results from reduced venous return, leading to a decline in cardiac output and/or systemic vascular resistance. The primary objective of this study was to estimate the efficacy and safety of norepinephrine and phenylephrine for the treatment of maternal post-spinal hypotension during cesarean section. The secondary objective was to compare the hemodynamics and neonatal APGAR scores between the two vasopressors. Methodology This prospective, randomized trial included 72 parturients scheduled for cesarean section. Before the administration of spinal anesthesia, participants were allocated using computer-generated randomization into the following two groups: norepinephrine (Group A) and phenylephrine (Group B). Group A received an intravenous bolus of norepinephrine 4 μg (4 μg/mL), while Group B was administered an intravenous bolus of phenylephrine 50 μg (50 μg/mL). Both study drugs were prepared by dilution with normal saline. Results The mean systolic blood pressure showed a decline in both groups for up to the initial two minutes and a gradual elevation later. A significantly greater decline in heart rate was noted in the phenylephrine group (Group B) compared with the norepinephrine group (Group A) at multiple time points during observation. In addition, patients receiving phenylephrine required fewer rescue bolus doses than those receiving norepinephrine, with the difference reaching high statistical significance (p < 0.0001). Both groups showed no statistically significant difference (p = 0.3938) in neonatal outcome, assessed by the one-minute APGAR score. The majority of neonates in both groups had APGAR scores in the moderate range (4-6), accounting for 88.89% in Group A and 94.44% in Group B. There was a statistically insignificant difference in APGAR score in both groups (p = 0.3139) at five minutes, with 100% and 97.22% of patients falling under the reassuring category of score 7-9 in Group A and Group B, respectively. Conclusions An intermittent bolus of norepinephrine is as effective as an intermittent bolus of phenylephrine for the treatment of maternal hypotension in spinal anesthesia during cesarean section. However, the incidence of heart rate reduction was much higher with phenylephrine than with norepinephrine. The number of bolus doses required was higher with norepinephrine than with phenylephrine.


Related Concept Videos
 01:29
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 01:24
Parenteral Anesthetics: Overview
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:22
Aneurysm IV: Nursing Management
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and...