Related Experiment Video
Updated: Mar 18, 2026
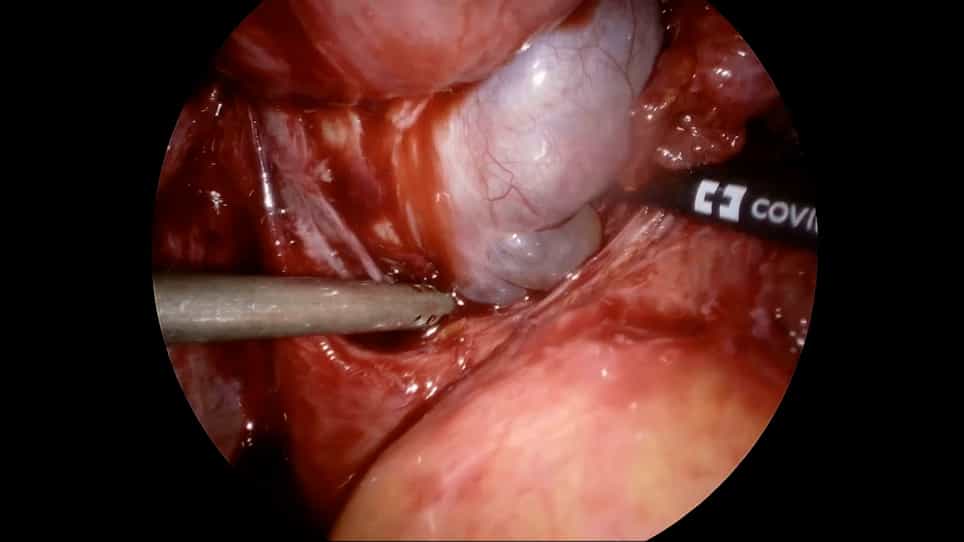

Surgical Techniques to Optimize Ovarian Reserve during Laparoscopic Cystectomy for Ovarian Endometrioma
Published on: January 22, 2022
A predictive nomogram for postoperative ovarian endometrioma recurrence in patients with congenital obstructive
Xiaotong Liu1,2, Ning Zhang1,2, Xuyin Zhang1,2
1Department of Gynecology, Obstetrics and Gynecology Hospital of Fudan University, Shanghai, China.

Objective:
This study aimed to develop a predictive model for ovarian endometrioma (OE) recurrence in patients with congenital obstructive Müllerian anomalies (OMAs) undergoing surgical intervention.
Methods:
This retrospective cohort study included 139 OMA patients with histologically confirmed ovarian endometrioma undergoing complete lesion excision and anatomical reconstruction between January 2013 and December 2020. A multivariable Cox regression analysis identified recurrence predictors; a nomogram was constructed and validated via time-dependent receiver operating characteristic curve (ROC), calibration curve, and decision curve analysis.
Results:
The mean surgical age of 139 patients was 20.70 ± 5.81 years. Over a mean follow-up of 80.8 months, 29.5% of patients experienced OE recurrence. Cumulative recurrence rates were 1.4% (24 months), 10.1% (36 months), 27.1% (60 months), and 34.4% (120 months). In a multivariate analysis, independent risk factors for endometrioma recurrence, such as preoperative hematometra >5 cm3 (hazard ratio [HR]: 2.650, 95%CI: 1.356-5.17, p = 0.004), rASRM score >40 (HR: 3.488, 95%CI: 1.252-9.709, p = 0.017), non-postoperative pregnancy (HR: 5.329, 95%CI: 1.399-20.307, p = 0.014), and hormonal treatment ≤30 months (HR: 3.563, 95%CI: 1.707-7.439, p = 0.001), and the other essential recurrent factor, surgical age, were all included in the nomogram. The nomogram showed strong discrimination (5-year AUC = 0.862, 10-year AUC = 0.808) and calibration, with decision curve analysis confirming clinical utility across probability thresholds. Internal validation via repeated K-fold cross-validation further showed robust model performance (5-year AUC = 0.864, 10-year AUC = 0.800).
Conclusion:
This model effectively stratifies OE recurrence risk in OMA patients post-surgery, guiding personalized management. Early surgical intervention may optimize endometrioma recurrence prevention to relieve Müllerian duct obstruction combined with prolonged postoperative medical suppression.