Related Experiment Video
Updated: May 10, 2026
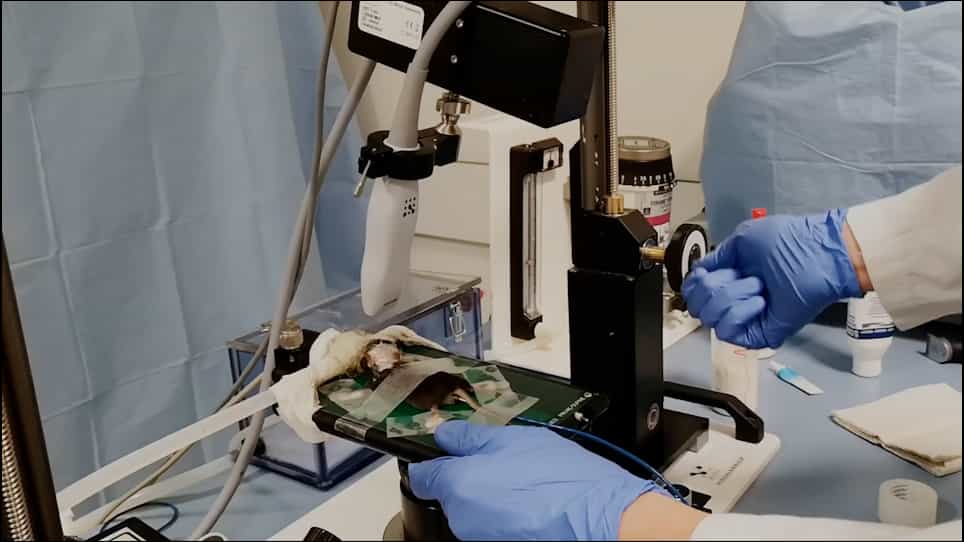

Analysis of Cerebral Vasospasm in a Murine Model of Subarachnoid Hemorrhage with High Frequency Transcranial Duplex Ultrasound
Published on: June 3, 2021
Sacral Dural Tears in Spontaneous Intracranial Hypotension: Imaging Phenotype and Treatment Outcomes in a Multicenter
Andrew L Callen1,2, Daniel Montes3, Timothy J Amrhein4
1From the Department of Radiology, Neuroradiology Section (A.L.C., D.M., D.B.), University of Colorado Anschutz Medical Campus, Aurora, Colorado andrew.callen@cuanschutz.edu.

Background And Purpose:
Sacral dural tears are an underrecognized cause of spontaneous intracranial hypotension, and their clinical behavior and response to treatment remain incompletely defined. We hypothesized that outcomes following epidural patching in sacral dural tears are driven primarily by disease chronicity and baseline imaging features, mirroring patterns observed in other spontaneous intracranial hypotension (SIH) leak subtypes, and are less dependent on procedural variables.
Materials And Methods:
We performed a multicenter retrospective cohort study of patients with SIH attributed to sacral dural tears who underwent epidural patching and had clinical and/or imaging follow-up. Of 61 identified patients, 54 met inclusion criteria. Clinical outcomes, brain and spine imaging findings, and procedural variables were analyzed. Univariate and multivariable logistic regression models were used to identify predictors of clinical and imaging outcomes. Myelographic techniques were compared for rates of precise leak localization.
Results:
The mean age was 37.8 years, and 85% of patients were women. Complete clinical improvement after patching occurred in 28 of 50 patients (56%), and complete resolution of sacral extradural CSF on follow-up spine MRI occurred in 17 of 37 patients (46%). Greater improvement in Bern score was independently associated with complete clinical improvement (OR 0.73; 95% CI, 0.54-0.99; P = .04) and showed a pattern toward imaging resolution. Unorganized baseline extradural CSF morphology predicted better clinical (P = .03) and imaging (P = .03) outcomes. Procedural variables, including injectate type, volume, and needle approach, were not associated with outcome. Dynamic CT myelography precisely localized the leak more frequently than digital subtraction myelography (75% vs 31%; P = .02). Eight patients underwent surgery, with mixed clinical and imaging outcomes.
Conclusions:
Epidural patching outcomes in sacral dural tears causing SIH are driven primarily by baseline imaging phenotype, disease stage, and intracranial imaging response rather than procedural technique. These findings support a morphology- and chronicity-aware approach to diagnosis and treatment and suggest that sacral dural tears represent a distinct SIH subtype with outcome patterns similar to other leak mechanisms.


