Related Experiment Video
Updated: May 6, 2026

A Novel Vertebral Stabilization Method for Producing Contusive Spinal Cord Injury
Published on: January 5, 2015
Dissecting the Enigma: insights from a retrospective study from India on congenital craniovertebral junction
Deepika Jain1, Tushar Rathod1, Yash Prakash Ved1
1Department of Orthopaedics, Seth G. S. Medical College and K. E. M. Hospital, Mumbai, India.

Study Design:
Single-center retrospective observational study.
Purpose:
This study aimed to analyze the associated anomalies, neurological manifestations, cord signal changes, surgical outcomes, and complications of congenital atlantoaxial instability (cAAI). Additionally, we summarized the evolving treatment options and provided technical notes relevant to anatomical variations encountered, outlining a stepwise approach for diagnosis/management.
Overview Of Literature:
AAI is predominantly congenital (approximately 73%) and often associated with various bony and vascular anomalies. These anatomical variations complicate the restoration of craniovertebral junction (CVJ) alignment and increase the risk of progressive myelopathy. Standard treatment involves reduction with or without release, followed by instrumentation. However, the optimal correction angle, extent of fixation, implant choice, surgical approach, and role of foramen magnum decompression have remained controversial.
Methods:
This single-center retrospective study from a tertiary care center analyzed data collected over 8 years (2015-2023). Patients with congenital AAI were included, whereas those with traumatic, inflammatory, or infective etiologies were excluded. Of 103 AAI patients evaluated, 25 (24.27%) had congenital etiology and 78 had acquired pathology. The primary outcome variables included radiological parameters (C1-C2 angle, posterior occipitocervical angle, atlantodens interval, space available for cord, and clivocanal angle) and clinical parameters assessing neurology and function.
Results:
Vascular (36%) and bony (92%) anomalies were frequent, with the most common being occipitoatlantal assimilation (68%). Moreover, 84% of the patients had cord signal intensity changes. An anomalous course and hypoplastic vertebral artery were observed in 16% of the patients each, while 7/25 patients (28%) had irreducible dislocations requiring anterior release. The average C1-C2 angle (C1C2A) correction was 20.6° (standard deviation [SD]=12.24; 95% confidence interval [CI], 15.812-25.408), whereas the average postoperative C1C2A was 22.36° (SD=5.68; CI, 20.133-24.587; p<0.05, paired t -test).
Conclusions:
cAAI poses additional challenges over other forms of AAI given its corresponding abnormal bony and vascular anatomy. Thorough planning and anatomical restoration are essential for satisfactory outcomes.
More Related Videos


Related Concept Videos
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...
 01:16
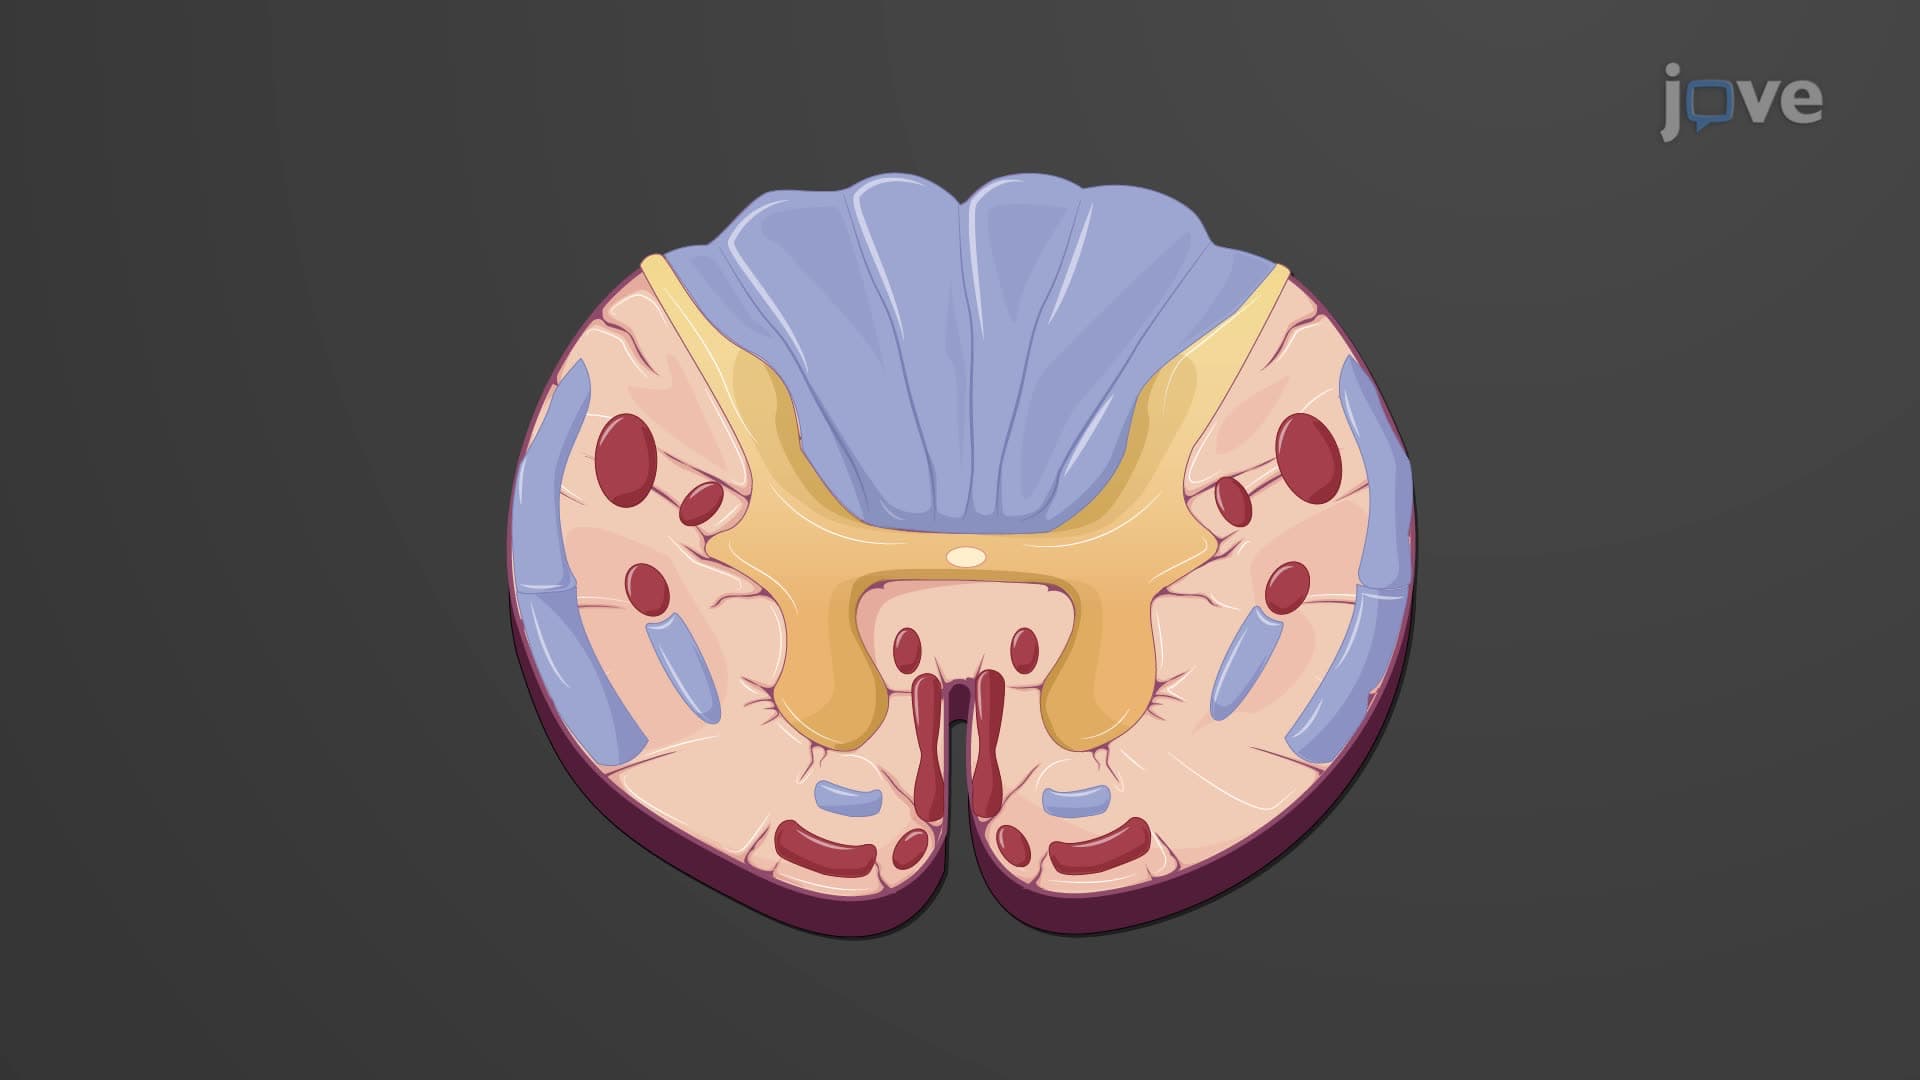
Spinal Cord: Cross-sectional Anatomy
Gray Matter and its Components
Central to the gray matter is...
 01:19
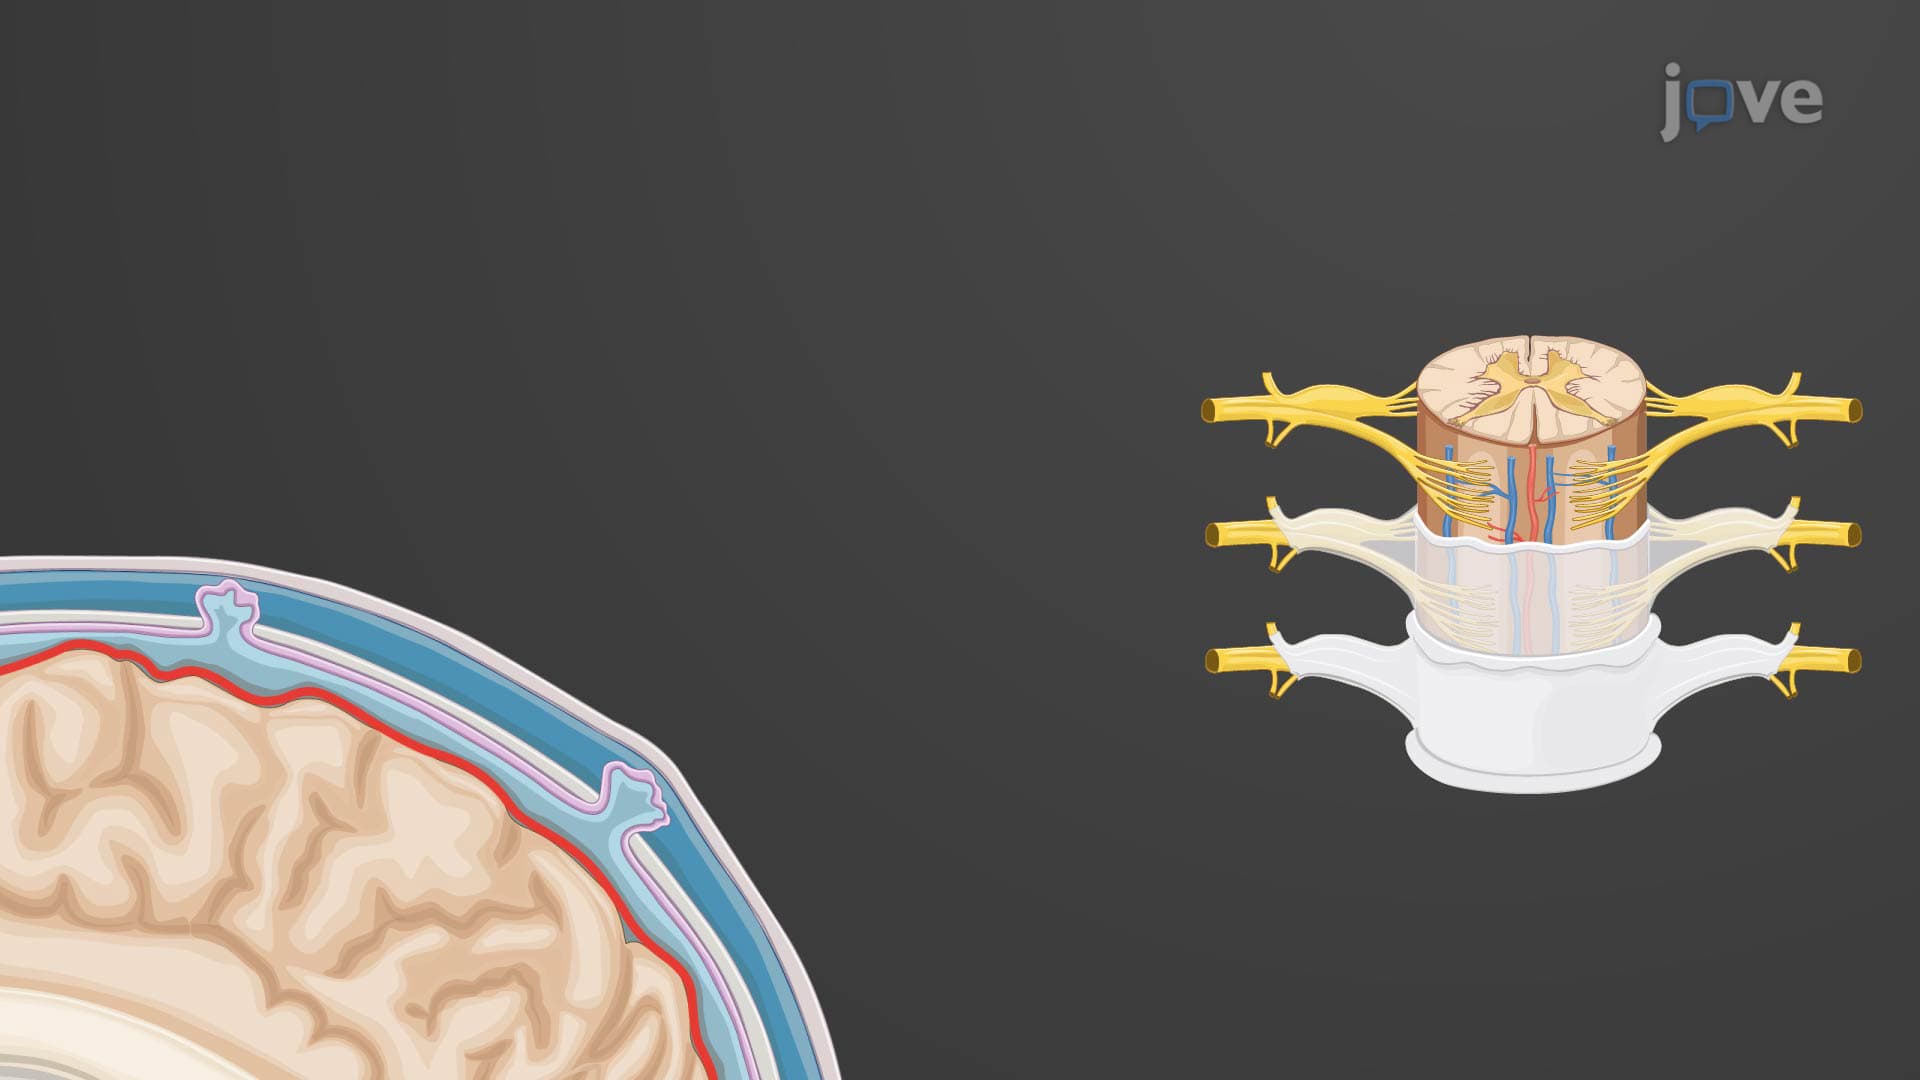
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies