Related Experiment Video
Updated: Mar 20, 2026
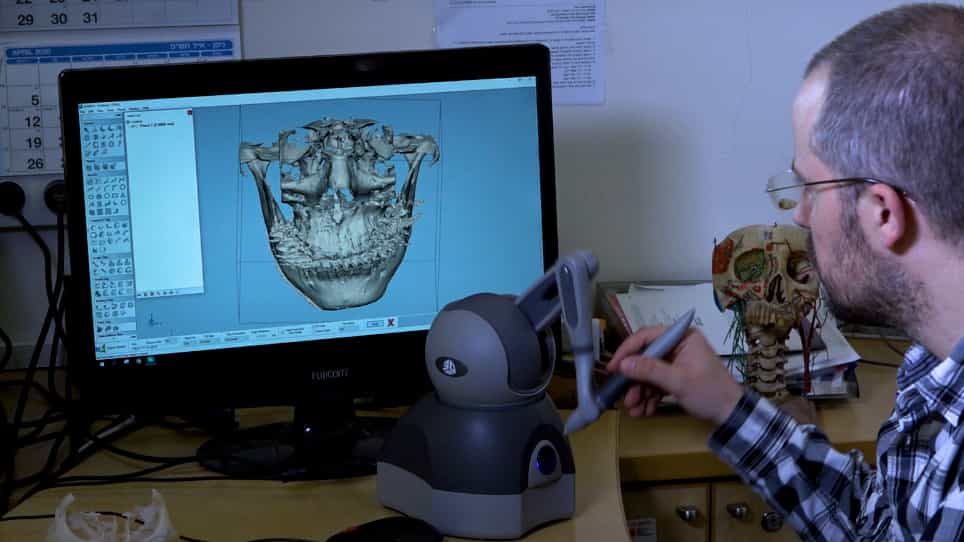

Treatment of Facial Deformities using 3D Planning and Printing of Patient-Specific Implants
Published on: May 23, 2020
Clinical Profile and Management of Maxillofacial Injuries in a Tertiary Care Hospital in North India: A Prospective
Marimuthu P1, Mohd Kalim Ansari1, Ghulam S Hashmi1
1Oral and Maxillofacial Surgery, Dr. Ziauddin Ahmad Dental College and Hospital, Aligarh Muslim University, Aligarh, IND.

Background:
Maxillofacial injuries significantly affect facial aesthetics, functional capacity, and quality of life. With the growing societal emphasis on physical appearance, a thorough understanding of the etiology, clinical presentation, and management of these injuries has become important.
Methods:
A two-year prospective study was conducted from December 31, 2020, to October 31, 2022 (22 months) at the Department of Oral and Maxillofacial Surgery, Dr. Ziauddin Ahmed Dental College, and the Emergency Department of Jawaharlal Nehru Medical College and Hospital, Aligarh, Uttar Pradesh. Patient demographics, etiology of injury, anatomical site, associated injuries, and treatment modalities were recorded. Data analysis was performed using IBM SPSS Statistics for Windows, Version 20.0 (Released 2011; IBM Corp., Armonk, NY, USA). As this was a descriptive study, results were summarized using descriptive statistics such as frequencies and percentages.
Results:
Among 400 patients, the mean age was 25.9 ± 1.99 years. Males constituted 80% (n = 320), yielding a 4:1 male-to-female ratio. The most affected age group was 21-30 years (41.2%, n = 165). Road traffic accidents (RTAs) were the predominant cause (77.7%, n = 275), followed by falls (18%, n = 44) and assaults (4%, n = 16). Middle-third fractures were most frequent (53%, n = 212), followed by mandibular fractures (30%, n = 120). Condylar fractures were the most common mandibular injury (28.2%, n = 113), while zygomaticomaxillary complex (ZMC) fractures were the most prevalent midfacial injuries (28%, n = 112). Head injuries (63.2%, n = 148) were the most common associated trauma. Open reduction and internal fixation (ORIF) was performed in 61.7% (n = 247) of cases.
Conclusion:
Maxillofacial injuries disproportionately occur in young male individuals, with RTAs (most notably those involving motorcycles and other two-wheeled vehicles) constituting the principal etiological factor. In clinical practice, this necessitates heightened preparedness for immediate airway stabilization, definitive management of maxillofacial fractures, and integration of multidisciplinary trauma protocols. Furthermore, active participation of clinicians in advocating protective helmet usage, reinforcing community-based injury prevention programs, and facilitating streamlined referral systems may contribute to decreasing trauma burden, improving treatment outcomes, and limiting long-term functional and aesthetic sequelae.

Related Concept Videos
 01:26
Tonsillitis II: Management
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:21
Tertiary Healthcare System
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:11
Secondary Healthcare System