Related Experiment Video
Updated: Mar 21, 2026
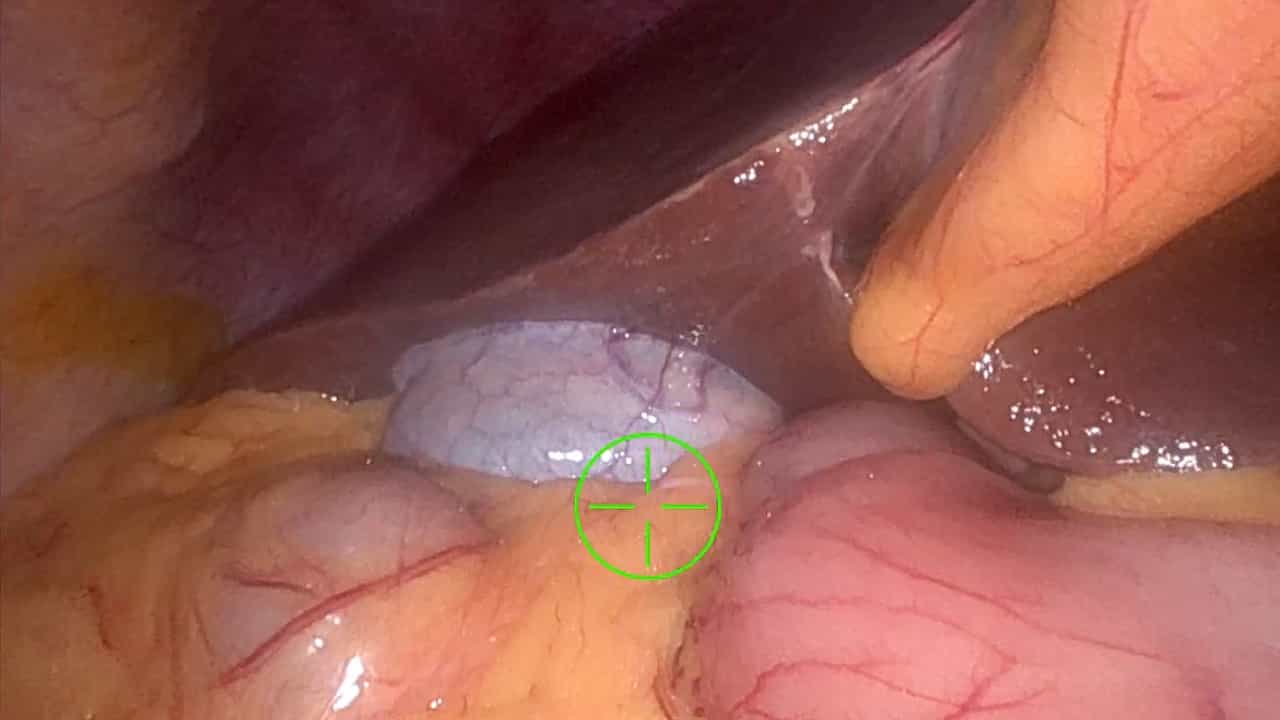
Application of Robot-assisted Pancreaticobiliary Junction Resection in Benign Duodenal Tumors
Published on: December 20, 2024
Gastric-Type Adenomas of the Nonampullary Duodenum: Reappraisal of Clinicopathological and Molecular Features and a
Hidetaka Yamamoto1,2, Shinichiro Kawatoko2,3, Yumi Oshiro4
1Department of Pathology and Oncology, Graduate School of Medicine, Dentistry and Pharmaceutical Sciences, Okayama University, Okayama.

Abstract:
Nonampullary duodenal neoplasms of gastric phenotype include pyloric gland adenoma, foveolar-type adenoma, and duodenal neoplasm of uncertain malignant potential. In addition, previously undesignated epithelial tumors have been observed in the duodenum. Their clinicopathological and molecular characteristics, as well as their pathologic classification, remain incompletely defined due to their rarity. In this study, we examined a total of 105 lesions from 100 patients for histopathologic and immunohistochemical features and analyzed genomic alterations in 20 representative cases using next-generation sequencing (NGS). All 105 cases were classified by a combination of growth pattern (exophytic, dumbbell, and inverted), nuclear grade (low- and high-grade), and predominant gastric phenotype (foveolar, pyloric gland, intermediate mucous cell, fundic gland, and not otherwise specified). Among the 105 tumors, 97 (92%) were low-grade and 8 (8%) were high-grade. Intratumoral heterogeneity in nuclear grade and/or immunophenotype was frequently observed. NGS revealed mutations in GNAS (75%), KRAS (45%), and APC (30%) across the histopathologic subgroups. In addition, 6 of 8 high-grade tumors (75%) harbored MDM2 gene amplification, which was associated with diffuse and strong expression of MDM2 protein and high Ki-67 index. In contrast, low-grade tumors exhibited rare MDM2 amplification (6%), and immunoreactivity for MDM2 and Ki-67 was generally sparse. The patients showed an extremely favorable prognosis without metastases, irrespective of nuclear grade. These findings suggest that nonampullary duodenal neoplasms of gastric phenotype can be reclassified as "gastric-type adenomas" based on excellent prognosis and common genetic alterations, albeit a wide spectrum of morphology and gastric phenotypic expression. MDM2 amplification may contribute to histologic progression.

Related Concept Videos
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds...
 01:27
Peptic Ulcer
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:27
Gastritis-I: Introduction and Types
Acute gastritis presents as a sudden inflammation triggered by various stressors to the stomach lining, such as exposure to corrosive agents, local irritants like aspirin and other NSAIDs, alcohol consumption, radiation therapy, physical trauma, severe burns, sepsis,...
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...