Lower-grade glioma imaging volumes and survival: a single-institution analysis of 90 patients after resection using intraoperative MRI
Related Experiment Video
Updated: Mar 21, 2026

Implementation of Minimally Invasive Brain Tumor Resection in Rodents for High Viability Tissue Collection
Published on: May 9, 2022
Jeffrey L Nadel1, Nicholas T Gamboa1, David Botros1
1Clinical Neurosciences Center, Department of Neurosurgery, University of Utah, 175 N. Medical Drive East, Salt Lake City, UT, 84132, USA.

Purpose:
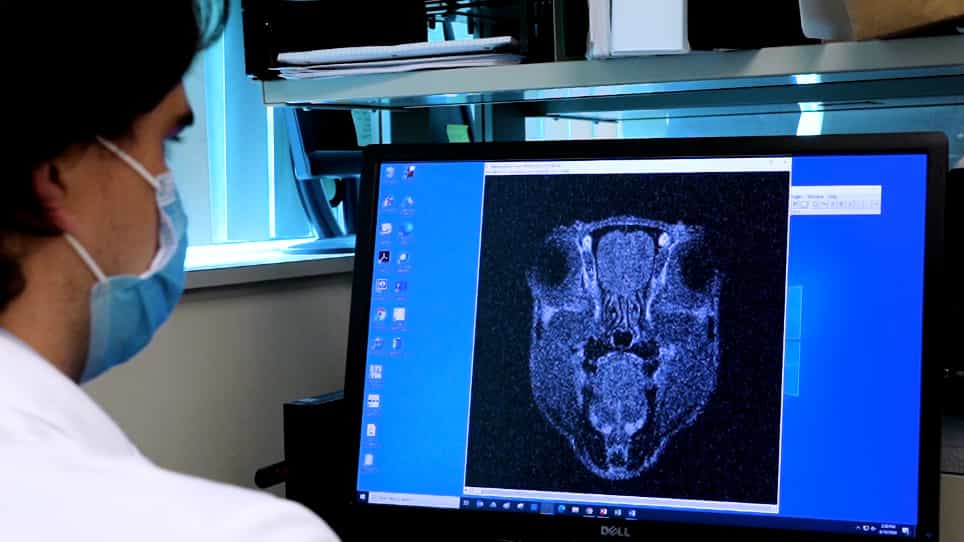
Extent of resection (EOR) and residual tumor volume (RTV) are key prognostic factors in lower-grade gliomas (LGGs). Intraoperative magnetic resonance imaging (iMRI) enables real-time assessment of tumor removal, but the survival relevance of sequential volumetric measures remains incompletely defined. This study evaluated the relationship between T2- and FLAIR-based imaging volumes, EOR, and survival in patients undergoing LGG resection with iMRI with long-term radiographic and clinical follow-up.
Methods:
We retrospectively reviewed 90 patients with WHO Grade 2-3 LGGs who underwent iMRI-guided resection between 2011 and 2023 at a single institution. Radiographic and clinical follow-up was tracked through 2025. Volumetric analyses were performed on preoperative, intraoperative, immediate postoperative, and three-month postoperative T2-weighted and FLAIR sequences. Associations between imaging volumes, EOR, and progression-free (PFS), malignant progression-free (mPFS), and overall (OS) survival were assessed using log-rank and multivariable Cox regression analyses, including subgroup analysis by isocitrate dehydrogenase (IDH) mutation status.
Results:
Median clinical and radiographic follow-up was 94.5 ± 34.8 months. Greater EOR correlated with longer survival across all metrics. In IDH-mutant tumors, FLAIR-based EOR was independently predictive of PFS (p ≤ 0.03), mPFS (p ≤ 0.02), and OS (p ≤ 0.02) on multivariable analysis. Additional resection after iMRI occurred in 55.6% of patients, with 90% yielding positive tumor margins, but did not independently improve survival.
Conclusion:
In LGG surgery accompanied by iMRI, greater EOR and smaller residual T2/FLAIR volumes predict longer survival, particularly among IDH-mutant tumors. The use of iMRI facilitates maximal safe resection.