Related Experiment Video
Updated: Jul 31, 2026

A Mobile Outside-in Technique of Transforaminal Lumbar Endoscopy for Lumbar Disc Herniations
Published on: August 7, 2018
Construction and Validation of a Nomogram Prediction Model for Recurrent Lumbar Disc Herniation After Percutaneous
Zeyu Jiang1, Ziying Cui2, Yiping Yang1
1Department of Orthopedics, The Affiliated Taizhou People's Hospital of Nanjing Medical University, Taizhou School of Clinical Medicine, Nanjing Medical University, Taizhou, Jiangsu, People's Republic of China.

Objective:
To identify risk factors for recurrent lumbar disc herniation (rLDH) after percutaneous endoscopic lumbar discectomy (PELD) and to develop and internally validate a nomogram.
Methods:
This retrospective, single-center study included 607 patients who underwent PELD between January 2018 and December 2023. Thirty candidate predictors were collected. Predictor selection was performed using least absolute shrinkage and selection operator (LASSO) regression, followed by multivariable logistic regression. A nomogram was constructed in accordance with the Transparent Reporting of a multivariable prediction model for Individual Prognosis Or Diagnosis (TRIPOD) recommendations. Discrimination was assessed using the area under the receiver operating characteristic curve (AUC); for a binary outcome, the concordance index (C-index) is numerically equivalent to the AUC and was therefore reported for internal validation. Calibration was evaluated using the Hosmer-Lemeshow test and calibration curves. Internal validation was conducted using bootstrap resampling (1,000 iterations) and 10-fold cross-validation. Decision curve analysis (DCA) was applied to evaluate clinical utility.
Results:
During follow-up, 70 of 607 patients (11.5%) developed rLDH. Seven independent predictors were identified: postoperative activity, body mass index (BMI), smoking, ligamentum flavum (LF) thickness, sagittal range of motion (sROM), Modic change, and Pfirrmann grade. The nomogram achieved an AUC of 0.793 (95% CI: 0.736-0.850) and good calibration (Hosmer-Lemeshow P = 0.668). Internal validation showed a C-index of 0.763 (95% CI: 0.682-0.844) in bootstrap resampling and 0.775 in 10-fold cross-validation. The calibration curve showed close alignment with the ideal curve. DCA demonstrated favorable clinical utility of the model.
Conclusion:
This internally validated nomogram integrates clinical and imaging predictors to provide individualized rLDH risk prediction after PELD. It may assist in identifying patients at higher risk of recurrence who could benefit from closer postoperative surveillance and individualized decision-making. External validation is warranted before broad clinical implementation.
Related Concept Videos
 01:29
Herniated Intervertebral Disc l: Introduction
 01:23
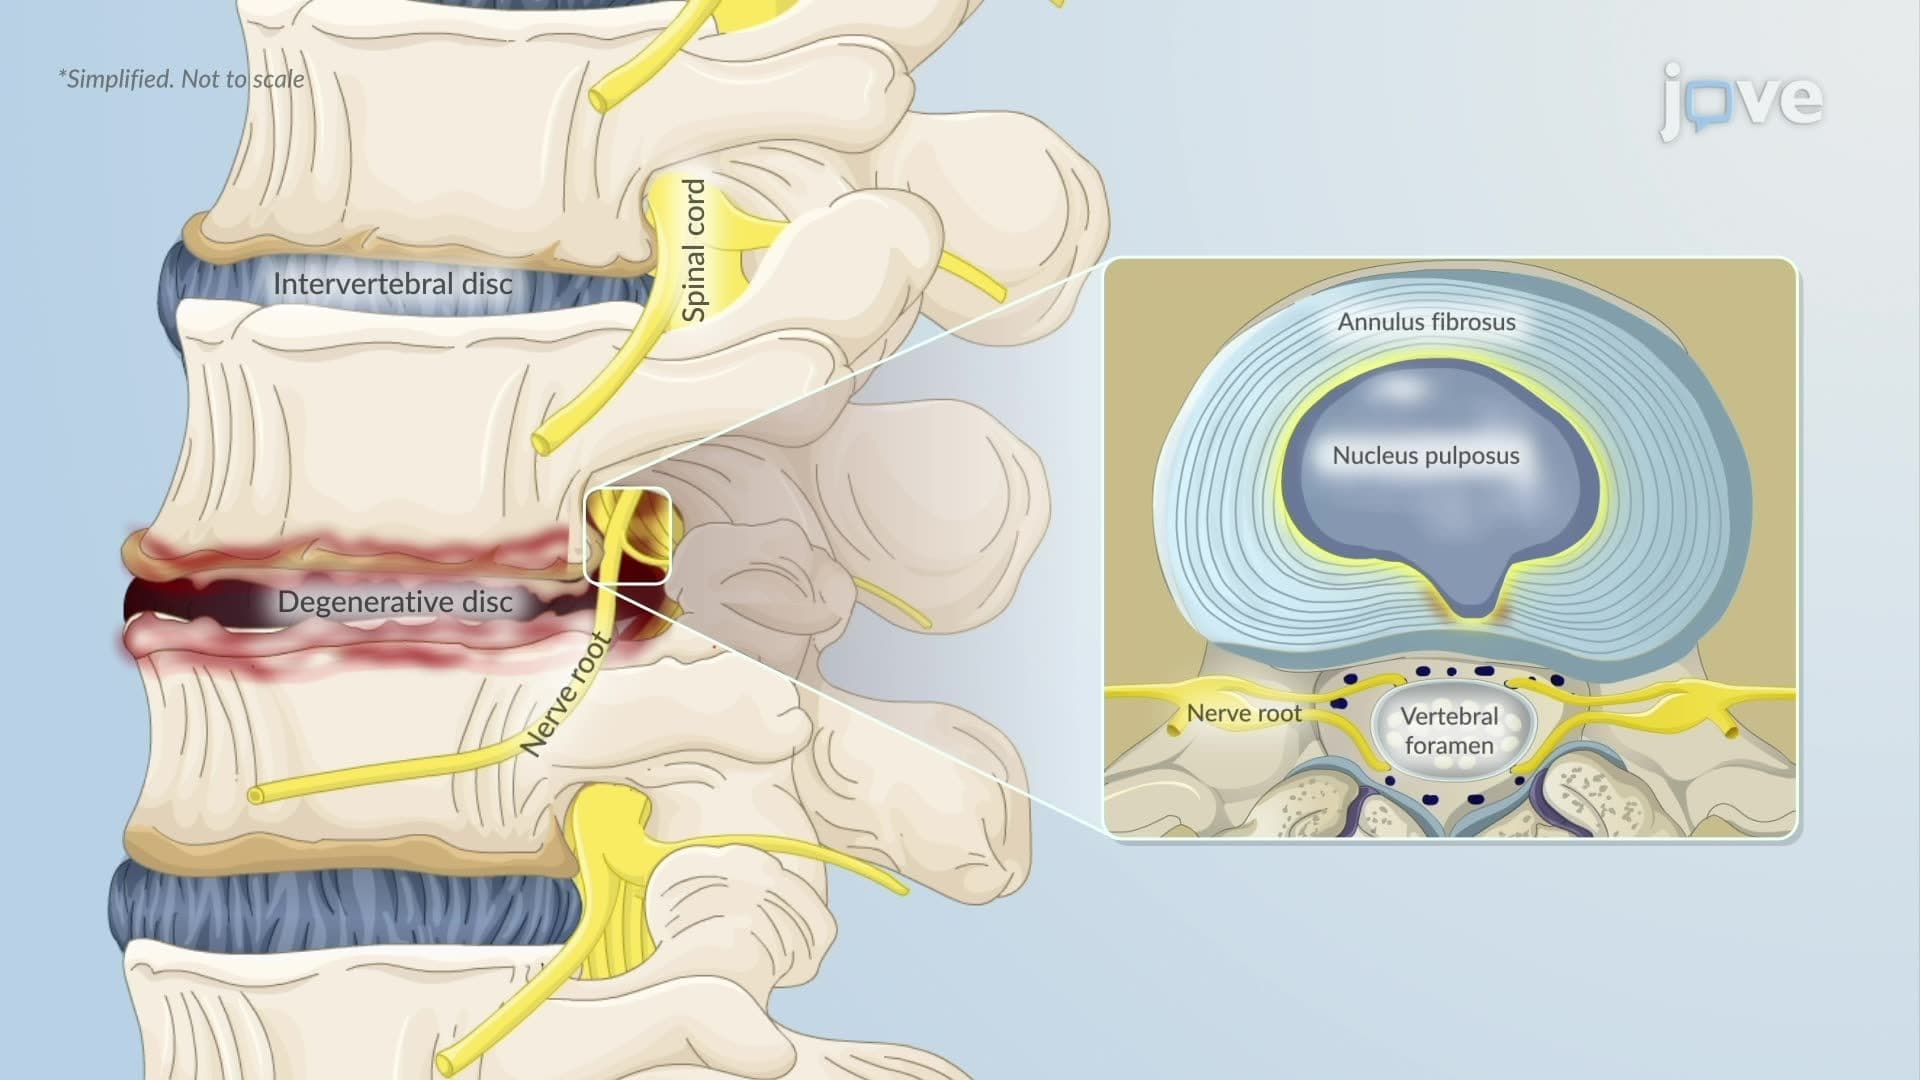
Degenerative Disc Disease ll: Pathophysiology