Related Experiment Video
Updated: Mar 21, 2026
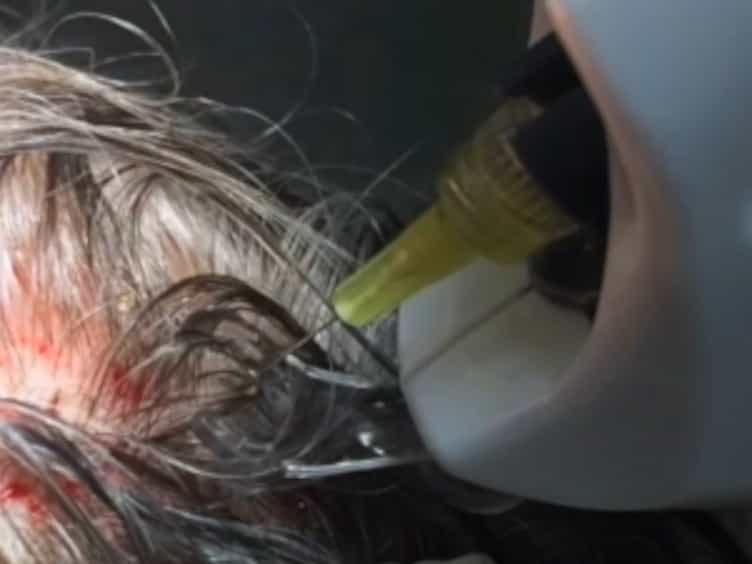
Mechanical and Controlled PRP Injections in Patients Affected by Androgenetic Alopecia
Published on: January 27, 2018
Perifollicular Inflammation and Fibrosis in Androgenetic Alopecia: Implications for Diagnosis and Treatment - A
Sanusi Umar1,2,3, Belinda H Tan4, Paul K Shitabata1,2,5
1Department of Medicine, University of California at Los Angeles, Los Angeles, CA, USA.

Introduction:
Androgenetic alopecia (AGA) is traditionally regarded as a noninflammatory, androgen-driven condition. Yet clinical and histologic evidence identifies a subset of patients with perifollicular infundibulo-isthmic lymphocytic infiltrates and fibrosis (PIILIF), a histopathologic pattern resembling early primary cicatricial alopecia (PCA). This study evaluates the clinical, histologic, and immunophenotypic features of PIILIF and their diagnostic and therapeutic implications.
Methods:
This retrospective study of 129 AGA patients drawn from a referral center, obtained trichoscopy-guided biopsies from balding and clinically non-alopecic scalp (cNAS). Histopathologic and immunohistochemical findings were correlated with clinical features and treatment outcomes. Patients with PIILIF received multimodal therapy targeting androgenic and inflammatory pathways. The cohort, from a specialty clinic, included both typical and treatment-resistant AGA.
Results:
PIILIF was identified in the cNAS of 81% of patients, particularly in those aged 44 or older, with Norwood stage ≥5, or with prior poor response to therapy. Histology showed CD117+ mast cells, perifollicular CD4-predominant lymphocytes and fibrosis in the infundibulo-isthmic unit. Combination therapy using dihydrotestosterone blockade plus anti-inflammatory agents modeled after PCA therapies, including tetracyclines, topical calcineurin inhibitors, and select phytoactive botanicals, yielded greater improvement than standard AGA treatment regimens alone. Overall, 67% improved, and 2% had suboptimal outcomes (p < 0.0001). These findings support an AGA-PIILIF continuum that may include fibrosing alopecia in a pattern distribution.
Conclusion:
PIILIF represents an under‑recognized inflammatory endotype within AGA that may account for treatment resistance in some patients. Early biopsy can confirm the diagnosis, and therapy targeting hormonal and immune pathways may improve outcomes. Routine trichoscopy with a low threshold to biopsy perifollicularly abnormal units showing mild erythema, scale, or hyperpigmented collars can guide care, particularly in treatment resistant or equivocal cases. The broader systemic implications of this inflammatory signature merit further investigation.


Related Concept Videos
 01:20
Folliculogenesis
 01:06
Multipotency and Niche of Bulge Stem Cell
 01:20
Accessory Structures of the Skin: Hair Growth and Types
 01:27
Acne Infection
 01:23
Skin Diseases and Disorders
Gram-positive Staphylococcus spp. and Streptococcus spp. are responsible for many of the most common skin infections. However, many...
 01:21
Accessory Structures of the Skin: Sebaceous Glands
These glands that produce the oils on the skin and hair are holocrine glands. The mature...