Related Experiment Video
Updated: Mar 21, 2026
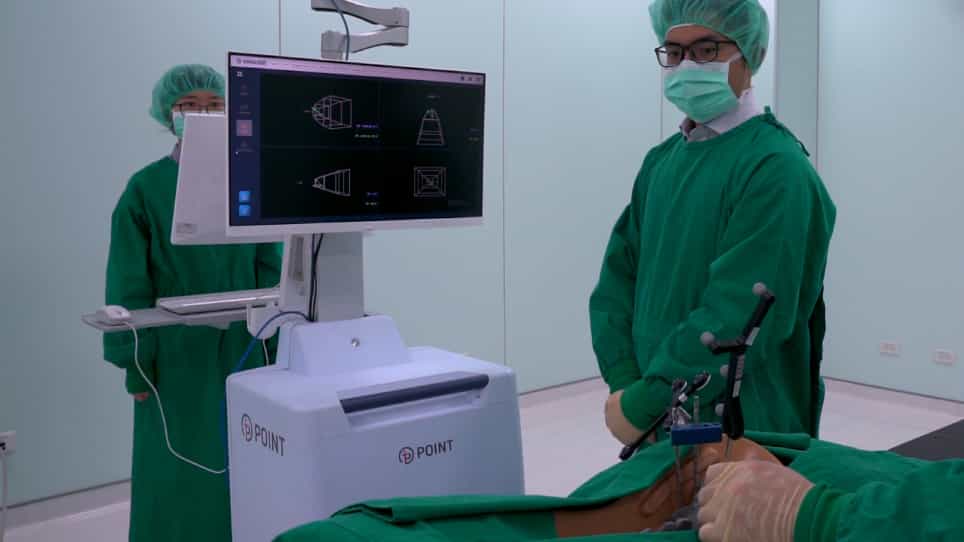

A Spine Robotic-Assisted Navigation System for Pedicle Screw Placement
Published on: May 11, 2020
Advances in Stereotactic Navigation for Primary Spine and Pelvis Tumor Resection and Reconstruction: A Systematic
Tejas Subramanian1,2, Alexander R Oles3, George Li4
1Department of Orthopedic Surgery and Rehabilitation Medicine, University of Chicago, IL, USA.

Background:
Primary spine/pelvic tumors are aggressive, and en bloc resection is often essential. While stereotactic navigation is increasingly used for instrumentation in spine surgery, its specific role in tumor resection remains incompletely defined.
Purpose:
We sought to describe (1) reported rates of achieving negative margins, (2) local recurrence, (3) complications attributed to navigation, and (4) comparative outcomes from studies involving nonnavigated controls.
Methods:
We conducted a systematic review according to preferred reporting items for systematic reviews and meta-analysis guidelines. Databases were queried for studies investigating the use of stereotactic navigation in primary spine/pelvic tumor surgery. Outcomes including surgical margin status, local recurrence, and complications were extracted and qualitatively synthesized using a best-evidence approach.
Results:
Twenty-one studies with 240 patients were included. The mean patient age was 46 years with follow-up of 33.4 months. Tumors were most often located in the sacrum/pelvis (81.3%), followed by the thoracic (8.3%), cervical (5.8%), and lumbar spine (4.6%). Chordoma (31.7%) and chondrosarcoma (27.1%) were the most frequently reported types. Negative surgical margins were achieved in 88.3% of cases. Local recurrence was reported in 16% of patients, with the highest observed in chondrosarcoma (32.4%). Complications occurred in 30.3% of patients; however, only 1% (2 cases) were attributed to navigation use. Two comparative studies examining navigated versus nonnavigated cohorts suggested improved bony margins and lower recurrence risk with navigation.
Conclusion:
Early studies suggest that stereotactic navigation may be a feasible and safe adjunct for the resection of primary spine/pelvic tumors, particularly in achieving adequate bony margins. However, the current evidence is limited to small retrospective studies with heterogeneity in methodology, tumor type, and follow-up.
Level Of Evidence:
Level IV: Systematic review of level-III and level-IV studies.
Insights
Stereotactic navigation may improve surgical outcomes for primary spine/pelvic tumors by enhancing negative margins and reducing recurrence. While generally safe, evidence is limited by study heterogeneity.
Area of Science:
- Neurosurgery
- Orthopedic Oncology
- Surgical Navigation
Background:
- Primary spine and pelvic tumors are aggressive, necessitating en bloc resection.
- Stereotactic navigation is used in spine surgery, but its role in tumor resection is not fully defined.
Purpose of the Study:
- To assess negative margin rates, local recurrence, and navigation-related complications in primary spine/pelvic tumor surgery.
- To compare outcomes of navigated versus nonnavigated tumor resections.
Main Methods:
- Systematic review of studies using stereotactic navigation for primary spine/pelvic tumor surgery.
- Qualitative synthesis of outcomes including margin status, local recurrence, and complications.
- Best-evidence approach applied to extracted data.
Main Results:
- 88.3% of 240 patients achieved negative margins; 16% experienced local recurrence (highest in chondrosarcoma).
- 30.3% of patients had complications, with only 1% attributed to navigation.
- Two comparative studies suggested improved bony margins and lower recurrence with navigation.
Conclusions:
- Stereotactic navigation appears feasible and safe for primary spine/pelvic tumor resection, potentially improving bony margins.
- Current evidence is limited by small, heterogeneous retrospective studies.