Related Experiment Video
Updated: Mar 21, 2026
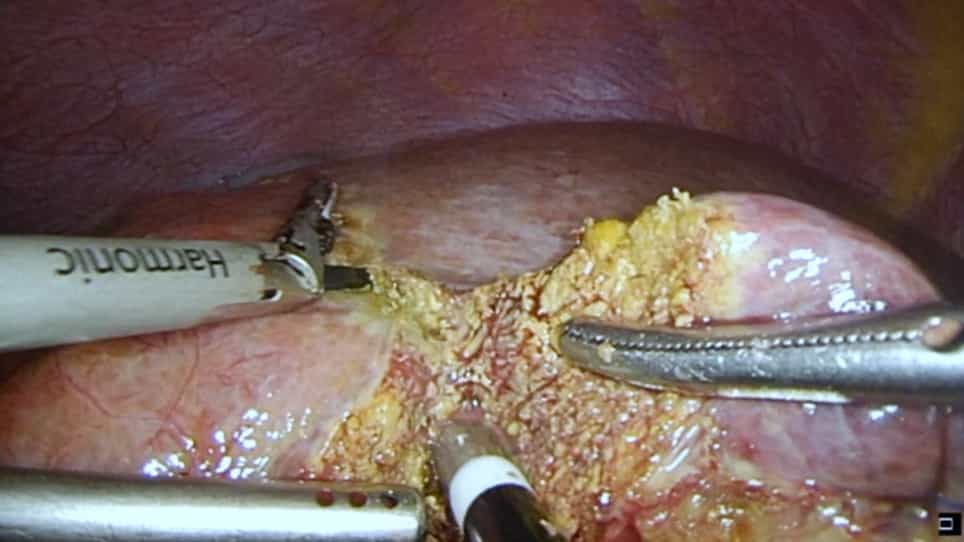

Application of Hemostatic Devices in Laparoscopic Hepatectomy
Published on: April 19, 2022
Hepatocellular Cancer Recurrence After Liver Transplantation With and Without the Use of Intraoperative Blood Salvage
Elise V Butler1,2, Jacqueline L Robson1,2, Stephanie Ponsonby3
1From the Department of Anaesthesia, Royal Prince Alfred Hospital, Sydney, New South Wales, Australia.

Background:
Intraoperative blood salvage (IBS) and autotransfusion have been widely implemented to minimize allogenic blood transfusion in major surgery. Despite published literature, controversy exists around its use in liver transplantation (LT) for patients with hepatocellular carcinoma (HCC) due to concern for oncological recurrence.
Methods:
We retrospectively studied adults with HCC who underwent deceased donor LT at a single LT center in Australia (August 2007-July 2020), comparing those who received IBS and autotransfusion with those who did not. Leukodepletion filters were not used. The primary outcome was time to HCC recurrence. The secondary outcomes were HCC recurrence-free survival and overall survival post-LT.
Results:
A total of 245 patients having concurrent LT and HCC were analyzed. Of these, 167 received IBS and 78 did not. HCC recurrence occurred in 22/245 (9.0%) after a median of 20 months (IQR 13.5-24.5). For the primary outcome, IBS and autotransfusion was not associated with a decrease in time to HCC recurrence on unadjusted analysis (hazard ratio [HR] 0.80, 95% confidence interval [CI] 0.34-1.92; P = .62). Independent predictors of time to HCC recurrence were: hepatitis C (adjusted HR [aHR] 3.57, 95% CI, 1.03-12.4, P = .04), number of HCCs (aHR 1.17 per lesion increase, 95% CI, 1.06-1.30, P < .01), higher alpha-fetal protein levels (aHR 1.002 per kIU/L increase, 95% CI, 1.0003-1.003, P = .01), and microvascular invasion (aHR 3.27, 95% CI, 1.26-8.50, P = .01). After adjusting for these confounders, there remained no relationship between IBS and autotransfusion and time to HCC recurrence (aHR 0.57, 95% CI, 0.23-1.44, P = .24). For the secondary outcomes, IBS and autotransfusion was not a predictor of HCC recurrence-free survival (aHR 0.75, 95% CI, 0.39-1.42, P = .38) or overall survival (aHR 0.68, 95% CI, 0.35-1.33, P = .26) on multivariable analysis.
Conclusions:
In this single-center study, IBS and autotransfusion during LT in patients with concurrent HCC was not associated with an increased risk of recurrence. No unexpected risk factors for HCC recurrence after LT were identified. This study provides further evidence to confirm the safety of IBS in LT for HCC without the use of leukodepletion filters.
More Related Videos
 08:15
A Hepatocellular Cancer Patient-Derived Organoid Xenograft Model to Investigate Impact of Liver Regeneration on Tumor Growth
Published on: February 2, 2024
 05:25
Author Spotlight: Exploring Cold Ischemia and Warm Reperfusion Injury in Fatty Liver Transplantation
Published on: December 1, 2023