Related Experiment Video
Updated: Jun 19, 2026
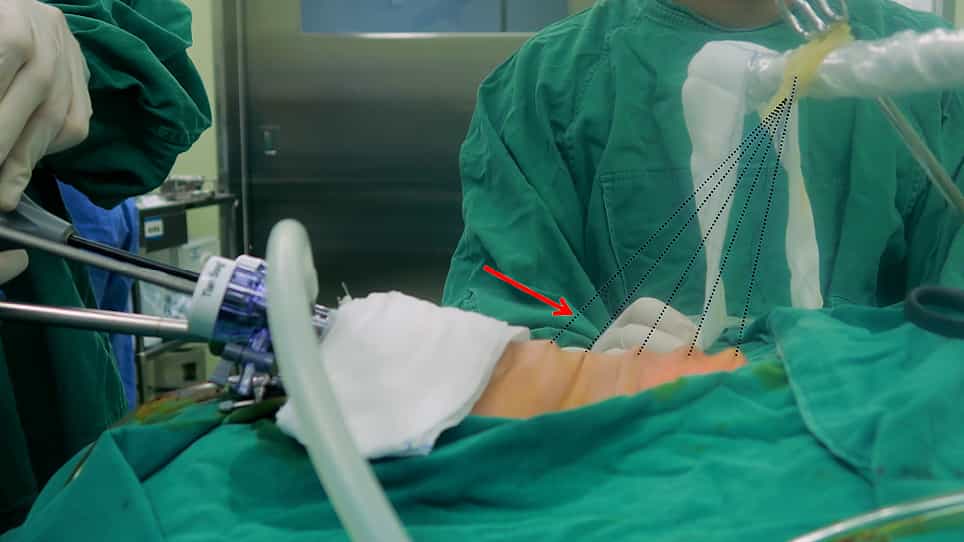

Transoral Endoscopic Thyroidectomy Vestibular Approach for Thyroid Lobectomy
Published on: May 12, 2023
From Lobectomy to Completion Thyroidectomy: A Cohort Study and Systematic Review
Idit Tessler1,2, Tzahi Yamin2, Liroy Caracucli1
1Department of Otolaryngology-Head and Neck Surgery, Sheba Medical Center, Ramat Gan, Israel.

Introduction:
The suggested management of thyroid cancer has been revised in the 2015 American Thyroid Association Management Guidelines, suggesting thyroid lobectomy alone for low-risk thyroid cancer. However, precise patient selection is essential to identify who may need completion thyroidectomy (CT), avoiding the burden of a second surgery. Here, we aimed to evaluate contemporary rates and indications for completion thyroidectomy following initial lobectomy, in light of evolving clinical guidelines, to better identify patients at risk and improve preoperative decision-making.
Methods:
We perform a retrospective cohort study and a systematic literature review. The original cohort includes patients who underwent CT for thyroid cancer from 2017 to 2022. Medical records were reviewed for demographics, sonography, cytology, pathology (malignancy type and aggressive features), CT indications, surgical intervals, and complications. In addition, a systematic literature review was performed and reported according to the PRISMA guidelines, collecting data on CT rates and indications.
Results:
In our institutional cohort (n = 54), 37% patients underwent completion thyroidectomy following initial lobectomy. The average time between the initial and completion surgeries was 3.75 ± 3.8 months. The systematic review included 30 studies comprising 23,899 patients who initially underwent lobectomy. The pooled weighted mean rate of completion thyroidectomy was 19.2% (range: 4.9%-94.6%). When reported (11 articles, 36.7%), the leading indications for completion surgery were aggressive histologic variants (158, 25.4%) followed by lymph node metastasis (143, 23%) and ETE (109, 17.5%). In a subgroup analysis, studies that specified tumour sizes of ≥1 cm or focused on the 1-4 cm range (n = 14) had a significantly higher mean CT rate of 45%, compared to studies without clearly defined tumour size (n = 16; mean CT rate: 16.1%; p < 0.001).
Conclusions:
Completion thyroidectomy is performed in a significant minority of patients following initial lobectomy, most often due to adverse pathological features identified postoperatively. Our findings highlight the need for improved preoperative risk assessment and patient selection, particularly as guideline-endorsed lobectomy becomes more common.
Related Concept Videos
 01:23
The Thyroid Gland
The follicles have a central cavity lined by simple cuboidal to squamous epithelial cells called follicular cells. These cells produce the glycoprotein...
 01:20
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
 01:25
Hyperthyroidism I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology
 01:23
Hypothyroidism II: Pathophysiology