Related Experiment Video
Updated: Mar 24, 2026
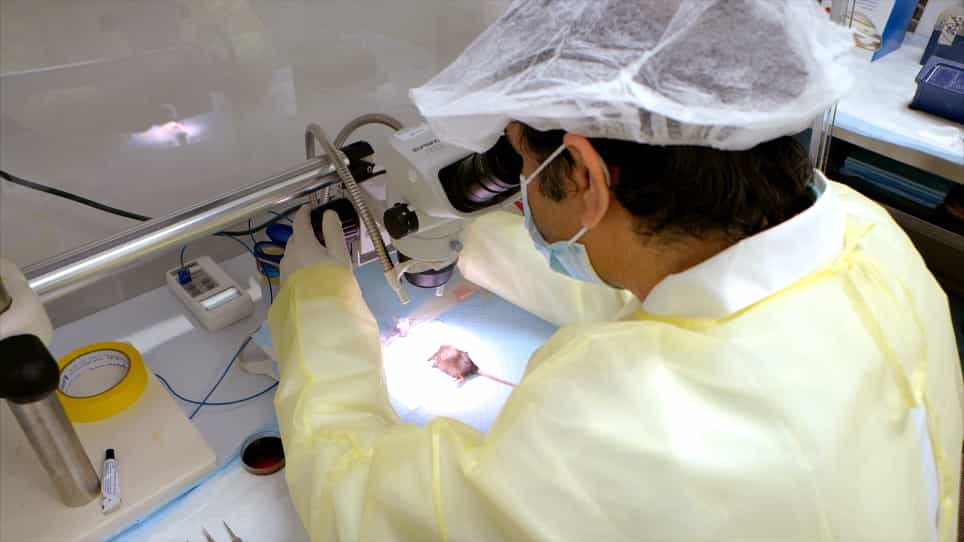

A Model for Encephalomyosynangiosis Treatment after Middle Cerebral Artery Occlusion-Induced Stroke in Mice
Published on: June 22, 2022
Mode of Birth and Stroke Risk After Childbirth Among Women With Moyamoya Disease
Jong Hun Kim1, Kwan Heup Song2, Man Young Park3
1Department of Neurology, Korea University Ansan Hospital, Ansan, Republic of Korea.

Importance:
There is limited large-scale evidence to guide the optimal mode of birth for patients with moyamoya disease (MMD).
Objective:
To evaluate whether the mode of birth (cesarean vs vaginal) is associated with stroke risk after childbirth for women with MMD.
Design, Setting, And Participants:
This cohort study evaluated stroke outcomes up to 3 years after childbirth. A nationwide, population-based analysis was performed using data from the Health Insurance Review and Assessment Service of South Korea. Individuals with MMD from January 1, 2002, to December 31, 2023 were identified. Among 31 750 patients, those with birth-related procedure codes were selected. The study population was restricted to women aged 19 to 49 years, and those with a diagnosis of malignant neoplasm within 3 years before the index date (date of childbirth) were excluded. Data were analyzed from June 11 to September 8, 2025.
Exposure:
Mode of birth.
Main Outcomes And Measures:
The primary outcome was any stroke, defined as a composite of ischemic or hemorrhagic stroke. Secondary outcomes included ischemic stroke, hemorrhagic stroke, and transient ischemic attack.
Results:
Of 1683 women analyzed (mean [SD] age, 33.6 [7.8] years), 1077 (64.0%) had cesarean births, and 606 (36.0%) had vaginal births. Post partum (3 months), any stroke incidence was 63.49 and 33.33 per 1000 person-years for cesarean and vaginal births, respectively. Multivariable analyses showed no significant risk differences for any stroke by birth mode at 3 months (adjusted hazard ratio [aHR], 0.71 [95% CI, 0.26-1.97]; P = .52) or 3 years (aHR, 0.90 [95% CI, 0.55-1.47]; P = .67). A significant interaction was observed between the mode of birth and the clinical onset type of MMD for the risk of any stroke (interaction P = .04 after Bonferroni correction); the adjusted HR for vaginal vs cesarean birth was 0.10 (95% CI, 0.01-0.79) in the asymptomatic or nonvascular onset subgroup, 1.49 (95% CI, 0.73-3.03) in the ischemic onset subgroup, and 0.94 (95% CI, 0.50-1.77) in the hemorrhagic onset subgroup. Notably, stroke incidence peaked in the early postpartum period (≤6 months: 35.7 per 1000 person-years), decreased at 1 year, and thereafter remained at a similar level.
Conclusions And Relevance:
In this cohort study of women with MMD, MMD itself was not found to be an absolute indication for cesarean birth; birth planning should be individualized based on obstetric factors and clinical onset type rather than routine preference for cesarean birth. In addition, vigilant monitoring and preventive strategies during the early postpartum period are warranted.
Related Concept Videos
 01:27
Regulation of Stroke Volume
Preload refers to the degree of stretch on the heart before it contracts. It's analogous to the stretching of a rubber band; the more it's stretched, the more forcefully it snaps back. This concept is encapsulated in the Frank-Starling law of the...
 01:17
Ischemic Heart Disease: Overview
Atherosclerosis, the primary malefactor, orchestrates this dangerous condition. It manifests as the accumulation of fatty deposits, akin to insidious plaques, within arterial walls. As time elapses, these plaques metamorphose, hardening and...
 01:19
Mitral Valve Prolapse III: Nursing Management
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:26
Mitral Stenosis III: Medical Management