Related Experiment Video
Updated: Mar 25, 2026
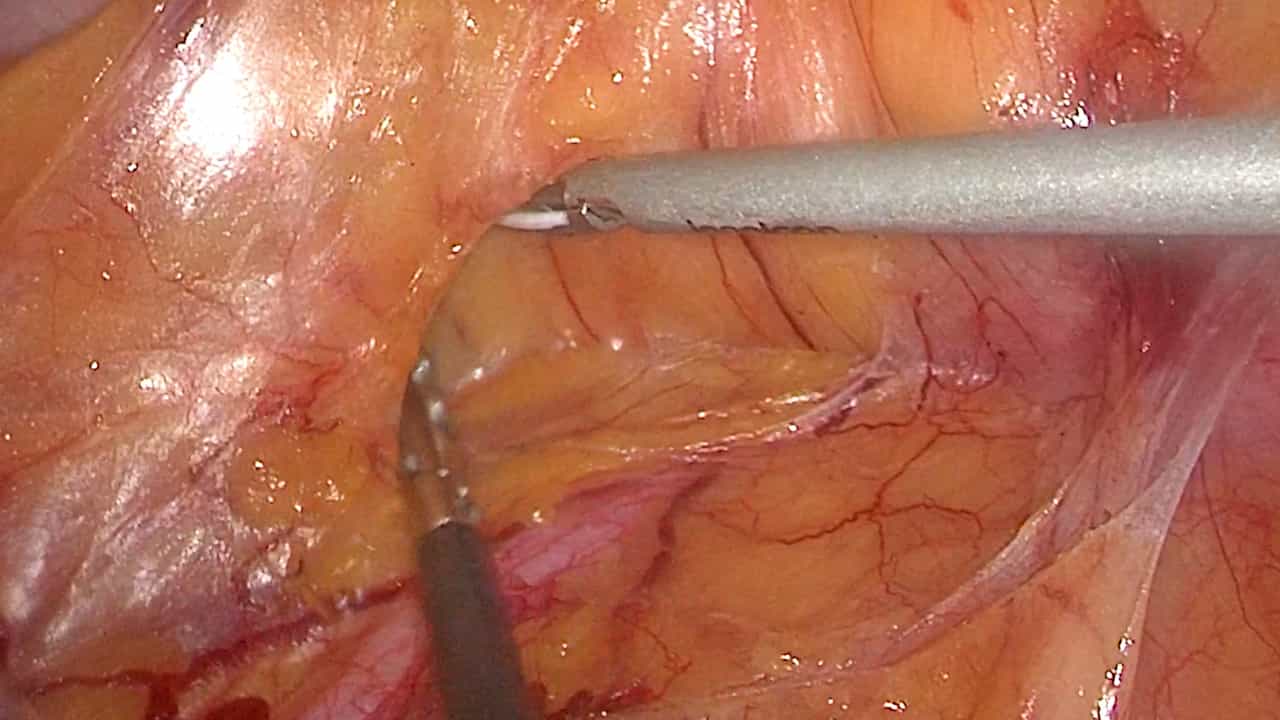

Caudal-to-cranial Approach in Laparoscopic Right Hemicolectomy with Complete Mesocolon Excision and D3 Lymph Node Dissection
Published on: January 9, 2026
A multinational pilot survey of clinical practice patterns in tumor-specific mesocolic excision and complete lymph
Sergey Efetov1, Rodrigo Perez2, Roel Hompes3
1Clinic of Faculty Surgery №2, I.M. Sechenov First Moscow State Medical University (Sechenov University), 2-4 Bolshaya Pirogovskaya St., Moscow, Russia, 119991. efetov@mail.ru.

Background:
Uncertainties persist regarding the allocation of apical lymph nodes in colorectal cancer, the approaches to lymph node dissection and mesocolic excision, which may contribute to inconsistent surgical practices. The aim of this study is to assess surgeons' practices in lymph node dissection and mesocolic excision approaches and to identify areas lacking standardization.
Methods:
A multinational pilot survey of 22 colorectal surgeons from 6 countries was conducted during the FICARE colorectal meeting. The survey consisted of 21 Likert-scale questions on surgical practices and lymph node allocation in colorectal cancer surgery.
Results:
Majority of the respondents (90.9%) recognized conceptual differences in apical lymph node stratification between right- and left-sided colon cancers, whereas D3 LND for left-sided cancer should include mesocolic tissue along the inferior mesenteric artery from its origin to the last sigmoid artery. Complete lymph node dissection requires excision of mesocolic tissue along inferior mesenteric artery for left colon cancer and superior mesenteric artery for right colon cancer according to 81.8% of respondents. At the same time, 95.5% agreed that intermediate and paracolic lymph nodes are located within a 10-cm resection margin proximally and distally from tumor, while 81.9% of respondents supported the concept of tumor-specific mesocolic excision to be sufficient enough for adequate paracolic and intermediate lymph node dissection.
Conclusions:
A multinational snapshot showed an existing contraindication in surgeons' perception of lymph node stratification and the variability in mesocolic excision and LND. Further Delphi consensus is needed to prove the suggested concepts.
More Related Videos
 05:43
The Role of Anatomical Dissection in Defining Colic and Small Bowel Artery Lymphovascular Bundles in the D3 Volume of Small and Large Bowel Mesentery
Published on: August 1, 2025
 12:45
Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022