Related Experiment Video
Updated: Mar 27, 2026
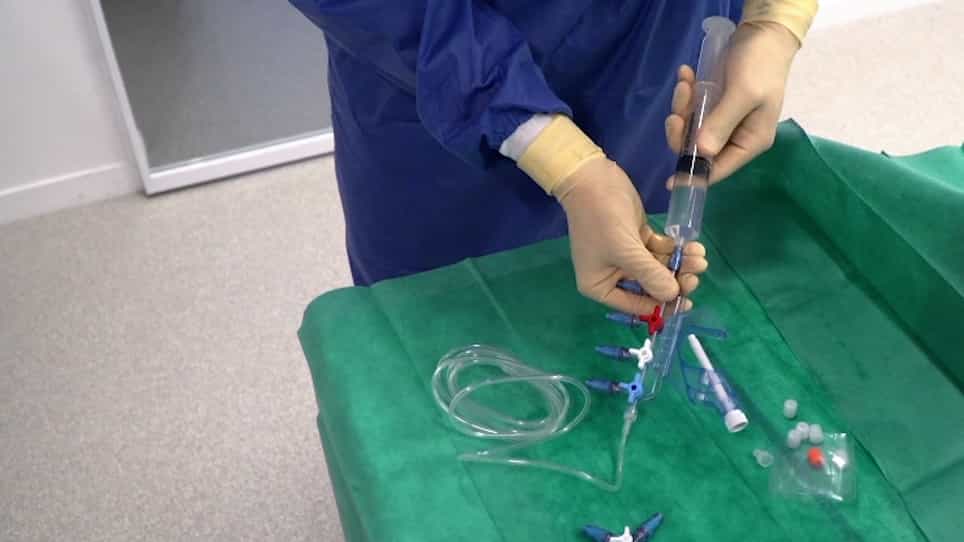

A Protocol to Set Up Needle-Free Connector with Positive Displacement on Central Venous Catheter in Intensive Care Unit
Published on: July 13, 2019
Midline and central line catheters usage and blood stream infection: Trends and insights from 2016 to 2024
Patrick McGinnis1, Samantha Camp1, Minahil Cheema1
1University of Maryland School of Medicine, Baltimore, MD, United States.

Background:
Central line-associated bloodstream infections (CLABSIs) remain a major source of hospital-related morbidity and mortality. Replacing central venous catheters (CVCs) with midline catheters (MLCs), when clinically appropriate, has been proposed as a strategy to reduce the incidence of CLABSI cases. We hypothesized that increased MLC utilization would correlate with decreased CLABSI incidence.
Research Question:
Is increased use of midline catheters, in place of central venous catheters, associated with reduced CLABSI incidence over time?
Study Design And Methods:
We conducted a retrospective analysis using the TriNetX database, which includes de-identified data from over 130 million patients across 94 healthcare organizations (2016-2024). Adults with ICD-10 procedure codes for CVC or MLC placement were included. Propensity score matching, logistic-binomial and Poisson regression (with log line-count offset), and time-series modeling were used to evaluate device utilization and CLABSI incidence. Matching covariates included demographics and clinical proxies of acuity and infection risk e.g., ICU admission, vasopressor use, mechanical ventilation, parenteral nutrition, chemotherapy, immunosuppression, transplant, CKD, diabetes. Post-match balance was assessed using standardized mean differences (SMDs); all covariates achieved SMD <0.1 (Supplementary Fig. S1). This study was reviewed and determined to be exempt from full review by an institutional review board, as it only utilized anonymized, retrospective data. As such, the requirement for informed consent from participants was waived.
Results:
Among 268,401 adults, 58,205 (22%) received a midline catheter (MLC) and 168,098 (63%) received a central venous catheter (CVC); 7036 received both during the study period, yielding 42,098 CLABSI events. MLC use increased from 3200 in 2016 to 10,449 in 2024, while CVC use declined from 23,316 to 11,912. In propensity-matched CVC cohorts, the crude proportion of CLABSI remained stable (0.5-0.8% annually; p for trend = 0.55). Poisson regression adjusting for device exposure estimated each year a 14% increase in CLABSI incidence (IRR per year = 1.14, p < 0.001); midline share was not an independent predictor (IRR = 1.19, p = 0.66). After propensity score matching, odds of CLABSI decreased by ∼0.8% per year although this effect was not statistically significant (p = 0.745). Candidal sepsis was rare (<0.5% annually) without device-type differences; bacterial/unspecified sepsis was modestly higher among midline recipients in select years.
Interpretation:
Despite increased MLC use and reduced CVC utilization, CLABSI rates did not decline, suggesting that catheter type alone may not drive infection risk. A multifaceted infection prevention approach, including site selection, maintenance practices, and patient-specific considerations is needed when determining catheter choice.
More Related Videos
Related Concept Videos
 01:29
Endocarditis IV: Nursing Management
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:27
Parentral Nutrition: Centeral and Peripheral Parental Nutrition
PN can be administered through two primary routes:
1. Central Parenteral Nutrition (CPN):
CPN involves delivering a high concentration of nutrients through a large vein. This is typically achieved using a Peripherally Inserted Central Catheter (PICC) or,...
 01:26
Healthcare Associated Infections I: Iatrogenic, Exogenic and Endogenic
HAIs significantly increase the cost of health care. Extended stays in healthcare institutions, increased disability, increased costs of medications, including specialized antibiotics, and prolonged recovery times add to the patient's expenses and the healthcare institution and funding bodies.
 01:25
Endocarditis I: Introduction
 01:29
Venous Thrombosis III: Interprofessional Care