Related Experiment Video
Updated: Mar 27, 2026


Author Spotlight: A Single-Entry Point Endoscopic Intraventricular Approach for Third Ventriculostomy and Pineal Biopsy
Published on: June 28, 2024
Pineal cyst surgery beyond morphology: a critical evaluation of a consecutive surgical series
Filipe Wolff Fernandes1, Assel Saryyeva2, Elvis J Hermann2
1Department of Neurosurgery, Hannover Medical School, Hannover, Germany. Wolfffernandes.filipe@mh-hannover.de.

Purpose:
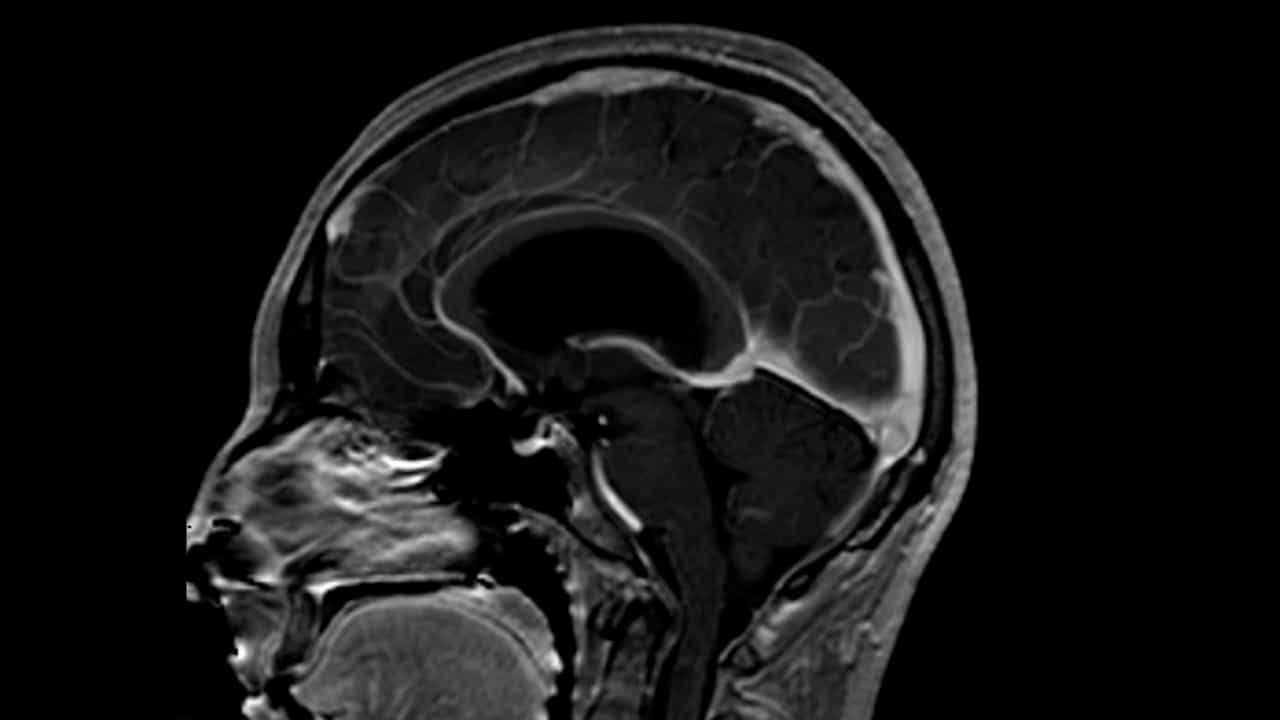
The surgical management of pineal cysts (PC) remains controversial, particularly in non-hydrocephalic patients where radiological and clinical correlations are inconsistent. Most studies rely on cyst size or morphology as surgical criteria. This study aims to assess clinical-radiological correlations and outcomes in a consecutive single-center cohort, and to compare outcomes across microsurgical, endoscopic, and stereotactic approaches.
Methods:
A retrospective analysis was performed on 46 symptomatic PC patients treated between 2008 and 2024. Clinical data and radiological data, including cyst dimensions, third ventricle-mesencephalic angle, aqueduct diameter, and predominant expansion were analyzed. Patients were categorized into surgical (n = 18) and non-surgical (n = 28) cohorts. Surgical outcomes were assessed using the Chicago Chiari Outcome Scale (CCOS) at 3-month, 12-month, and long-term follow-up. Statistical comparisons were conducted to correlate radiological markers with symptoms and postoperative outcomes.
Results:
Headache was the most common symptom in both groups (80%), followed by visual disturbances in the surgical group (33%), and vertigo in the non-surgical group (32%). Compared with the non-surgical cohort, the surgical patients had larger cysts, narrower aqueducts (0.9 vs. 1.6 mm, p < 0.001) and a higher prevalence of predominant anterior expansion (67% vs. 7%, p < 0.001). Among all operated patients, 94% achieved good or excellent CCOS outcomes at 12-months, and 93% maintained these outcomes at long-term follow-up (mean 62 months, range 16-216 months). Neither PC volume nor hydrocephalus predicted consistently postoperative outcome. Microsurgical resection (n = 12) achieved favorable long-term outcome (mean CCOS 14.9), but the highest complication rate (3 patients) and the highest recurrence of headache despite total PC excision. Endoscopic fenestration with ventriculostomy (n = 3) yielded the best long-term outcome (mean CCOS 15.7) with no recurrences. Stereotactic drainage with a catheter with a Rickham reservoir placement (n = 3) provided stable decompression but lower CCOS scores at long-term (mean CCOS 13.0) compared with other approaches.
Conclusion:
Surgery for symptomatic PC provides durable improvement when guided by radiological-clinical criteria. Aqueduct diameter was more closely associated with outcome than PC size. Microsurgical, endoscopic, and stereotactic approaches each have specific roles that should guide individualized treatment.