
Diffuse Correlation Spectroscopy for Noninvasive Monitoring of Peripheral Perfusion During Cardiogenic Shock and
Hiroki Matsushita1, Kenta Oba1, Koki Kurono2
1Department of Cardiovascular Dynamics, National Cerebral and Cardiovascular Center Research Institute, Suita, Japan.

Objective:
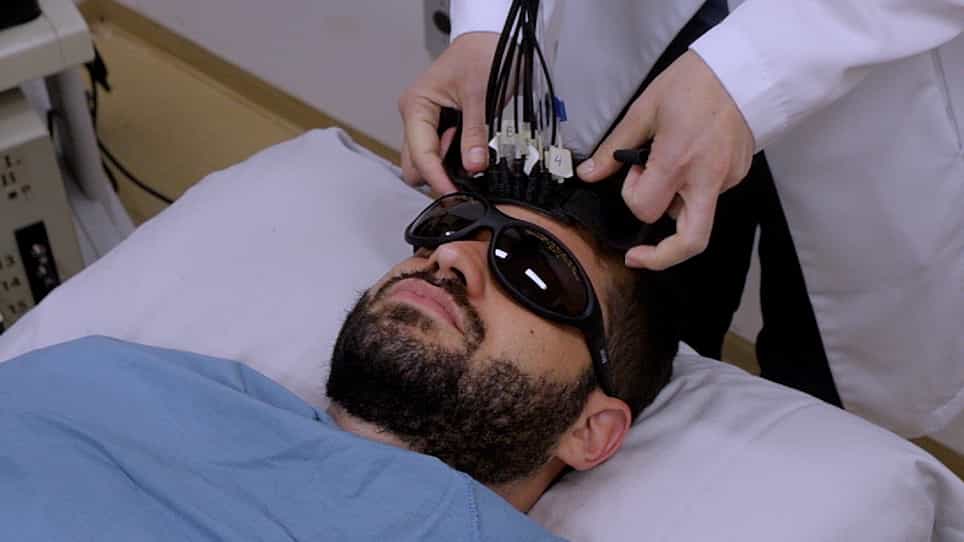
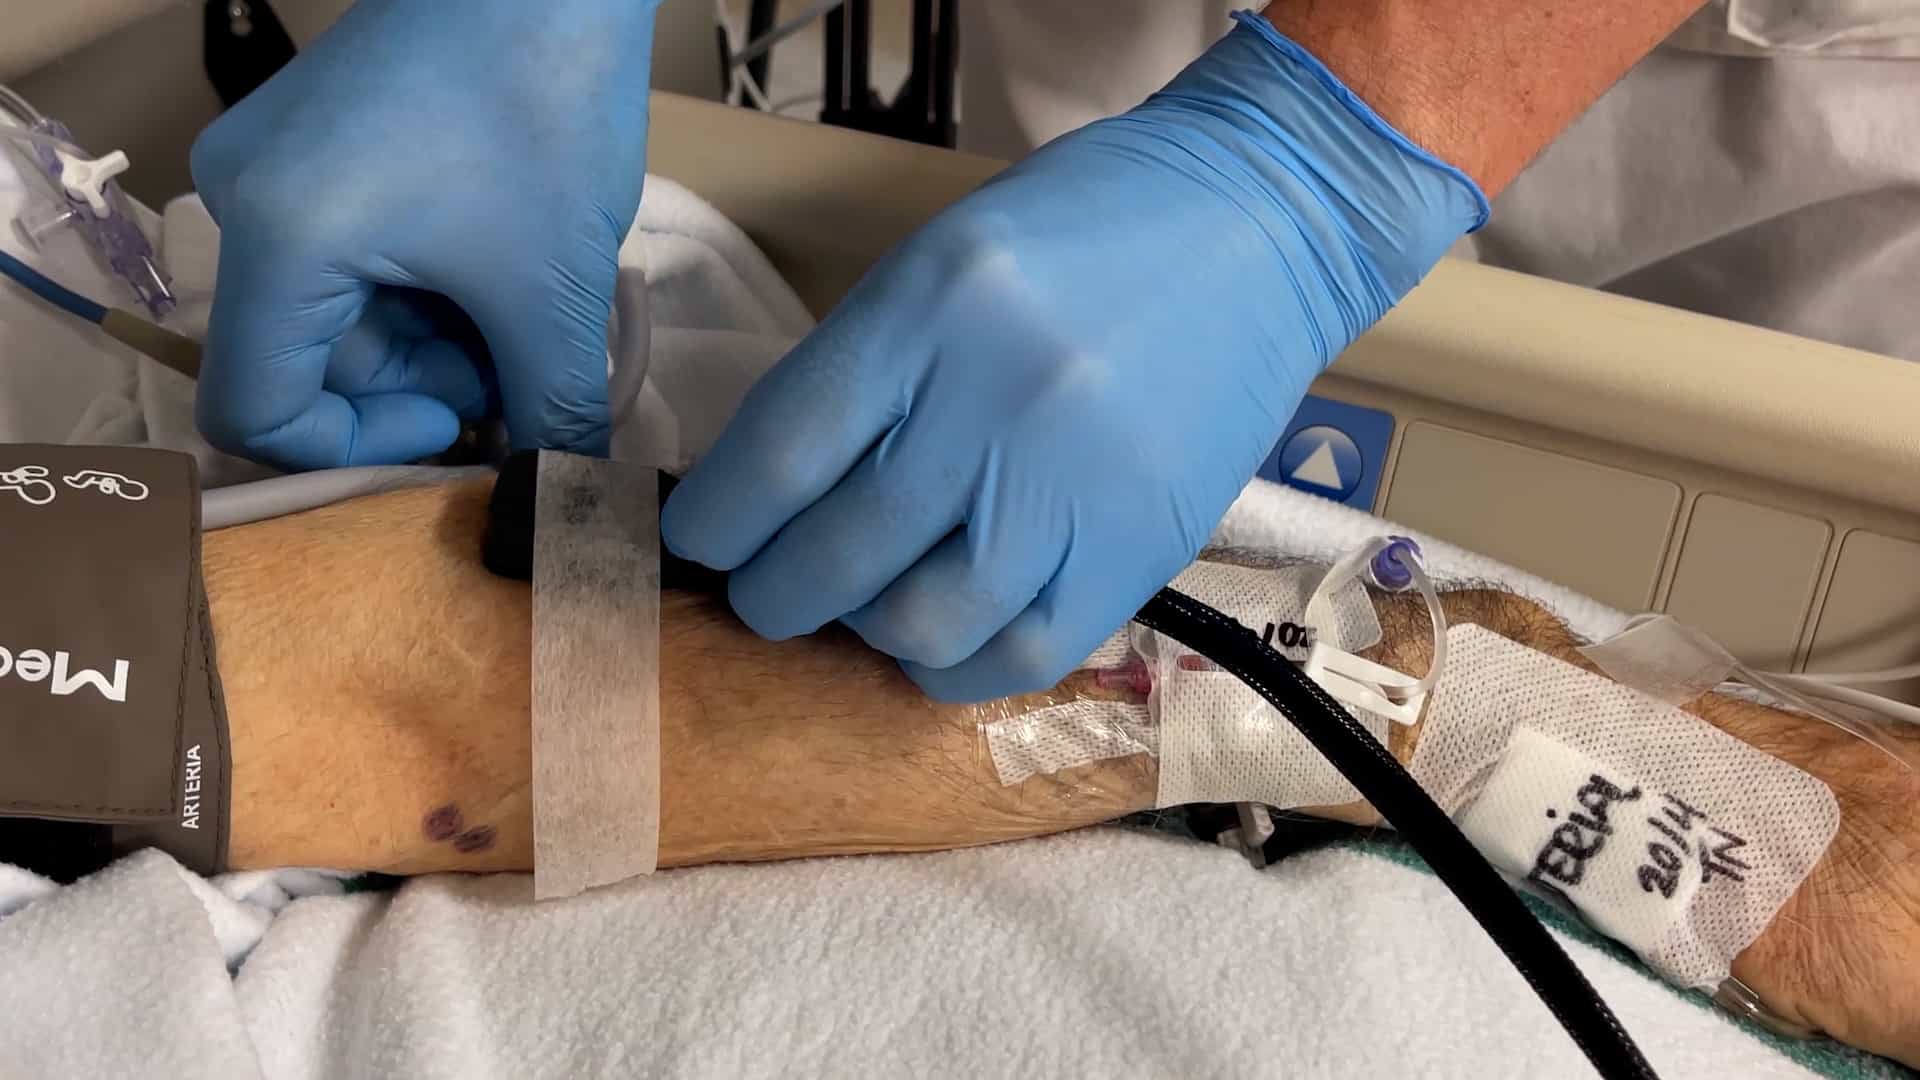
In cardiogenic shock (CS), persistent microcirculatory impairment despite improved macrocirculatory parameters is associated with poor outcomes. Therapeutic strategies must therefore address both macro- and microcirculation. Conventional microcirculatory measures have limitations, especially during venoarterial extracorporeal membrane oxygenation support (VA-ECMO). Diffuse correlation spectroscopy (DCS) is a novel optical technique enabling continuous, noninvasive evaluation of microvascular blood flow. This study evaluated DCS for monitoring microcirculation in CS under VA-ECMO.
Methods:
Seven male beagle dogs (median weight 10.1 kg) underwent CS induction by coronary ligation followed by ventricular fibrillation (VF). VA-ECMO (80-100 mL·kg -1 ·min -1 ) was initiated 5 minutes after VF onset and maintained for 90 minutes under nonpulsatile flow. After stabilization, VA-ECMO flow was reduced from 100 to 30 mL·kg -1 ·min -1 , and mean arterial pressure (MAP) was increased to ≥65 mmHg using vasoconstrictors. Measurements included MAP, cardiac output, and microcirculatory parameters [DCS-derived blood flow index (BFI), perfusion index, skin blood flow, tissue oxygen saturation, mixed venous oxygen saturation, and lactate].
Results:
Coronary ligation caused progressive declines in MAP, cardiac output, and microcirculatory indices. MAP [median (interquartile range)] was 109.6 (95.8, 119.7) at baseline and 45.7 (26.3, 51.6) mmHg at CS onset. During VF, perfusion index became unmeasurable while BFI rapidly fell to near zero, detecting peripheral flow loss under nonpulsatile conditions. VA-ECMO initiation restored MAP and mixed venous oxygen saturation, with gradual recovery of BFI and skin blood flow. Reducing VA-ECMO flow lowered MAP [64.7 (62.3, 69.9) to 36.4 (34.4, 44.6) mmHg] and BFI [3.6 (3.4, 5.1) to 1.0 (0.8, 1.2) × 10 -9 ·cm 2 ·s -1 ]. Vasopressors increased MAP [83.1 (79.0, 89.1) mmHg] but failed to improve BFI [1.5 (1.3, 2.1) × 10 -9 ·cm 2 ·s -1 ], indicating persistent microcirculatory impairment.
Conclusions:
DCS continuously detected microvascular changes during CS and VA-ECMO support regardless of pulsatility. DCS may be useful for early identification of microcirculatory dysfunction and optimization of therapy in CS.