
Updates on pancreas exocrine function in cystic fibrosis for the era of highly effective modulator therapy
Mitchell L Ramsey1, Chee Y Ooi2
1Division of Gastroenterology, Hepatology, and Nutrition, College of Medicine, The Ohio State University Wexner Medical Center, Columbus, OH, USA.

Insights
Cystic fibrosis (CF) treatments are evolving. New CFTR modulator therapies (CFTRm) may alter pancreatic function, requiring careful monitoring and enzyme replacement therapy (PERT) adjustments.
Area of Science:
- Gastroenterology
- Pulmonology
- Genetics
Background:
- The pancreas is an early target organ in cystic fibrosis (CF).
- Exocrine pancreatic insufficiency (PI) is common in CF, necessitating lifelong pancreatic enzyme replacement therapy (PERT).
- Emerging CFTR modulator therapies (CFTRm) are changing CF treatment paradigms.
Purpose of the Study:
- To review the diagnosis and treatment of exocrine pancreatic disease in CF patients using CFTRm.
- To discuss the impact of CFTRm on the natural history of the exocrine pancreas.
- To provide guidance on managing PERT in the era of CFTRm.
Main Methods:
- Review of current literature on CF exocrine pancreatic disease and CFTRm.
- Analysis of natural history data in the context of CFTRm use.
- Clinical recommendations for monitoring and management.
Main Results:
- CFTRm may alter pancreatic function, but regaining pancreatic sufficiency (PS) is rare.
- Objective exocrine function testing (e.g., fecal elastase) is recommended for patients on CFTRm.
- Most improvements in exocrine function are observed in children; adults on CFTRm are less likely to reduce PERT.
Conclusions:
- Clinicians should monitor exocrine function and counsel patients on unknowns regarding CFTRm.
- Stepwise de-escalation of PERT is advised, rather than abrupt discontinuation.
- Close monitoring for complications of severe PI is crucial, especially in adults starting CFTRm later in life.
Abstract:
The pancreas is one of the earliest affected organs in cystic fibrosis (CF). Most newborn screening programs are based on pancreatic inflammation causing elevated trypsinogen at birth, and most individuals with CF are born with exocrine pancreatic insufficiency (PI) which requires lifelong treatment with pancreas enzyme replacement therapy (PERT). However, as CFTR modulating therapies (CFTRm) are administered earlier and earlier, these paradigms may be changing. In this article, we summarize updates on the diagnosis and treatment of exocrine pancreatic disease in CF in the era of CFTRm. We provide a concise review on the natural history of the exocrine pancreas in CF as a context to discuss new observations of CFTRm use at different time points in utero, in childhood, and in adulthood. Clinicians are encouraged to obtain objective exocrine function testing (i.e., fecal elastase) among individuals receiving CFTRm therapy, and to counsel patients and/or parents on the unknowns regarding natural history during CFTRm use. Few patients will regain pancreatic sufficiency (PS) and we encourage clinicians to de-escalate PERT stepwise, rather than discontinue abruptly. Lastly, it is important to note that most reports of improved exocrine function are described in children, and individuals who started CFTRm in adulthood are unlikely to experience reduction in PERT dose and should continue close monitoring for late complications of severe PI, like fat soluble vitamin deficiency and metabolic bone disease.
More Related Videos
 08:00
Generation of Human Nasal Epithelial Cell Spheroids for Individualized Cystic Fibrosis Transmembrane Conductance Regulator Study
Published on: April 11, 2018
 07:04
Forskolin-induced Swelling in Intestinal Organoids: An In Vitro Assay for Assessing Drug Response in Cystic Fibrosis Patients
Published on: February 11, 2017
Related Concept Videos
 01:24
Cystic Fibrosis: Management
Sinus disease and chronic...
 01:23
Cystic Fibrosis: Pathogenesis
CF is primarily caused by a genetic mutation in a chromosome 7 gene coding for the cystic fibrosis transmembrane conductance regulator (CFTR) protein. The most common gene mutation leading to CF is the ΔF508 mutation,...
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:16
Cells and Secretions of the Pancreas
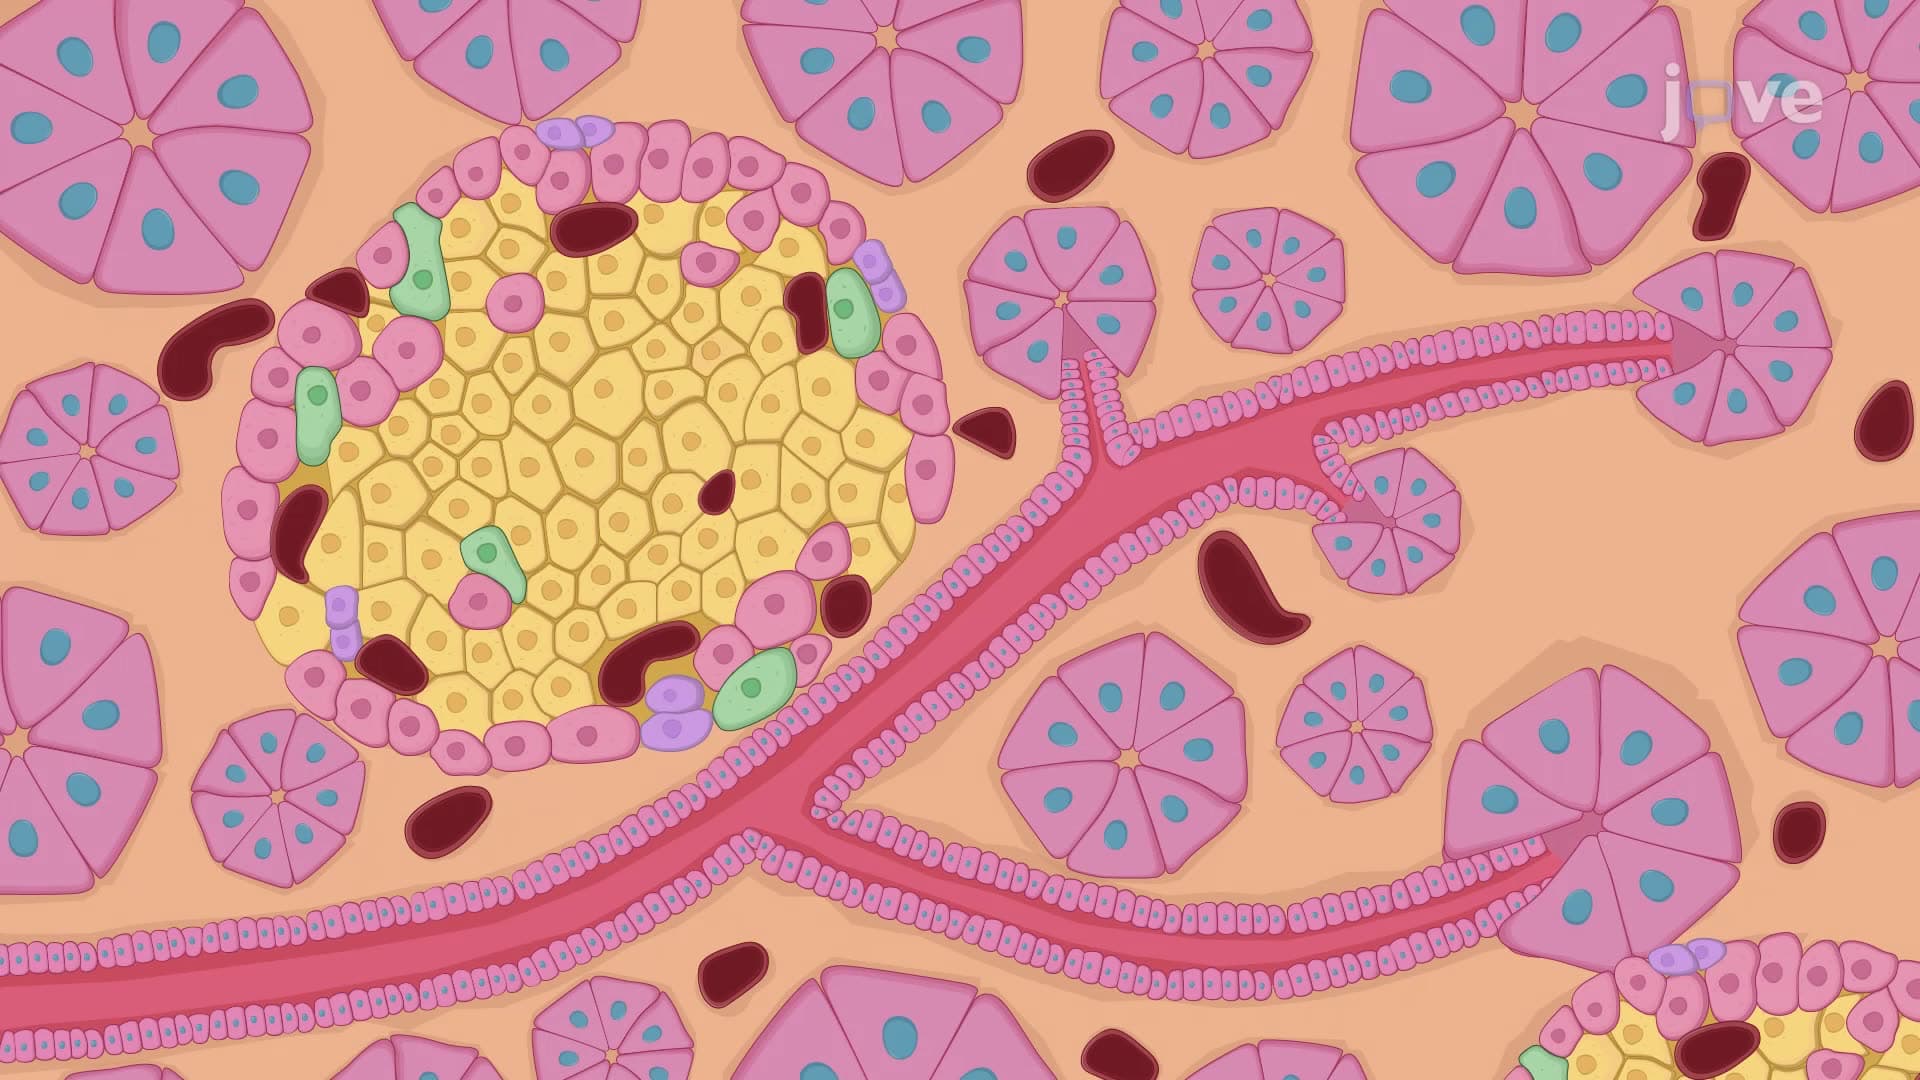
Exocrine function is carried out by acinar cells, organized into clusters known as acini. These cells contribute to digestion by releasing substantial quantities of enzyme-rich, alkaline digestive juices.
Concurrently, the dispersed clusters of endocrine cells throughout the...
 01:26
Pancreatic Juice and Secretion
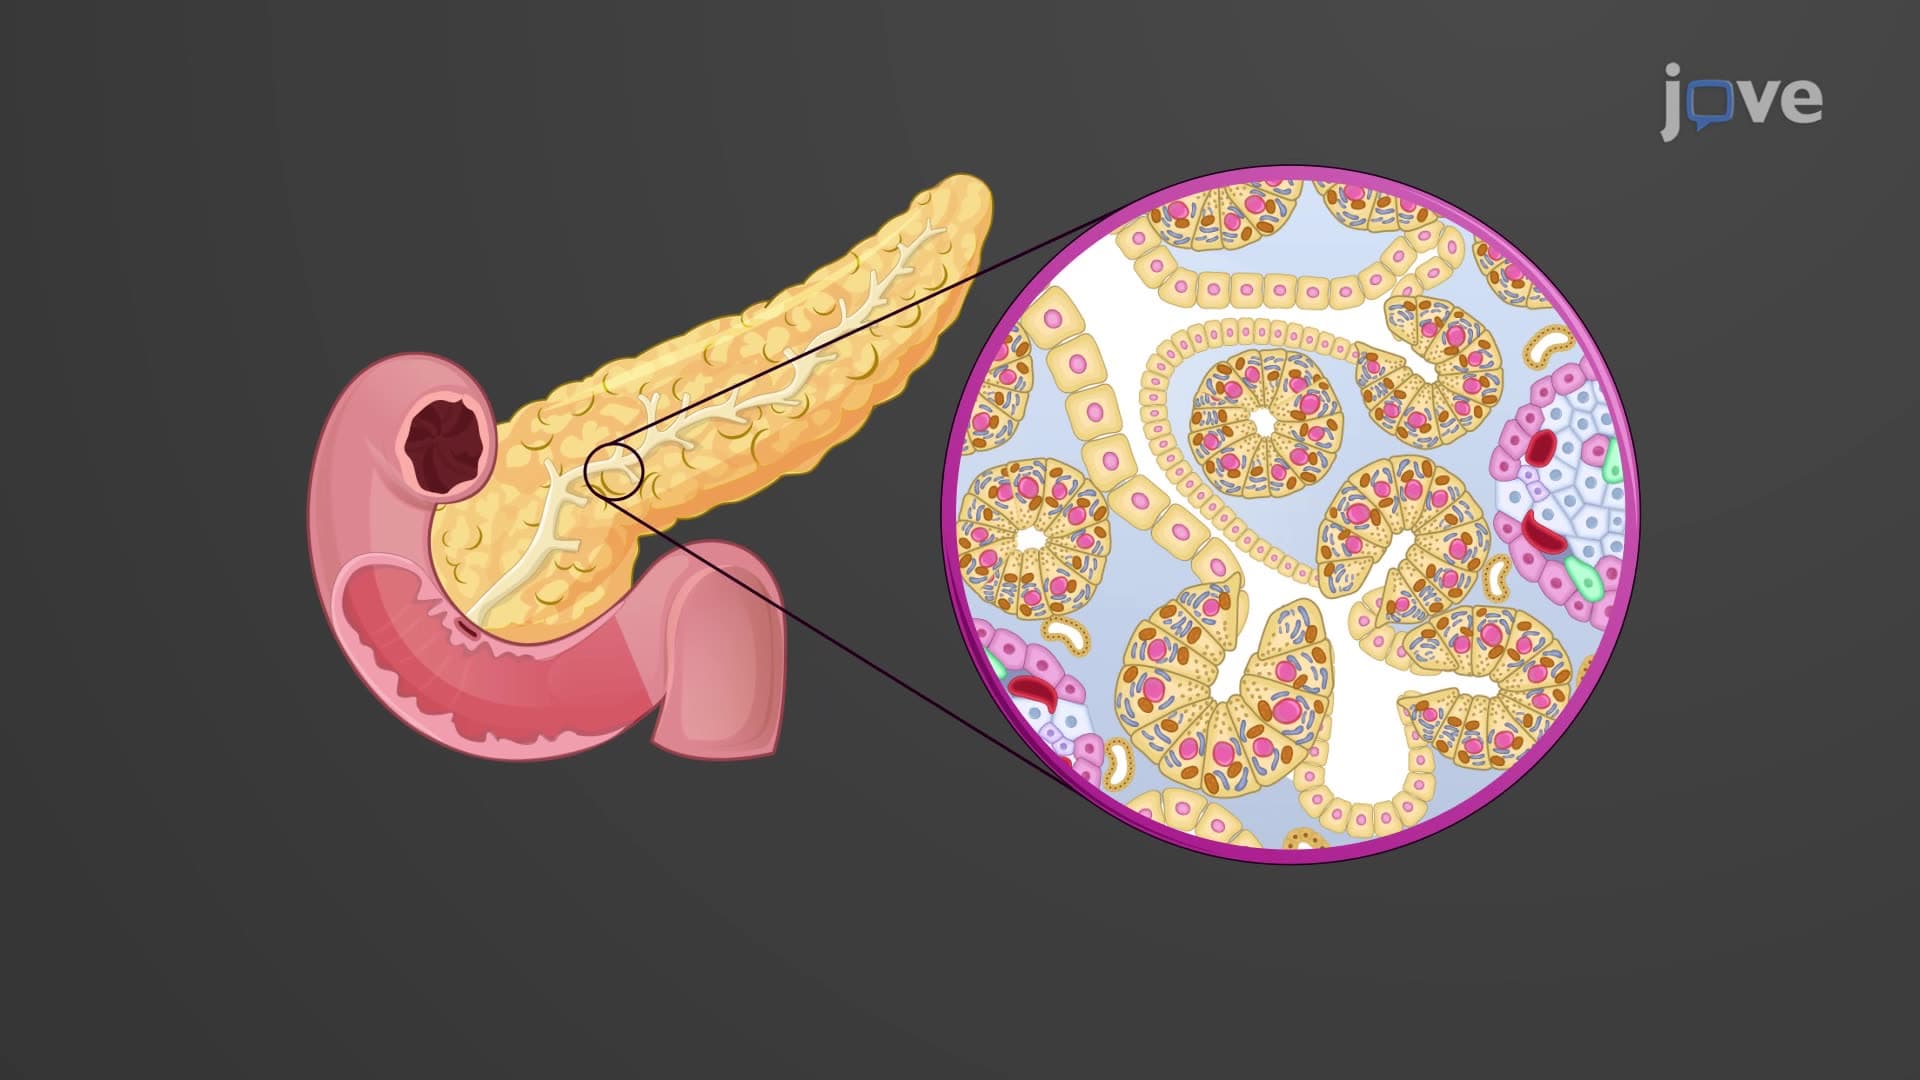
When acidic chyme from the stomach enters the duodenum, it triggers the release of secretin, a hormone that prompts pancreatic juice secretion. After a fatty meal, cholecystokinin, another hormone, stimulates gallbladder contraction and enhances enzyme-rich...
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
Insulin and C-peptide are...