Related Experiment Video
Updated: Mar 28, 2026
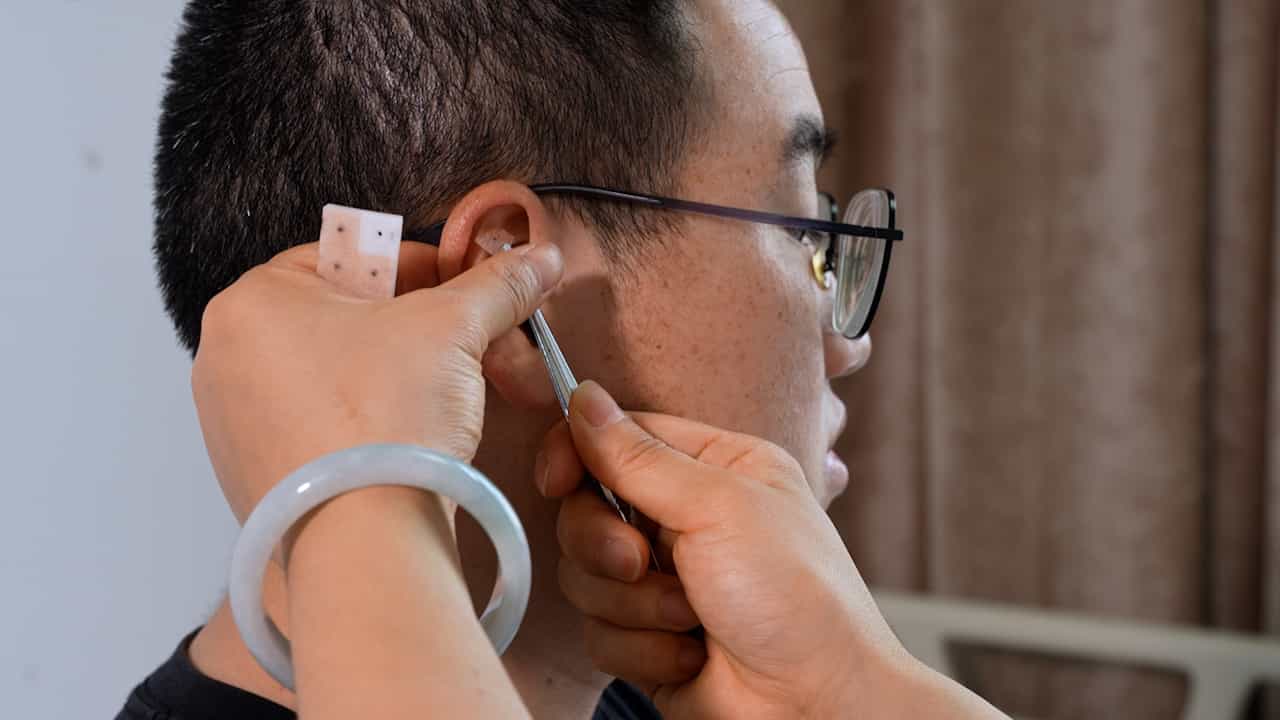

Author Spotlight: Efficacy of Auricular Pressure Bean Therapy in Reducing Wheezing Symptoms
Published on: May 10, 2024
Sickle Cell Lung Disease in a 9-year-Old Presenting with Wheezing: Investigating Causal Relationships, Asthma or
David Mukunya1, Daniel Mawanda2, Rebecca Nantanda3
1Department of Community and Public Health, Busitema University, Mbale, Uganda.

Background:
Sickle cell disease (SCD) affects about 7.7 million people worldwide, and this has been increasing annually due to an increasing population in sub-Saharan Africa and the Caribbean. Pulmonary complications contribute significantly to mortality due to sickle cell disease. We have frequently heard wheezing in children with sickle cell disease that has responded to beta agonists such as salbutamol leading us to wonder whether this was asthma or a presentation of acute chest syndrome. We present this case to highlight the co-occurrence of sickle cell disease and asthma, and to re-ignite the debate on the whether this is coincidental or causal.
Case Presentation:
We present a 9-year-old male from Ugandan, with no known history of any chronic illness who presented with a one-day history of abdominal, limb, and chest pain. He had associated yellowing of eyes, palpitations, and difficulty in breathing. The patient had had a long-standing history of difficulty in breathing, worse during the night and cold seasons, relieved by taking prednisolone tablets that were bought over the counter. On examination, he was sick looking, in mild respiratory distress, with moderate pallor and severe jaundice. Investigation showed a low hemoglobin (6.6g/dl) and immunoglobulin E (IgE) levels were 2300 IU/mL (normal range 0.1 to 200 IU/mL). Hemoglobin electrophoresis showed predominantly sickled hemoglobin (HbSS) (71%), and low fetal hemoglobin (HbF) (8.3%). Spirometry showed an increase of forced expiratory volume after bronchodilator therapy of 22.8%. We made a diagnosis of sickle cell disease and asthma and managed the patient using oxygen, fluid therapy, analgesia, salbutamol by nebulization, hydroxyurea, folate, ceftriaxone and a blood transfusion. For the long-term management, we initiated him on hydroxyurea 20.8mg/kg/day, folate, and fansidar. We also prescribed budesonide and formeterol and are in the process of linking him to a regional referral hospital for chronic care.
Conclusion:
We present a case of a 9-year-old newly diagnosed with sickle cell disease and asthma highlighting that both conditions can occur in the same individual. We diagnosed both during the same visit and cannot comment on what manifested first. Our findings reinforce the importance of objective pulmonary function testing and allergic evaluation when assessing wheezing in children with SCD.


Related Concept Videos
 01:24
Asthma-III: Symptoms and Complications
Classification of Asthma
 01:29
Asthma-I: Introduction
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include: