Related Experiment Video
Updated: Mar 30, 2026
Modeling Hypoxia/Reoxygenation Injury in Proximal Tubular Epithelial Cells
Published on: November 21, 2025
The Influence of Renal or Hepatic Impairment on the Pharmacokinetics of Iclepertin (BI 425809): Results from Two
HeeJae Choi1, Shilpa Madari1, Elmar Daalman2
1Boehringer Ingelheim Pharmaceuticals, Inc., Ridgefield, CT, USA.

Background And Objectives:
Iclepertin, a selective GlyT1 inhibitor undergoes metabolism mainly via hepatic CYP3A4, with only a small fraction undergoing urinary excretion. Patients with kidney or liver problems can have reduced CYP3A4 levels or activity, which may affect the levels of iclepertin in the blood and, in turn, its safety. Here, we present the results of two studies investigating the safety and pharmacokinetics of iclepertin in participants with various degrees of renal or hepatic impairment.
Methods:
In these two phase I, open-label, non-randomised, parallel studies, a single oral dose of iclepertin 10 mg was administered to participants with mild, moderate or severe renal impairment or mild or moderate hepatic impairment, together with healthy matched participants (based on age, sex, weight and race [only for renal impairment]; n = 8 for each impairment group. Primary and secondary endpoints included maximum plasma concentration (Cmax) and exposure metrics (area under the concentration-time curve [AUC]) of iclepertin. Safety was also assessed (adverse events [AEs]).
Results:
In the renal impairment study (N = 36), exposure of iclepertin was minimally affected by renal impairment across trial groups except for the severe renal impairment group, which showed increased iclepertin exposure (AUC0-tz and AUC0-∞ geometric mean ratio impaired versus matched participants [90% CI]: 126.1% [104.1, 152.8] and 146.0% [109.9, 193.9]), but similar Cmax. In the hepatic impairment study (N = 29), participants with mild hepatic impairment showed similar Cmax of iclepertin and exposure parameters to matched participants (geometric mean ratio [90% CI]: 102.1% [82.4, 126.4]), whereas participants with moderate hepatic impairment showed reduced Cmax (geometric mean ratio impaired versus matched participants [90% CI]: 81.9% [67.2, 99.7]) and increased AUC0-tz and AUC0-∞ (128.7% [104.0, 159.3] and 157.2% [119.1, 207.5], respectively. Headache was the only drug-related AE reported in > 1 participant in each study, which was resolved within the treatment period, and no severe AEs were reported.
Conclusions:
These findings indicate that although some increased exposure to iclepertin is expected in patients with severe renal impairment or moderate hepatic impairment, iclepertin 10 mg demonstrated a favourable safety profile, was well-tolerated, and can be administered in patients with varying degrees of renal or hepatic impairment without dose modification.
Study Registration:
ClinicalTrials.gov (NCT05718843, NCT05731895).
More Related Videos
 09:32
Drug-Induced Senescence in Liver Cells Promotes M2 Macrophage Polarization: Implications for Tyrosine Kinase Inhibitor-Associated Hepatotoxicity
Published on: October 17, 2025
 07:35
Use of Ultra-high Field MRI in Small Rodent Models of Polycystic Kidney Disease for In Vivo Phenotyping and Drug Monitoring
Published on: June 23, 2015
Related Concept Videos
 01:14
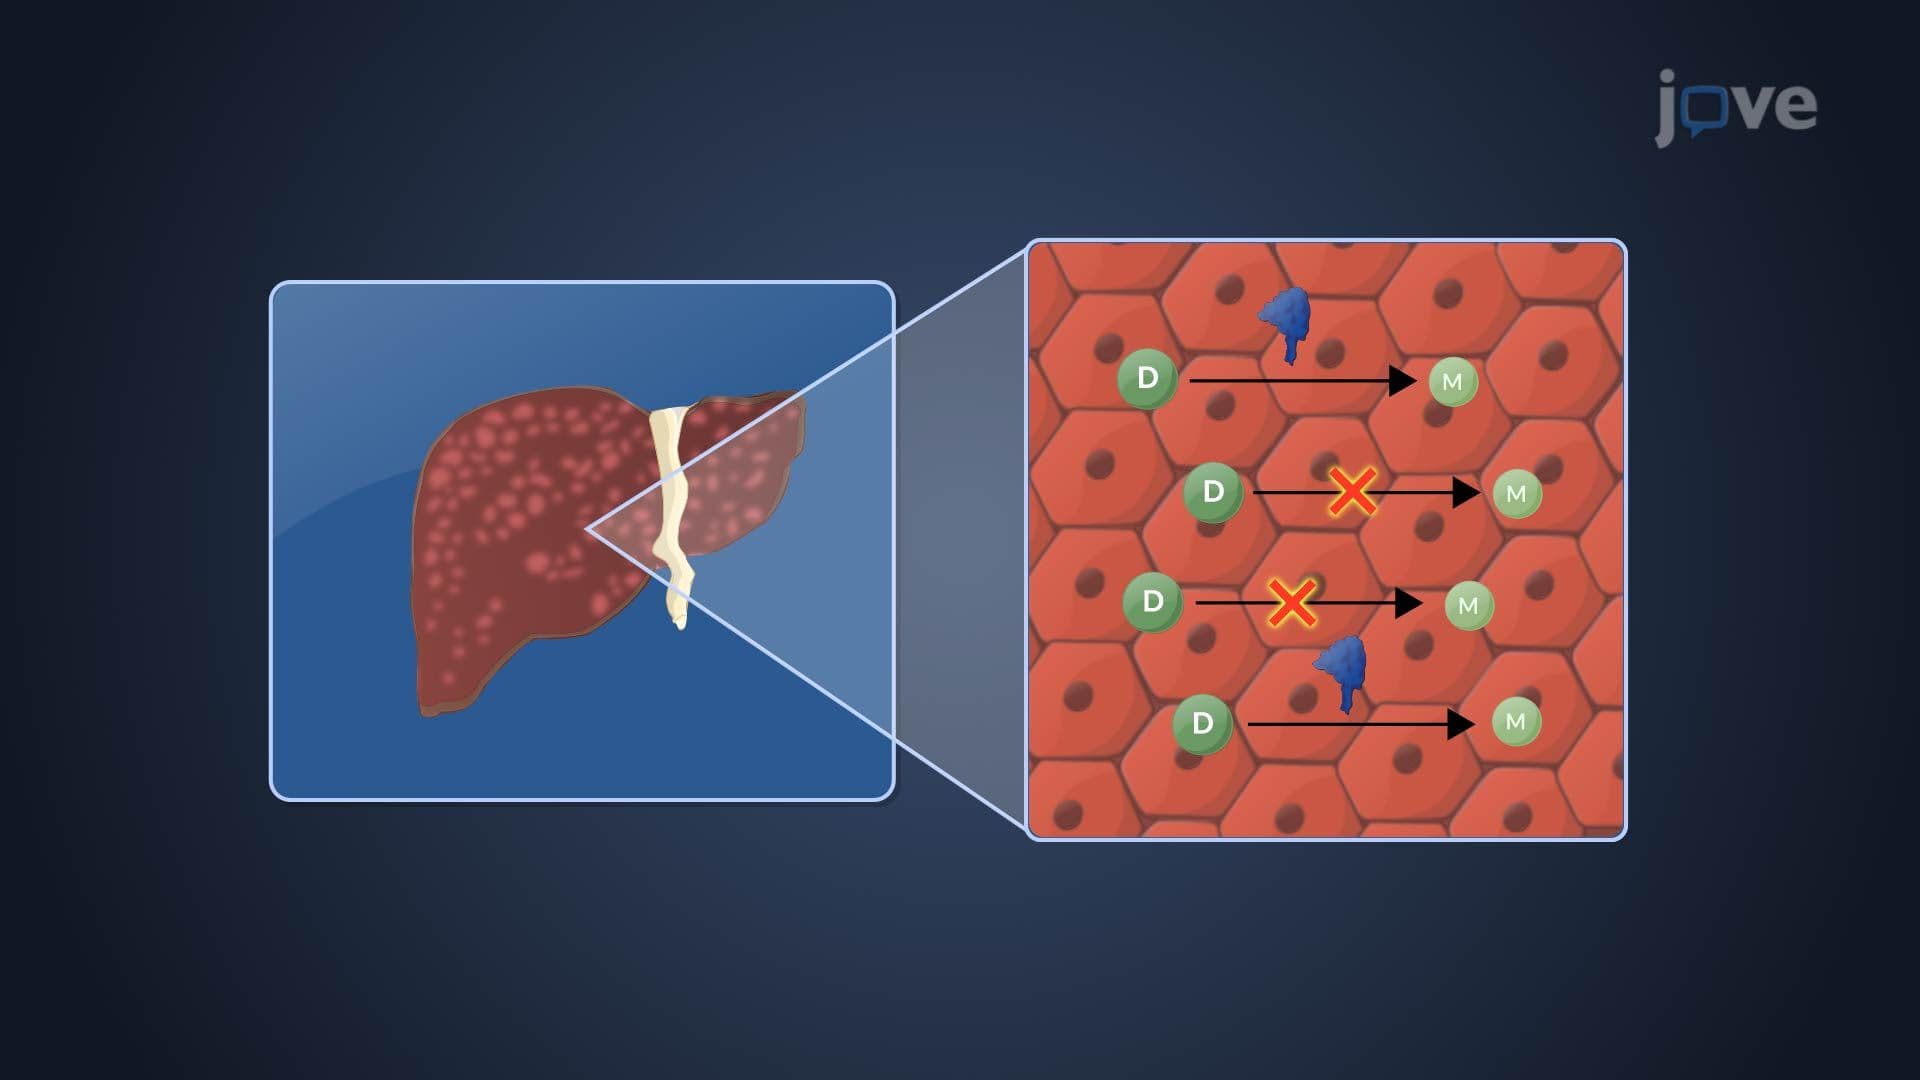
Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant