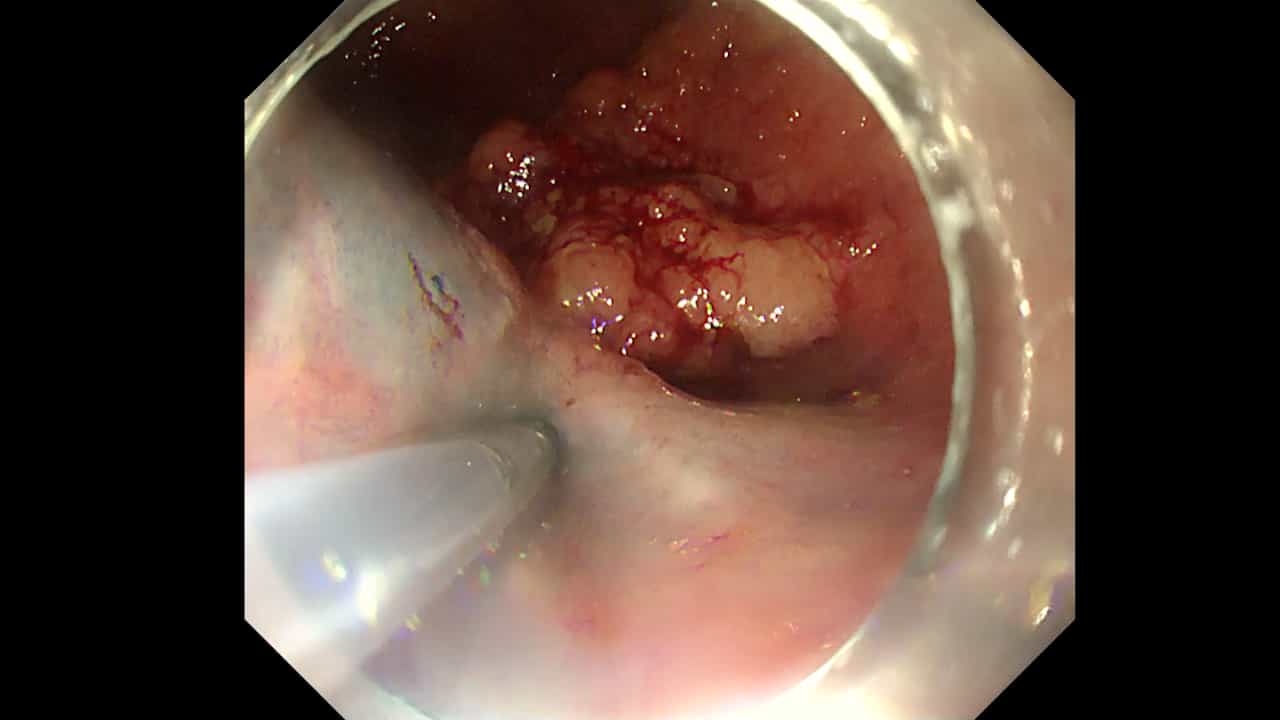
Related Experiment Video
Updated: Mar 30, 2026

ADSC-sheet Transplantation to Prevent Stricture after Extended Esophageal Endoscopic Submucosal Dissection
Published on: February 10, 2017
Clinical outcomes of circumferential endoscopic submucosal dissection for superficial esophageal squamous cell
Nan Dai1, Changqing Guo2, Ping Liu2
1Department of Gastroenterology, The First Affiliated Hospital of Zhengzhou University, Zhengzhou, Henan, China; Department of Gastroenterology, The First Affiliated Hospital of Xi'an Jiaotong University, Xi'an, Shaanxi, China.

Background And Aims:
Circumferential endoscopic submucosal dissection (C-ESD) is increasingly used for circumferential superficial esophageal squamous cell carcinoma (C-ESCC), although outcome data remain sparse. This study aimed to evaluate the short- and long-term outcomes of C-ESD in patients with C-ESCC.
Methods:
Clinical outcomes of patients with C-ESCC undergoing C-ESD at 2 Chinese centers were analyzed. Short-term outcomes included en bloc resection rate, curative resection rate, operation time, and adverse events. Long-term outcomes comprised overall survival (OS), disease-specific survival (DSS), cumulative recurrence rate (CRR), and the efficacy of stricture prevention and management.
Results:
A final assessment was conducted in 100 patients (100 lesions). The median lesion length was 5.2 cm (IQR, 4.5-6.0). Technical success rates were as follows: en bloc resection, 92.0% (95% CI, 85.0-96.4); R0 resection, 84.0% (95% CI, 75.6-90.5); and curative resection, 81.0% (95% CI, 72.3-88.3). The median procedure duration was 97.5 minutes (IQR, 70.5-138.3). Adverse events included delayed bleeding (3.0%), perforation (1.0%), and strictures (88.0%). With a median follow-up of 47.4 months (IQR, 34.3-65.2), 3- and 5-year OS and DSS were identical at 95.6% (95% CI, 91.4-99.9). Cumulative recurrence increased from 16.2% (3 years) to 19.8% (5 years). Prophylactic measures reduced stricture incidence (80% vs 100%; P = .007) and median number of endoscopic dilation sessions, 3 (IQR, 1-6) versus 4 (IQR, 3-9.8); P = .028. Stricture resolution was achieved in 95.5% of cases.
Conclusions:
C-ESD is an effective treatment for C-ESCCs. Although it achieves reliable oncological control with a favorable prognosis, its value is tempered by high stricture rates and a nonnegligible recurrence risk (∼20%). To optimize patient outcomes, advancing stricture prevention and ensuring rigorous long-term management are crucial future directions.