Related Experiment Video
Updated: Mar 31, 2026
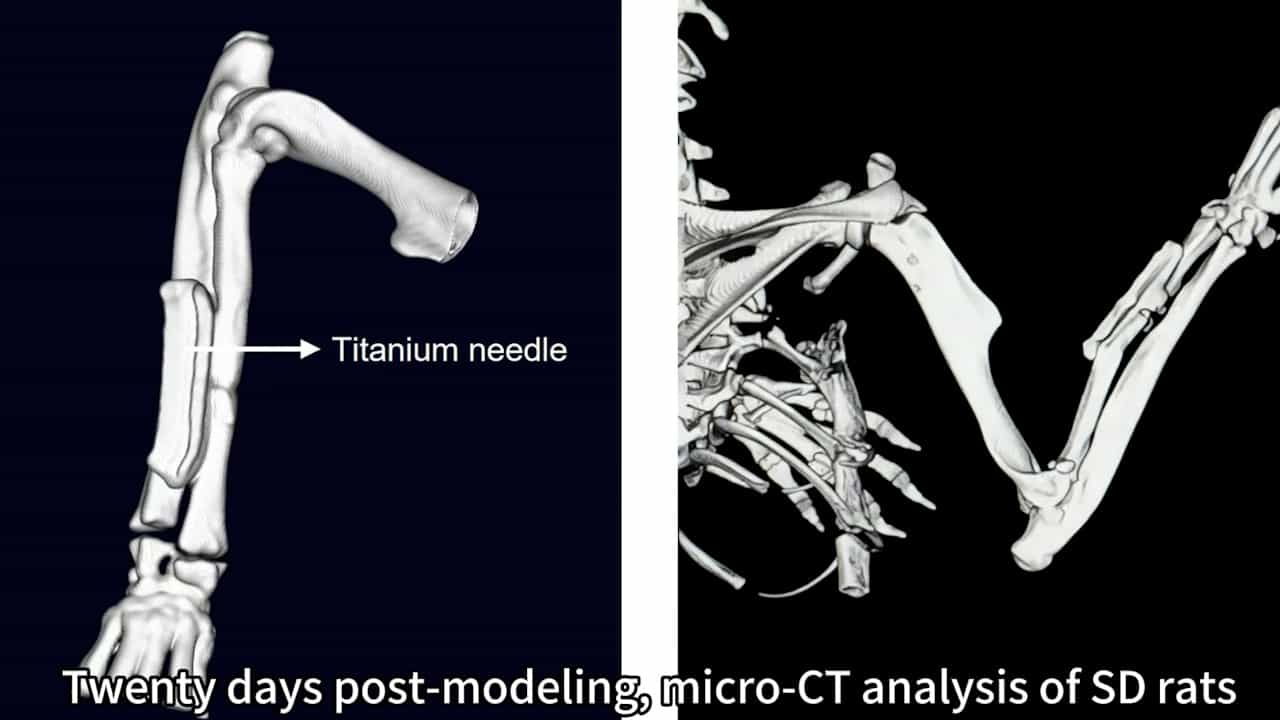

Development of a Novel Internal Fixation Model for Rat Radial Fractures: Fracture Healing Assessment and Dorsal Root Ganglion Isolation
Published on: March 13, 2026
Fracture Patterns, Skeletal Age, and Outcomes in Adolescent Supracondylar Humerus Fractures Treated With Open
Asahi Murata1, Josiah Wolf1, Michael Talerico2
1Department of Orthopedics, Nationwide Children's Hospital, Columbus, OH, USA.

Background:
Supracondylar humerus fractures (SCHF) in adolescents transitioning to skeletal maturity are less common, and literature on the management of complex cases with open reduction internal fixation (ORIF) is limited. The objective of this study was to retrospectively evaluate SCHFs treated with ORIF at a single tertiary pediatric center.
Methods:
Patients of ages 7-18 who received ORIF between 2015 and 2024 for SCHF with intercondylar extension (T-type; OTA/AO 13-E/4.2) or extraarticular SCHF (eSCHF; OTA/AO 13-M/3.1, 13/E/1.1) were included. Patients treated with percutaneous pinning alone or with prior elbow fractures were excluded. Demographic characteristics, skeletal age, injury mechanism, fracture morphology, and fixation strategy were compared. Outcomes included fracture union, range of motion (ROM), and complications. Stiffness was defined using Morrey's criteria. Final ROM was graded as defined by Jarvis et al.
Results:
Twenty-eight patients (12.7 years, 45% Female) were included and represented 3% of SCHFs in this age range. The T-type group (n = 14) was older and more skeletally mature (modified Sauvegrain score 6.8 vs 4.5; P = .003) than the eSCHF group. Plate and screw constructs were preferred in T-type fractures (9/14, 64%), while 79% (11/14) of eSCHF received cannulated screws (P = .008). All fractures achieved union (mean 11 wks). The T-type group was immobilized for a shorter period (2.3 vs 3.2 weeks; P = .043) and had more stiffness at 3 months (50 vs 9%; P = .042), but the difference in arc of motion at final follow-up did not reach statistical significance (133 vs eSCHF 142 deg; P = .07). The ROM in T-type fractures did not differ by construct type. Most patients (n = 18, 64%) were skeletally advanced compared to their chronological age (range 6-30 months). Complication rate was high (64%) primarily from hardware pain (9; 32%).
Conclusions:
T-type SCHF were seen in skeletally mature patients and were associated with slower ROM recovery. Fixation strategy was correlated with fracture type. There were no significant differences in clinical outcomes between the two fixation methods. Future prospective studies are warranted to optimize the treatment of adolescent SCHF injuries.
Key Concepts:
(1)Patients with SCHF with intraarticular extension were older and more skeletally mature.(2)Plate and screws were preferred over cannulated screws for intraarticular extension.(3)All fractures achieved union and final arc of motion did not differ by fracture type.(4)Elbows with T-type fractures were immobilized 1 week less but stiffer at 3-months.(5)Complication rate was high at 64%, and half were due to hardware pain.
Level Of Evidence:
III, Retrospective Cohort Study.
More Related Videos
 07:35
Creating Rigidly Stabilized Fractures for Assessing Intramembranous Ossification, Distraction Osteogenesis, or Healing of Critical Sized Defects
Published on: April 11, 2012
 04:41
Treatment with Locking Intramedullary Nailing for Intertrochanteric Fracture of the Femur Utilizing a New Awl with a Distal Positioner
Published on: June 6, 2025
Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...