Related Experiment Video
Updated: Apr 1, 2026
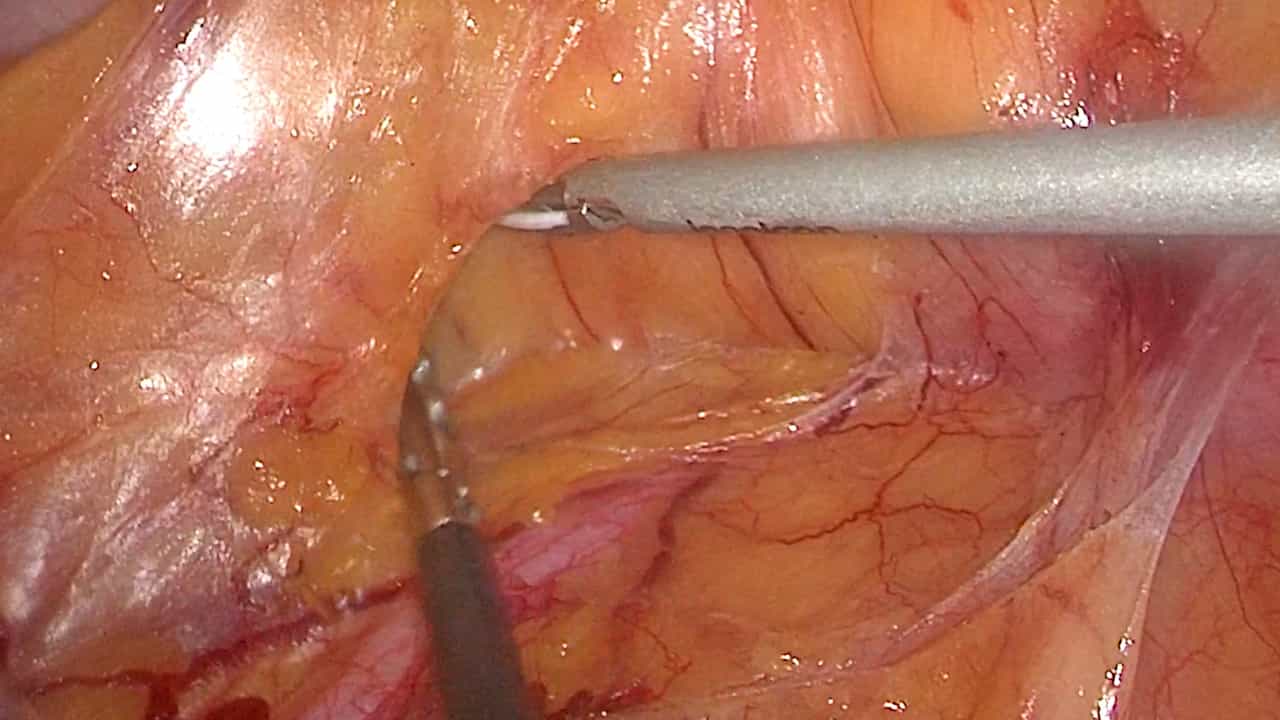

Caudal-to-cranial Approach in Laparoscopic Right Hemicolectomy with Complete Mesocolon Excision and D3 Lymph Node Dissection
Published on: January 9, 2026
Redefining the Lymphadenectomy Standard to Avoid Understaging in Oncologic Colectomies
Praveen D Chatani1, Jordan D Fredette2, James Sun1
11Department of Surgical Oncology, Fox Chase Cancer Center, Philadelphia, PA.

Background:
Accurate identification of positive lymph nodes after colectomy is essential for optimizing oncologic outcomes, as it directly informs the use of adjuvant chemotherapy in nonmetastatic colon cancer. The current lymph node target required for accurate staging has remained unchanged for decades. This study sought to identify a data-driven lymph node threshold that better optimizes oncologic outcomes.
Methods:
The National Cancer Database was queried for patients with clinically node-negative colon adenocarcinoma undergoing curative-intent resection between 2010 and 2021. Variables associated with nodal positivity were identified and the likelihood of nodal positivity with increasing lymph node examination targets was assessed.
Results:
Clinically node-negative patients who underwent curative-intent colectomy (n=195,009) were found to be node-positive in 26.3% of cases. Characteristics associated with nodal positivity included lymphovascular or perineural invasion, poor differentiation, microsatellite stability, age <50 years, and sigmoid primary. The number of nodes examined correlated with increased odds of pathologic node-positive disease at varying rates (11.2% per node for the first 10 nodes, 1.2% per node from 11-26 nodes, with no correlation beyond 26 nodes). Examination of ≥18 nodes was independently associated with pathologic nodal positivity (odds ratio [OR], 1.11), receipt of adjuvant chemotherapy (OR, 1.10), and improved median overall survival (hazard ratio, 0.88) when compared with those with 12 to 17 nodes examined (all P<.05).
Conclusions:
Our study demonstrates the superiority of a predetermined higher lymph node examination target (≥18 nodes) compared with the current standard. This target more frequently identified stage III disease and was associated with higher rates of adjuvant chemotherapy use and improved overall survival.
More Related Videos
 05:43
The Role of Anatomical Dissection in Defining Colic and Small Bowel Artery Lymphovascular Bundles in the D3 Volume of Small and Large Bowel Mesentery
Published on: August 1, 2025
 08:26
Clinical Application of Single-Surgeon, Three-Port, Laparoscopic Resection for Colorectal Cancer with Natural Orifice Specimen Extraction
Published on: March 24, 2023