Related Experiment Video
Updated: Jul 6, 2026
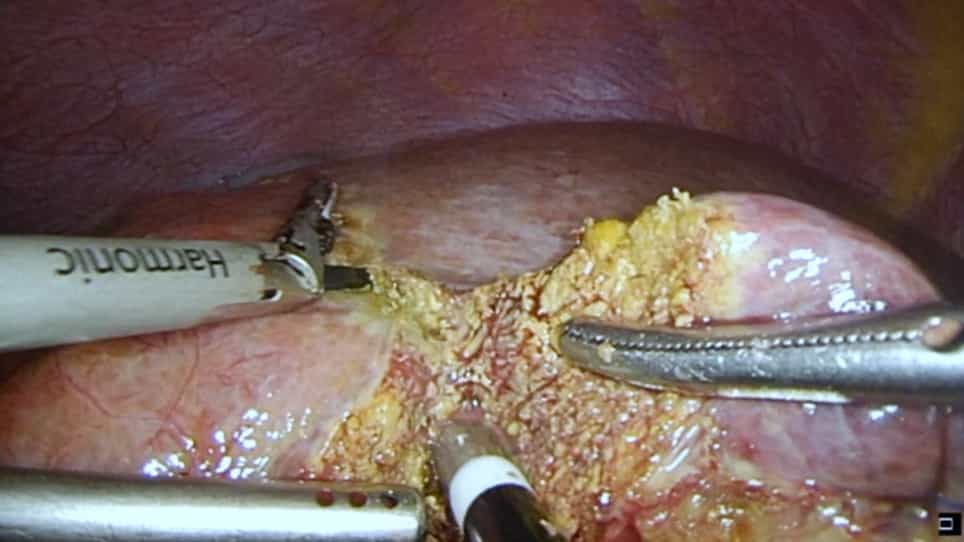

Application of Hemostatic Devices in Laparoscopic Hepatectomy
Published on: April 19, 2022
Delayed Port-Site Hematoma Following Robot-Assisted Hysterectomy Using the Hinotori Surgical Robot System in an
Yoshiko Kawata1, Kenbun Sone1, Yuichiro Miyamoto1
1Department of Obstetrics and Gynecology, The University of Tokyo Hospital, Tokyo, JPN.

Perioperative management of patients on anticoagulation therapy requires careful balancing of the thromboembolic and bleeding risks. Heparin bridging is considered for high-risk patients; however, it may increase the incidence of postoperative bleeding complications. We report the case of a 74-year-old woman with stage IA endometrial cancer and cardiovascular comorbidities, including atrial fibrillation and mitral stenosis, who was receiving warfarin therapy. She underwent robot-assisted laparoscopic hysterectomy using the Hinotori surgical robot system with heparin bridging. On postoperative day 5, after restarting both heparin and warfarin, the patient developed a 9-cm subcutaneous hematoma at the right lower abdominal port site. Contrast-enhanced computed tomography suggested bleeding from a perforating branch of the inferior epigastric artery. Anticoagulation was interrupted, and local compression achieved hemostasis. After cautious reinitiation of anticoagulation therapy, the patient was discharged on postoperative day 14 without recurrent bleeding. This case highlights the importance of careful interpretation of activated partial thromboplastin time during heparin bridging in patients receiving warfarin, as additive anticoagulant effects may lead to excessive anticoagulation. In addition, preoperative imaging assessment of abdominal wall vasculature and careful port placement are essential to prevent delayed port-site hemorrhage during robot-assisted surgery.
Perioperative management of patients on anticoagulation therapy requires careful balancing of the thromboembolic and bleeding risks. Heparin bridging is considered for high-risk patients; however, it may increase the incidence of postoperative bleeding complications. We report the case of a 74-year-old woman with stage IA endometrial cancer and cardiovascular comorbidities, including atrial fibrillation and mitral stenosis, who was receiving warfarin therapy. She underwent robot-assisted laparoscopic hysterectomy using the Hinotori surgical robot system with heparin bridging. On postoperative day 5, after restarting both heparin and warfarin, the patient developed a 9-cm subcutaneous hematoma at the right lower abdominal port site. Contrast-enhanced computed tomography suggested bleeding from a perforating branch of the inferior epigastric artery. Anticoagulation was interrupted, and local compression achieved hemostasis. After cautious reinitiation of anticoagulation therapy, the patient was discharged on postoperative day 14 without recurrent bleeding. This case highlights the importance of careful interpretation of activated partial thromboplastin time during heparin bridging in patients receiving warfarin, as additive anticoagulant effects may lead to excessive anticoagulation. In addition, preoperative imaging assessment of abdominal wall vasculature and careful port placement are essential to prevent delayed port-site hemorrhage during robot-assisted surgery.