Related Experiment Video
Updated: Apr 2, 2026


Investigation into Deep Breathing through Measurement of Ventilatory Parameters and Observation of Breathing Patterns
Published on: September 16, 2019
Effect of manual diaphragmatic release on ventilatory function and quality of life in women with rheumatoid
Saher Lotfy Elgayar1, Mohamed Bayoumi Ibrahim Bayoumi1,2
1Department of Physiotherapy, Faculty of Allied Medical Sciences, Middle East University, Amman, Jordan.

Introduction:
Rheumatoid arthritis (RA) could lead to several respiratory dysfunctions, impairing quality of life.
Objective:
To evaluate the effect of manual diaphragmatic release (MDR) added to aerobic training (AT) on ventilatory function, diaphragmatic motion, aerobic capacity, and quality of life, compared with AT alone, in women with RA.
Methods:
Eighty women with RA were equally assigned to either the MDR group, which received MDR and AT, or the control group, which received AT only, for 8 weeks. Outcomes included forced vital capacity (FVC) and total lung capacity (TLC), diaphragmatic motion, maximal oxygen consumption (Vo2max), and the Rheumatoid Arthritis Quality of Life Questionnaire (RA QoL).
Results:
Analysis was conducted using ANCOVA. Relative to the controls, the MDR group showed significantly greater post-study FVC (mean difference (MD) = 3.99%; 95% CI: 1.14 to 6.83; p = 0.007), TLC (MD = 3.75%; 95% CI: 1.10 to 6.41; p = 0.006), diaphragmatic motion (MD = 7.5 mm; 95% CI: 1.11 to 9.89; p = 0.001), and Vo2max (MD = 5.02 ml/kg/min; 95% CI: 1.19 to 8.4; p = 0.01), along with a significantly lower RA QoL score (MD = -3.64; 95% CI: -5.39 to -1.9; p = 0.001).
Conclusion:
In women with RA, adding MDR to AT was more effective than AT alone in improving ventilatory function, diaphragmatic motion, aerobic capacity, and quality of life.
Trial Registration:
ClinicalTrials.gov, prospective, NCT06716008.
More Related Videos
Related Concept Videos
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:15
Respiratory Volumes
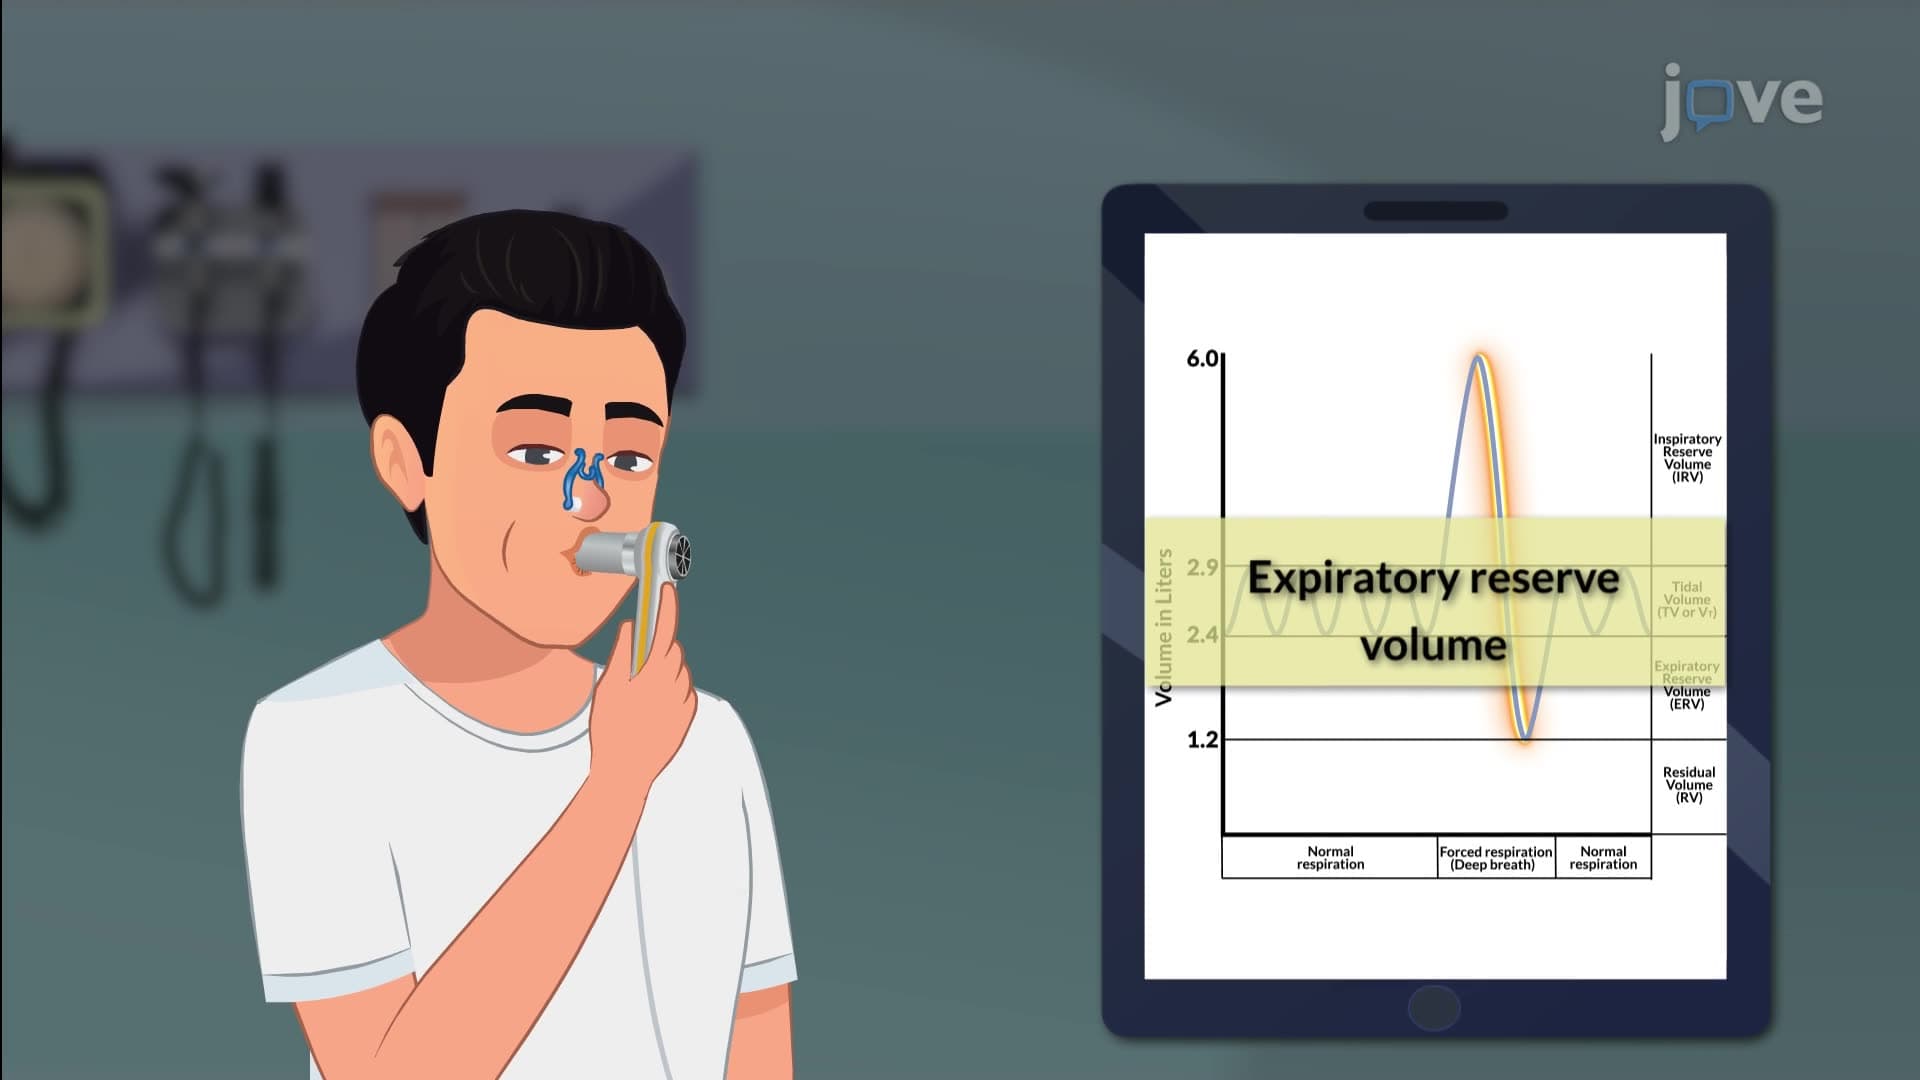
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation: