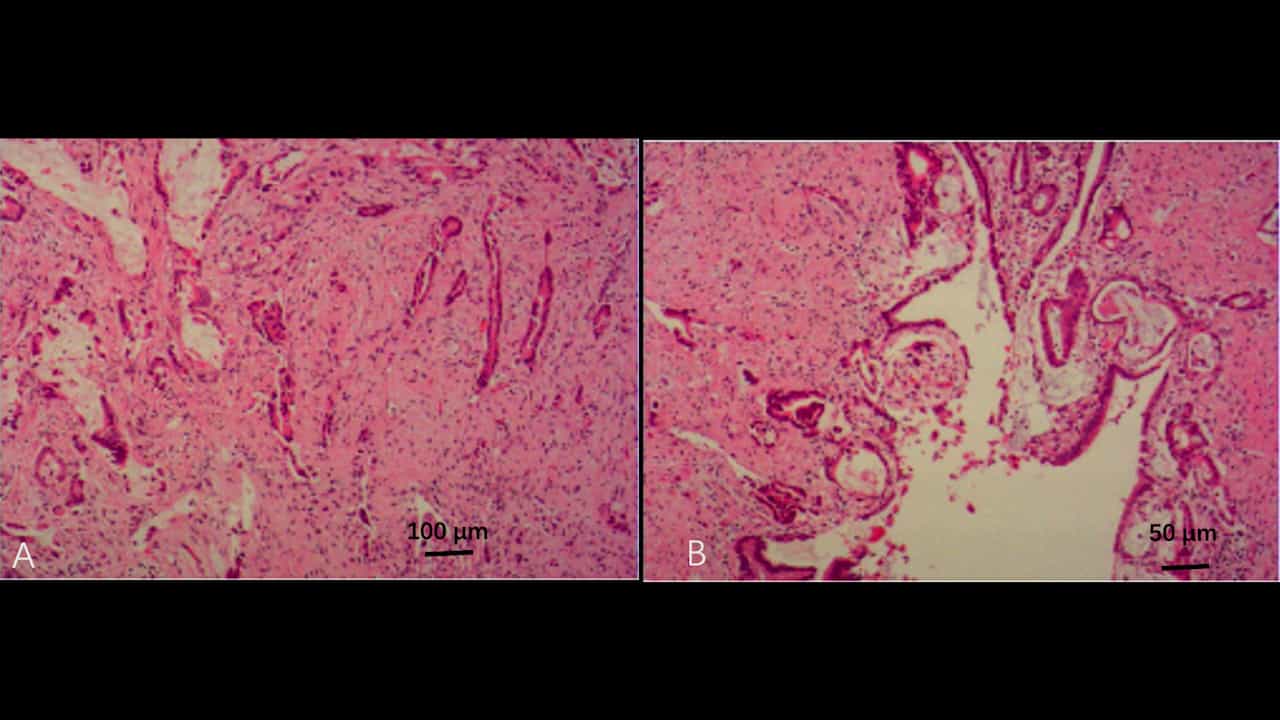
Adolescent Epstein-Barr virus-associated cholestatic jaundice with porta hepatis/pancreatic head lymphadenopathy and
Ying Chen1, Bo Liu2, Xiaoyu Zhu1
1Department of Gastroenterology, Yibin Hospital Affiliated to Children's Hospital of Chongqing Medical University, Yibin, China.

Background:
Cholestatic jaundice is uncommon in adolescents. Epstein-Barr virus (EBV)-related inflammatory lymphadenopathy can mimic malignant biliary obstruction and cause a transient rise in carbohydrate antigen 19-9 (CA 19-9), complicating diagnosis.
Case Presentation:
A previously healthy 15-year-old girl presented with 6 days of jaundice and dark urine without fever. Physical examination showed moderate generalized jaundice with mild scleral icterus; multiple mobile, non-tender lymph nodes in the bilateral cervical regions and right post-auricular area (largest ∼2 × 2 cm); palpable liver and spleen; and mild right upper-quadrant tenderness with equivocal Murphy's sign. Initial tests showed a cholestatic pattern (total/direct bilirubin 102.4/67.7 μmol/L at the referring hospital; and 133.2/126.3 μmol/L on admission) with elevated ALP/GGT and total bile acids. CT suggested a porta hepatis-to-pancreatic-head soft-tissue density with mild intrahepatic ductal prominence; CA 19-9 was 117.7 U/mL [ref <37 U/mL]. EBV POCT was positive; EBV DNA was detected at low level. MRI/MRCP (2025-09-29) showed no obvious biliary obstruction. After MRCP excluded fixed biliary obstruction, the patient improved with conservative management (diagnostic evaluation, close monitoring, and symptom-directed care) without invasive intervention; CA 19-9 declined. No causal inference regarding any medication effect should be drawn, and we do not recommend self-medication or routine off-label/unlicensed use of cholestasis-directed agents for EBV infection. In immunocompetent hosts, EBV-related lymphadenopathy is usually self-limited, and this case does not represent EBV-associated lymphoproliferative disease.
Conclusion:
EBV-related cholestatic hepatitis in adolescents can present with transient CA 19-9 elevation and reactive porta hepatis/pancreatic head lymphadenopathy, mimicking malignant obstruction. Serial laboratory and imaging assessments-particularly MRCP-together with conservative management may obviate unnecessary invasive procedures.

Related Concept Videos
 01:26
Diseases of the Liver and Gallbladder
Cirrhosis is characterized by the scarring of hepatic lobules in the liver, which are replaced by fibrous tissue, affecting the liver's normal functioning. NAFLD, on the other hand, is caused by an excessive build-up of fat in the liver, not...
 01:25
Hepatitis
 01:21
Hepatic Portal System
At its core, the hepatic portal vein is the result of a confluence of the superior and inferior mesenteric veins along with the splenic vein. Each of these veins has a unique role. The superior mesenteric vein is...