Related Experiment Video
Updated: Apr 3, 2026
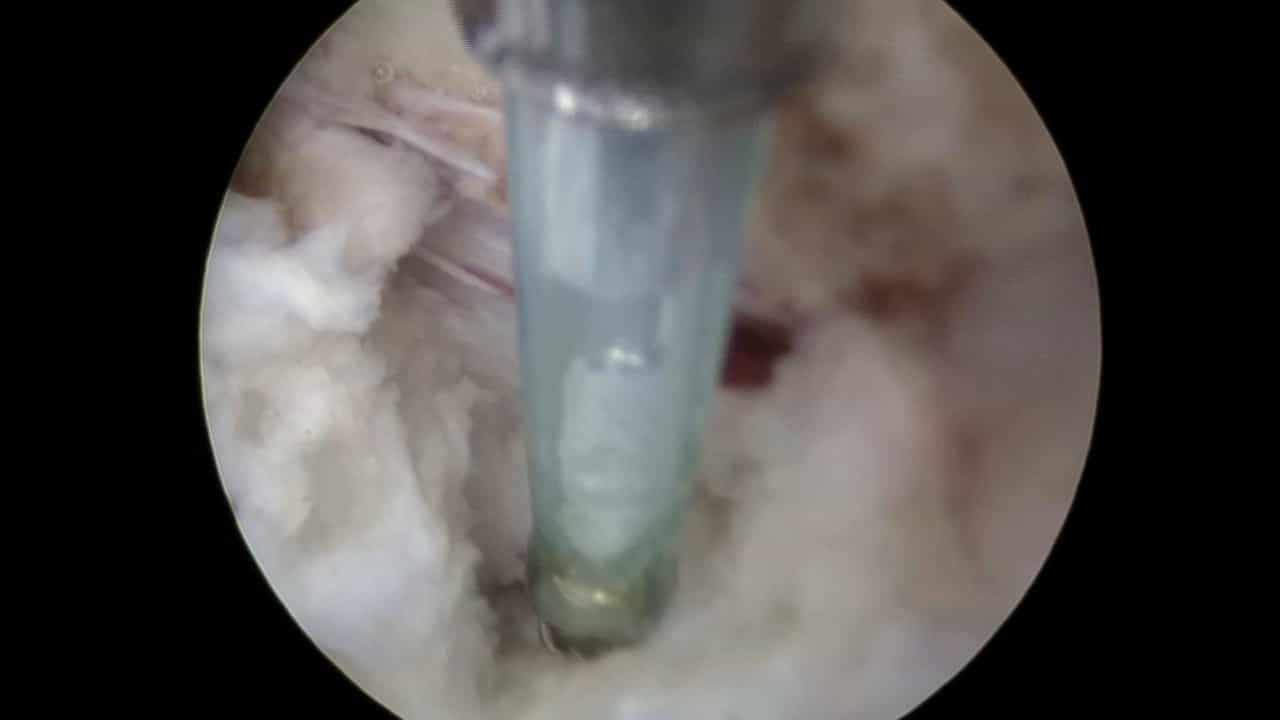

Full-Endoscopic Transforaminal Approach for Lumbar Discectomy
Published on: September 8, 2023
Can we move thoracic disc surgery to the ambulatory setting? The role of endoscopy
Harsh Jain1, Advith Sarikonda1, James F Bathon2,3
11Department of Neurological Surgery, Vanderbilt University Medical Center, Nashville.

Objective:
While surgery for thoracic disc herniation causing spinal cord compression has traditionally been an inpatient procedure, fraught with risk and often requiring multilevel fusion, recent advances in endoscopic surgery challenge this paradigm. This study presents a single-surgeon case series of endoscopic thoracic discectomy performed in an ambulatory setting, outlining 1) the surgical technique, 2) patient selection and characteristics, and 3) postoperative outcomes. The goal of this study was to assess the safety and feasibility of performing endoscopic thoracic discectomy in an ambulatory surgery setting.
Methods:
A single-surgeon retrospective case series of patients undergoing endoscopic thoracic discectomy at an ambulatory surgery center between 2023 and 2025 was analyzed. Giant calcified discs causing spinal cord compression were excluded. Demographics, comorbidities, operative details, and postoperative outcomes were collected. Primary outcomes included surgical site infection, 90-day emergency department visit, readmission, and reoperation. Patient-Reported Outcomes Measurement Information System-29 (PROMIS-29) physical function scores were compared between baseline and 3 months. Descriptive analysis was performed.
Results:
Of the 39 patients undergoing endoscopic thoracic discectomy at an ambulatory surgery center, the mean age was 54.9 (SD 14.3) years, and 46.2% were male. Discectomy was performed at a single level in 92.3% of cases, most commonly T7-8 (26.2%), T12-L1 (16.7%), and T11-12 (14.3%). Preoperatively, 84.6% of patients had spinal cord compression, 23 (59.0%) were myelopathic, and 24 (61.5%) had a motor deficit. The mean operative duration was 107.6 (SD 46.4) minutes and the mean estimated blood loss was 12.7 (SD 19.1) ml. A dural tear in 1 patient was the only intraoperative complication. Regarding postoperative complications, 2 patients (5.1%) underwent reoperation, for a retained disc fragment in 1 patient and a CSF leak in the other. No surgical site infections were observed. PROMIS-29 physical function scores improved significantly from baseline (mean 35.1 [SD 7.3]) to 3 months (mean 41.6 [SD 8.0]; p = 0.004).
Conclusions:
In a single-surgeon series, endoscopic thoracic discectomies performed in an ambulatory surgery center were safe and feasible, with low perioperative morbidity, minimal blood loss, and meaningful early functional improvement. Where conventional management typically demands multilevel fusion or costotransversectomy, with a multiday hospital stay, endoscopic techniques offer a transformative alternative, making thoracic disc surgery safe and feasible even in outpatient environments.
Related Concept Videos
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due...
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...