Related Experiment Video
Updated: Apr 3, 2026
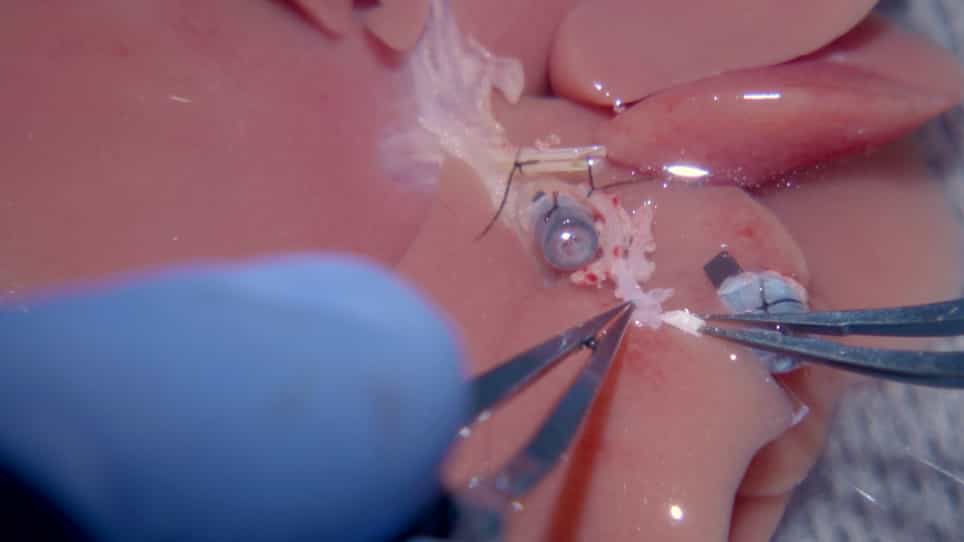

Reduced Complications after Arterial Reconnection in a Rat Model of Orthotopic Liver Transplantation
Published on: November 7, 2020
Achieving zero waitlist mortality for children on the pediatric liver transplant waitlist
Elizabeth King1, Carolyn Reuland1, Bhargava Mullapudi2
1Department of Surgery, Johns Hopkins University Hospital, Baltimore, Maryland, USA.

Insights
Pediatric liver transplant waitlists are dangerous for children. Promoting living donor liver transplantation (LDLT) and mandatory liver-splitting policies can save lives and increase organ availability for pediatric patients.
Area of Science:
- Pediatric Hepatology
- Transplantation Surgery
- Public Health Policy
Background:
- Children with end-stage liver disease face high waitlist mortality, especially infants under one year.
- Pediatric liver transplant candidates receive fewer organ offers and experience longer wait times than adults, impacting development.
- Current strategies to increase organ availability for children have been insufficient.
Purpose of the Study:
- To recommend strategies for increasing liver organ availability and reducing waitlist mortality in pediatric patients.
- To advocate for increased utilization of living donor liver transplantation (LDLT) and mandatory liver-splitting policies.
- To highlight the potential of split-liver grafts to improve outcomes and reduce waitlist times.
Main Methods:
- Review of current pediatric liver transplantation statistics in the US and international comparisons (e.g., Canada, UK).
- Analysis of the underutilization of living donor liver transplantation (LDLT) and split-liver grafts in the US.
- Examination of outcomes for split-liver versus whole-liver grafts in pediatric and adult populations.
Main Results:
- Living donor liver transplantation (LDLT) accounts for only 14.6% of pediatric transplants in the US, significantly lower than in Canada (46.2%).
- Fewer than 5% of potentially splitable livers are used for split-liver transplantation in the US, while over 65% are used in the UK.
- Outcomes for split-liver and whole-liver grafts are comparable in both pediatric and adult recipients.
Conclusions:
- Increased utilization of LDLT and adoption of mandatory liver-splitting policies are recommended to safeguard children awaiting liver transplants.
- These strategies could significantly decrease pediatric waitlist mortality and increase the number of liver transplants performed.
- Implementing a center-based allocation system can further support these goals by reducing cold ischemia time and enhancing liver availability.
Abstract:
Children with end-stage liver disease are at high risk of waitlist morbidity and mortality; children <1 year have the highest mortality of all age groups in the United States (US) (18.6 deaths per 100 patient-years). Pediatric candidates receive fewer offers of organs than adults, and excessive wait times contribute to delays in development that can have a lasting impact. Policy changes and outreach efforts have been insufficient to increase organ availability for children. Living donor liver transplantation (LDLT) is underutilized in the US, accounting for 14.6% of all pediatric transplants in 2023, compared with 46.2% in Canada. The ASTS Pediatric Committee therefore recommends promoting increased utilization of LDLT and incentivization and adoption of mandatory liver-splitting policies to safeguard these children, which could decrease pediatric waitlist mortality while increasing the number of liver transplants performed. Outcomes are similar between recipients of split-liver and whole-liver grafts in both pediatric and adult populations, but fewer than 5% of potentially splitable livers are currently used for split-liver transplantation in the US. In contrast, over 65% of pediatric patients in the United Kingdom receive a split-liver allograft, with excellent survival. Use of a center-based allocation system will support this mandate by reducing cold ischemia time and increasing liver availability.
Related Concept Videos
 01:28
Kidney Transplant I: Introduction
 01:26
Kidney Transplant II: Surgical Procedure
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:22
Bone Marrow Sampling and Transplants
The transplant begins with high doses of chemotherapy and radiation treatment, which aim to destroy...
 01:16
Kidney Transplant III: Nursing Management