Related Experiment Video
Updated: Apr 3, 2026

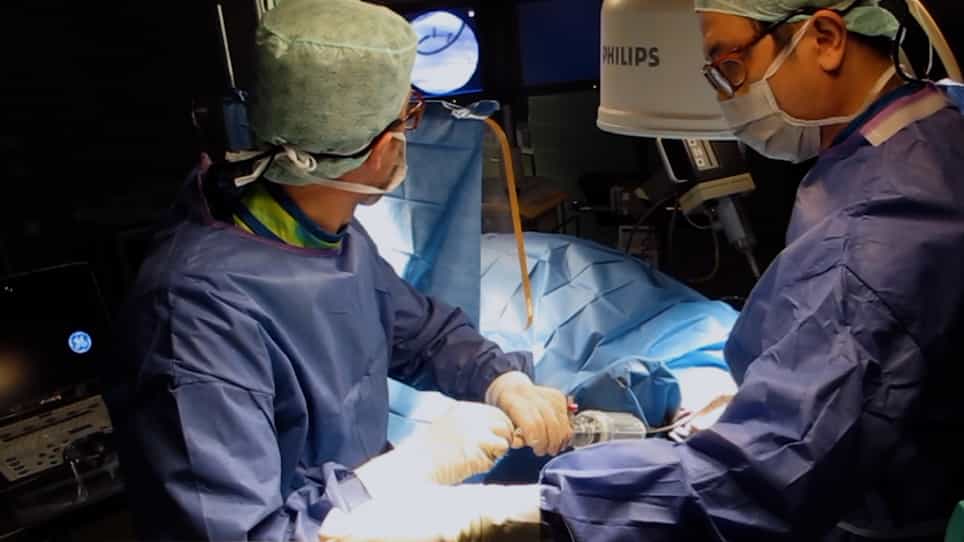
Upper-extremity Approach for Secondary Access in Transfemoral Transcatheter Aortic Valve Implantation
Published on: August 8, 2025
Safety and efficacy of transcatheter aortic valve replacement for native pure aortic valve regurgitation
Giulio Giovanni Cavalli1,2, Albino Vallabini1, Maurizio Braccio1
1Division of Cardiac, Minimally Invasive and Transcatheter Surgery, IRCCS Ospedale Casa Sollievo della Sofferenza, San Giovanni Rotondo, Foggia.

Aims:
Transcatheter aortic valve replacement has become the standard of care for high-risk patients with aortic stenosis. Considering the unique procedural challenges posed by native pure aortic regurgitation (NPAR), our aim was to evaluate the early and mid-term results of off-label transcatheter aortic valve replacement (TAVR), investigating the possibility of brief Veno-Arterial extracorporeal membrane oxygenation (VA ECMO) support for most complex procedures.
Methods:
We retrospectively enrolled 65 consecutive patients, who underwent TAVR for NPAR because they were deemed ineligible for surgery. Patients with aortic valve calcification or stenosis were excluded. Primary endpoints were technical and device success according to the VARC-3 criteria. Secondary endpoints were clinical efficacy at 1 year and absence of at least moderate paravalvular leak.
Results:
Patients' mean age was 76.15 ± 8.91. We adopted light sedation and local anesthesia in 60 patients (92.3%). High-risk patients (53.8%) were briefly supported with percutaneous femoro-femoral VA ECMO, allowing safer and more precise valve deployment. One intraprocedural death was recorded (1.5%). Although the overall 30-day mortality was 7.7%, primary composite outcomes were significantly better in the second half of the population ( P = 0.023 and P = 0.026). Only one moderate paravalvular leak (1.5%) was detected at 1-month follow-up. Clinical efficacy at 1 year was 76.3%, being available for 38 patients.
Conclusion:
TAVR is still considered an off-label approach for NPAR because of the increased stroke volume and absence of annular and leaflet calcification, which might increase the complication rate. Nonetheless, a standardized approach, with the aid of brief VA ECMO support for complex cases, should be considered a safe and valid option in high-volume centers for inoperable patients.
More Related Videos
 05:31
Transcatheter Pulmonary Valve Replacement from Autologous Pericardium with a Self-Expandable Nitinol Stent in an Adult Sheep Model
Published on: June 8, 2022
 14:14
Standardized Technique of Aortic Valve Re-implantation for Valve-sparing Aortic Root Replacement
Published on: December 11, 2017
Related Concept Videos
 01:25
Aortic Regurgitation III: Medical Management
 01:15
Aortic Regurgitation I: Introduction
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:17
Aortic Regurgitation IV: Nursing Management
 01:25
Mitral Regurgitation III: Medical Management