Related Experiment Video
Updated: Jul 4, 2026
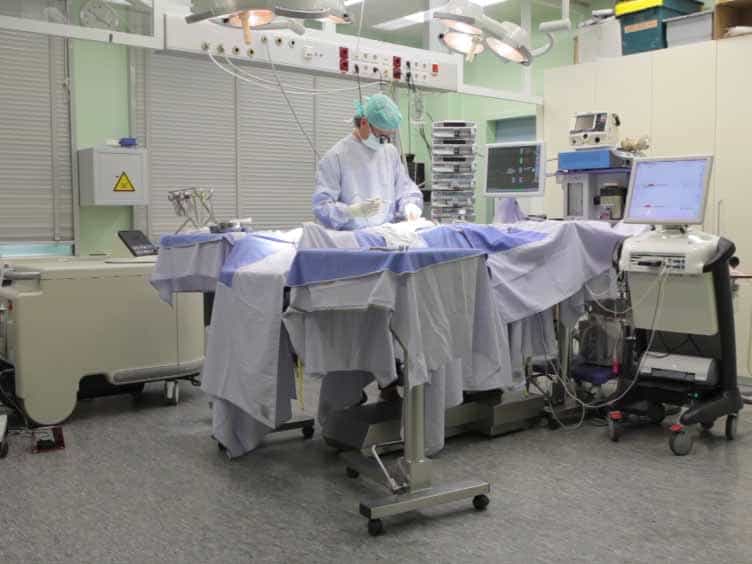
Evaluation of a Novel Laser-assisted Coronary Anastomotic Connector - the Trinity Clip - in a Porcine Off-pump Bypass Model
Published on: November 24, 2014
Percutaneous coronary intervention versus coronary artery bypass grafting for unprotected left main stenosis: 10-year
Emil Nielsen Holck1, Niels R Holm2, David Hildick-Smith3
1Department of Cardiology, Aarhus University Hospital, Aarhus, Denmark; Department of Clinical Medicine, Aarhus University, Aarhus, Denmark.

Insights
Percutaneous coronary intervention (PCI) and coronary artery bypass grafting (CABG) show similar 10-year survival rates for unprotected left main coronary artery disease. This finding supports individualized treatment strategies for patients eligible for both procedures.
Area of Science:
- Cardiovascular Medicine
- Interventional Cardiology
- Cardiac Surgery
Background:
- Coronary artery bypass grafting (CABG) is often recommended for significant unprotected left main coronary artery disease.
- Long-term outcome data comparing PCI with newer generation drug-eluting stents and CABG are limited.
Purpose of the Study:
- To compare the long-term outcomes of PCI versus CABG in patients with unprotected left main coronary artery disease.
- To provide data to aid heart teams in developing individualized patient-centered strategies.
Main Methods:
- A prospective, randomized, open-label, non-inferiority trial involving 1201 patients across 36 hospitals.
- Patients with unprotected left main coronary artery stenosis were randomly assigned (1:1) to PCI or CABG.
- The primary outcome was the difference in 10-year all-cause mortality analyzed using Kaplan-Meier estimates and Cox regression.
Main Results:
- No significant difference in 10-year all-cause mortality between PCI (23%) and CABG (25%) groups (HR 0.93; p=0.56).
- 1201 patients were randomized; 592 in each group were included in the intention-to-treat analysis.
- No significant difference in mortality was identified based on SYNTAX score.
Conclusions:
- PCI is as safe as CABG in patients with unprotected left main coronary artery disease and no additional complex lesions.
- The study supports shared decision-making for PCI versus CABG in eligible patients.
- Results aid in developing individualized patient-centered treatment strategies.
Background:
Coronary artery bypass grafting (CABG) is recommended over percutaneous coronary intervention (PCI) for patients with significant unprotected left main coronary artery disease. We aim to provide long-term outcome data comparing PCI with newer generation drug-eluting stents and CABG, which are scarce.
Methods:
This previously published, prospective, randomised, open-label, non-inferiority trial enrolled patients with unprotected left main coronary artery stenosis at 36 hospitals in Denmark, Estonia, Finland, Germany, Latvia, Lithuania, Norway, Sweden, and the UK. Eligibility was determined by a multidisciplinary heart team and defined by clinical criteria (chronic or acute coronary syndrome and a life expectancy of >1 year) and angiographic criteria (left main coronary artery diameter stenosis ≥50% or fractional flow reserve ≤0·80 in the left main ostium, mid-shaft, or bifurcation). Patients with ST elevation myocardial infarction within 24 h or considered at too high risk for CABG or PCI were excluded. Patients with angiographically confirmed significant left main coronary artery disease were randomly assigned (1:1) to PCI or CABG using an online system and stratified by site, sex, distal left main coronary artery bifurcation lesions, and diabetes. The primary outcome was the difference in 10-year all-cause mortality in the intention-to-treat (ITT) population, which was analysed using Kaplan-Meier estimates and unadjusted Cox regression. Patients were censored at the date of death, emigration, withdrawal, or loss to follow-up. Variation in all-cause mortality was assessed in prespecified subgroups. The trial is registered with ClinicalTrials.gov, NCT01496651 (active, not recruiting).
Findings:
From Dec 9, 2008, to Jan 21, 2015, 1201 patients were randomly assigned to PCI (n=598) or CABG (n=603). 17 patients were lost to follow-up before 1 year. 592 patients in each group were included in the ITT population. Mean age was 66·2 years (SD 9·9) in the PCI group and 66·2 years (9·4) in the CABG group. 256 (22%) of 1184 participants were female and 928 (78%) were male. There was no difference in all-cause mortality at 10 years (136 [23%] of 592 in the PCI group and 145 [25%] of 592 in the CABG group; hazard ratio 0·93 [95% CI 0·74-1·18]; p=0·56). No significant difference in all-cause mortality with SYNTAX score was identified.
Interpretation:
There was no significant difference in all-cause mortality at 10 years between PCI and CABG for patients with unprotected left main coronary artery disease and no additional complex lesions, indicating that PCI is equally as safe as CABG in patients eligible for both treatments. These results will aid heart teams in developing an individualised patient-centred strategy.
Funding:
Biosensors and Aarhus University Hospital.
More Related Videos


Related Concept Videos
 01:27
Coronary Artery Disease V: Interprofessional Care
 01:30
Acute Coronary Syndrome III: Diagnostic Studies