Related Experiment Video
Updated: Apr 7, 2026
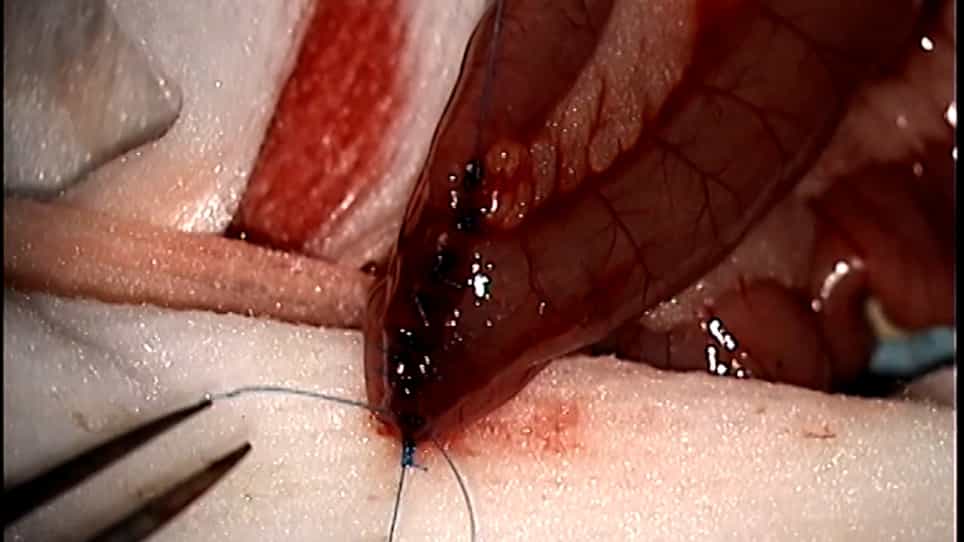

A Protocol for Roux-en-Y Gastric Bypass in Rats using Linear Staplers
Published on: August 21, 2021
Surgical Options for Refractory Anastomotic Ulcer after Roux-en-Y Gastric Bypass: A Narrative Review of the
Patrick Noel1, Christophe Cazeres2, Rami Edward Lutfi3
1Hopital Privé Bouchard Elsan, Marseille, France.

Background:
Marginal ulcer (MU) is a well-recognized complication following Roux-en-Y gastric bypass (RYGB), with a reported prevalence of 0.6%-16%. While most ulcers respond to medical therapy with proton pump inhibitors and risk factor modification, a subset of patients develop refractory ulcers requiring surgical intervention. Despite this clinical challenge, there remains no consensus on the optimal surgical approach for refractory MU.
Methods:
We performed a narrative review of the literature using PubMed, MEDLINE, and Google Scholar databases from January 2000 to December 2024. Search terms included marginal ulcer, anastomotic ulcer, gastric bypass, refractory ulcer, surgical treatment, vagotomy, and revisional surgery. We focused on studies reporting surgical outcomes for refractory MU after RYGB.
Results:
Current surgical options include (1) gastrojejunostomy revision with or without pouch reduction, (2) truncal vagotomy (laparoscopic or thoracoscopic), (3) subtotal or total gastrectomy with esophagojejunostomy, (4) gastric remnant resection, and (5) RYGB reversal with or without conversion to sleeve gastrectomy. Reported success rates vary from 36% to 100% depending on technique and follow-up duration. Recurrence rates remain concerning, ranging from 15% to 57% at 1 year. Risk factors for recurrence include persistent smoking (HR: 5.03), immunosuppression (HR: 4.60), and Nonsteroidal anti-inflammatory drug (NSAID) use (HR: 3.11). Emerging endoscopic approaches, including suturing and stent deployment, show promise as step-up therapy before surgical revision.
Conclusions:
The management of refractory MU after RYGB remains challenging with no single optimal surgical approach. Treatment should be individualized based on ulcer characteristics, the presence of associated complications (gastrogastric fistula and stricture), and patient risk factors. A stepwise algorithm incorporating endoscopic therapy, gastrojejunostomy revision, and salvage procedures is proposed.


Related Concept Videos
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...
 01:26
Aneurysm III: Interprofessional Care