Related Experiment Video
Updated: May 18, 2026
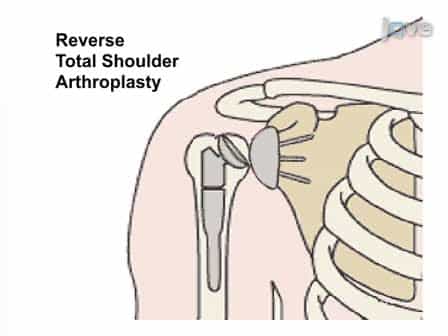
Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Optimizing reverse total shoulder arthroplasty for combined loss of elevation and external rotation: latissimus dorsi
Gaku Matsuzawa1,2, Taku Hatta3, Koichi Sasajima2
1Department of Orthopaedic Surgery, Tome Citizen Hospital, Tome, Japan.

Background:
Large to massive rotator cuff tears (RCTs) can lead to combined loss of active elevation and external rotation (CLEER), particularly when accompanied by severe fatty change of the external rotators. In such cases, reverse total shoulder arthroplasty (rTSA) may be insufficient, and adjunctive latissimus dorsi and teres major (LD/TM) transfer or lateralization is often considered, though their relative benefits remain unclear.
Methods:
This retrospective study included 38 shoulders from 38 patients with combined loss of active elevation and external rotation due to large to massive RCTs and severe fatty change of the infraspinatus and teres minor. All patients underwent rTSA and were followed for a minimum of 2 years. Patients were categorized into 4 groups based on the humeral component design and whether LD/TM transfer was performed: inlay component without muscle transfer (In group), onlay component without muscle transfer (On group), inlay component with muscle transfer (InT group), and onlay component with muscle transfer (OnT group). Lateralization was assessed radiographically by measuring the distance from the glenoid to the humeral component center and the greater tuberosity. Post-operative outcomes were evaluated in terms of active range of motion, the American Shoulder and Elbow Surgeons (ASES) score, and the Constant-Murley score. Radiographic and clinical results were compared across groups. Each outcome was evaluated relative to its minimum clinically important difference (MCID).
Results:
The In, On, InT, and OnT groups included 9, 7, 10, and 12 patients, respectively, with a mean follow-up of 38 months (range, 24-61). All groups showed significant improvements in forward elevation, ASES scores, and Constant-Murley scores at 24 months (P < .01). The range of external rotation improved significantly in the InT and OnT groups (P < .01), with the greatest improvement in the OnT group (P < .05). Internal rotation declined significantly in the In and InT groups (P < .05) but was preserved in the On and OnT groups. Post-operative ASES and Constant-Murley scores exhibited a similar trend to external rotation outcomes. External rotation in the In group and internal rotation in the In and InT groups did not reach their MCIDs, whereas all groups exceeded the MCIDs for the ASES and Constant-Murley scores.
Conclusion:
LD/TM transfer was associated with restoring external rotation, whereas humeral lateralization seemed related to better post-operative internal rotation. Among the treatment strategies evaluated, rTSA incorporating both LD/TM transfer and humeral lateralization was associated with better outcomes in this challenging patient population.
More Related Videos
 07:10
Modified Long Head of Biceps Tendon Rerouting and Fixation as Partial Capsular Reconstruction for Massive Irreparable Rotator Cuff Tears
Published on: March 6, 2026
 07:22
Arthroscopic Management of Massive Irreparable Rotator Cuff Tears: Whole Rotator Cable Reconstruction Using Proximal Biceps Tendon Autograft
Published on: June 6, 2025
