Related Experiment Video
Updated: Apr 7, 2026
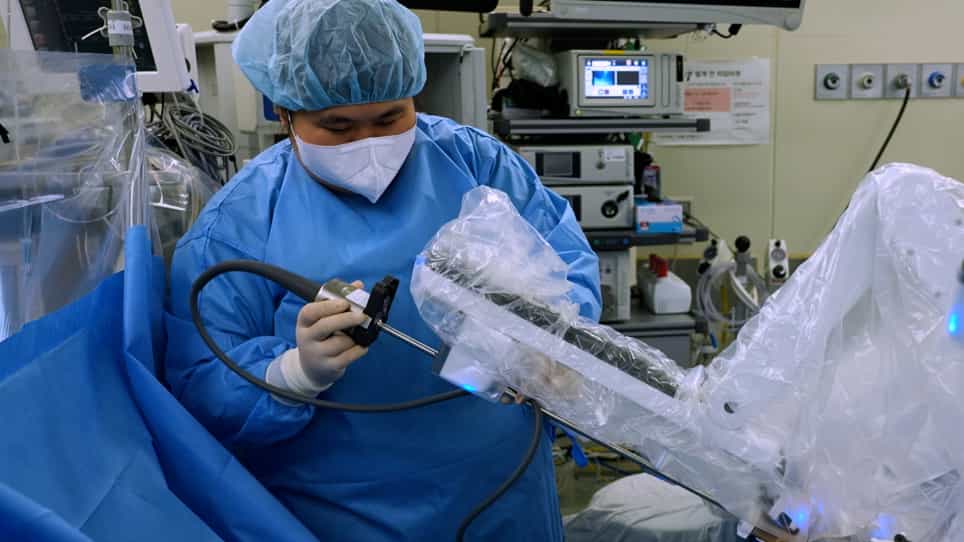

Robot-Assisted Kidney Transplantation
Published on: July 19, 2021
Robot-assisted partial nephrectomy for TFE3-rearranged renal cell carcinoma: a case report and literature review
Biao Jiang1, Shihang Zhang1, Hailin Luo1
1Department of Urology, Ganzhou People's Hospital, Ganzhou, Jiangxi, China.

Background:
TFE3-rearranged renal cell carcinoma (TFE3-RCC) is a rare RCC subtype driven by translocation involving Xp11.2 and TFE3 gene fusion. The management of TFE3-RCC is similar to that of other RCC subtypes and primarily involves surgical resection, targeted therapy, and immunotherapy, with surgical excision serving as the mainstay of treatment for localized disease. This study presents a rare case and demonstrates the feasibility and efficacy of robot-assisted partial nephrectomy (RAPN) in the treatment of localized TFE3-RCC, indicating that with meticulous planning and selection, RAPN could achieve a favorable prognosis in cases of localized TFE3-RCC.
Case Presentation:
We report a case of TFE3 gene fusion-associated renal cell carcinoma (RCC) in a 28-year-old woman who presented with a history of recurrent left flank pain for over two years, which had intensified over the preceding month. Two years earlier, in July 2022, the patient had been diagnosed with a "left renal cyst" at a local institution and received symptomatic treatment. In August 2024, due to the recent aggravation of symptoms, she was admitted for further evaluation. Abdominal contrast-enhanced computed tomography (CT) revealed a Bosniak category III cystic renal lesion, raising suspicion for renal cell carcinoma, measuring approximately 2.1 × 2.4 × 2.1 cm. In September 2024, the patient underwent robot-assisted laparoscopic partial nephrectomy for tumor excision. Histopathological analysis was suggestive of RCC with Xp11.2 translocation/TFE3 gene fusion. The pathological stage was classified as pT1aN0M0, and surgical margins were negative for malignancy. At the one-year follow-up, the patient recovered well without receiving any adjuvant therapy.
Conclusion:
This study elucidates the natural history, diagnosis, and management of TFE3-RCC, underscoring the critical importance of early surgical intervention. TFE3-RCC demonstrates marked aggressiveness, characterized by high recurrence rates and a poor prognosis in adult patients. Surgical resection serves as the mainstay of treatment for localized disease. Given its aggressive nature and substantial risk of recurrence and metastasis, diligent long-term follow-up is essential. For advanced or metastatic disease, targeted therapy and immunotherapy emerge as potential treatment options.


