Related Experiment Video
Updated: Apr 9, 2026
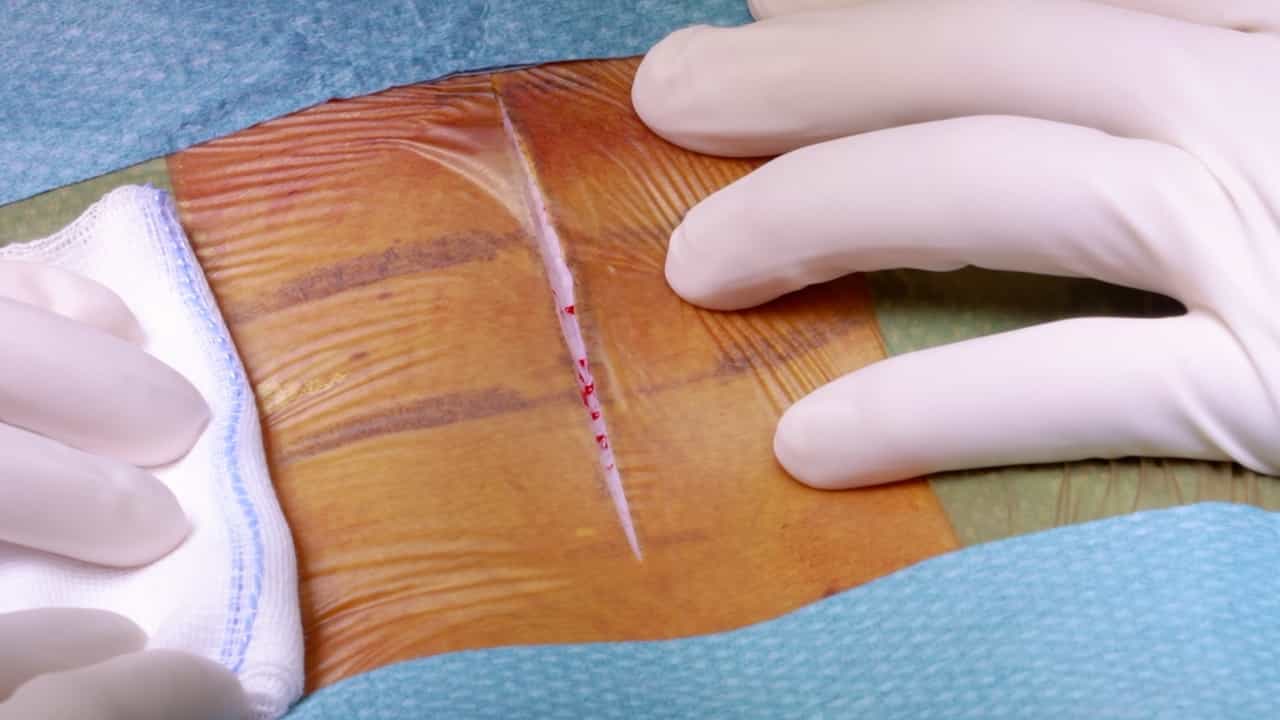

Lateral-PLIF for Lumbar Spinal Arthrodesis: A Detailed Step-By-Step Surgical Technique
Published on: January 23, 2026
Age-Stratified Analysis of Posterior Lumbar Fusion Surgeries: Revealing Unique Surgical Patterns and Outcomes in an
Jonathan Dalton, Alexa Tomlak, Mitchell Ng
1Department of Orthopaedic Surgery, Rothman Orthopaedic Institute, Thomas Jefferson University, Philadelphia, PA, USA.

Study Design:
Retrospective Cohort.
Objective:
Compare surgical characteristics, complications, and patient-reported outcome measures (PROMs) by clinically relevant and easily applicable age-decade groups after posterior lumbar decompression and fusion surgery (PLDF).
Summary Of Background Data:
Due to an aging population and an increased utilization of spine surgery, spine surgeons must increasingly consider age as a variable that affects surgical risk and outcomes.
Methods:
Patients undergoing primary/elective PLDF at one tertiary center (2017-2021) were included. Outcomes included rates of in-hospital and 30-day mortality, 90-day readmission, 1-year revision, and PROMs- Oswestry Disability Index, SF-12 Physical (PCS) and Mental Component Summary (MCS), and Visual Analog Scale (VAS): Back and Leg. Patients were stratified and compared by age decade.
Results:
1100 patients were included (Age: <50-N=90, 50-59-N=212, 60-69-N=385, 70-79-N=334, ≥80-N=79). Increasing age decade was associated with lower BMI. Comorbidities, levels decompressed and fused increased with age decade until 70 then slightly decreased. Patients ≥80 predominantly received PLDF, while those <50 predominantly received TLIF/PLDF. Decade groups were similar regarding rates of in-hospital/30-day mortality, 90-day readmission, 1-year revision, and all PROMs except 6-month and 1-year postoperative MCS. Patients aged 70-79 displayed the best 6-month and 1-year postoperative MCS scores. On multivariable regression, age ≥80 best predicted increased LOS (β=0.89; P<0.001) and non-home discharge (β=3.05; OR=21.17; P<0.001) after accounting for sex, BMI, Charlson Comorbidity Index, operative time, and number of levels fused; age 60-79 showed weaker prediction.
Conclusion:
Following PLDF, older patients had similar postoperative mortality, readmission, revision, and PROM improvement; however increasing age predicted increased LOS and non-home discharge. These results suggest that patients in advanced age decades derive similar benefits to their younger counterparts, while maintaining an appropriate safety profile. Future studies should further elucidate age-related outcome differences to improve risk stratification and patient counseling.