Related Experiment Video
Updated: Apr 9, 2026
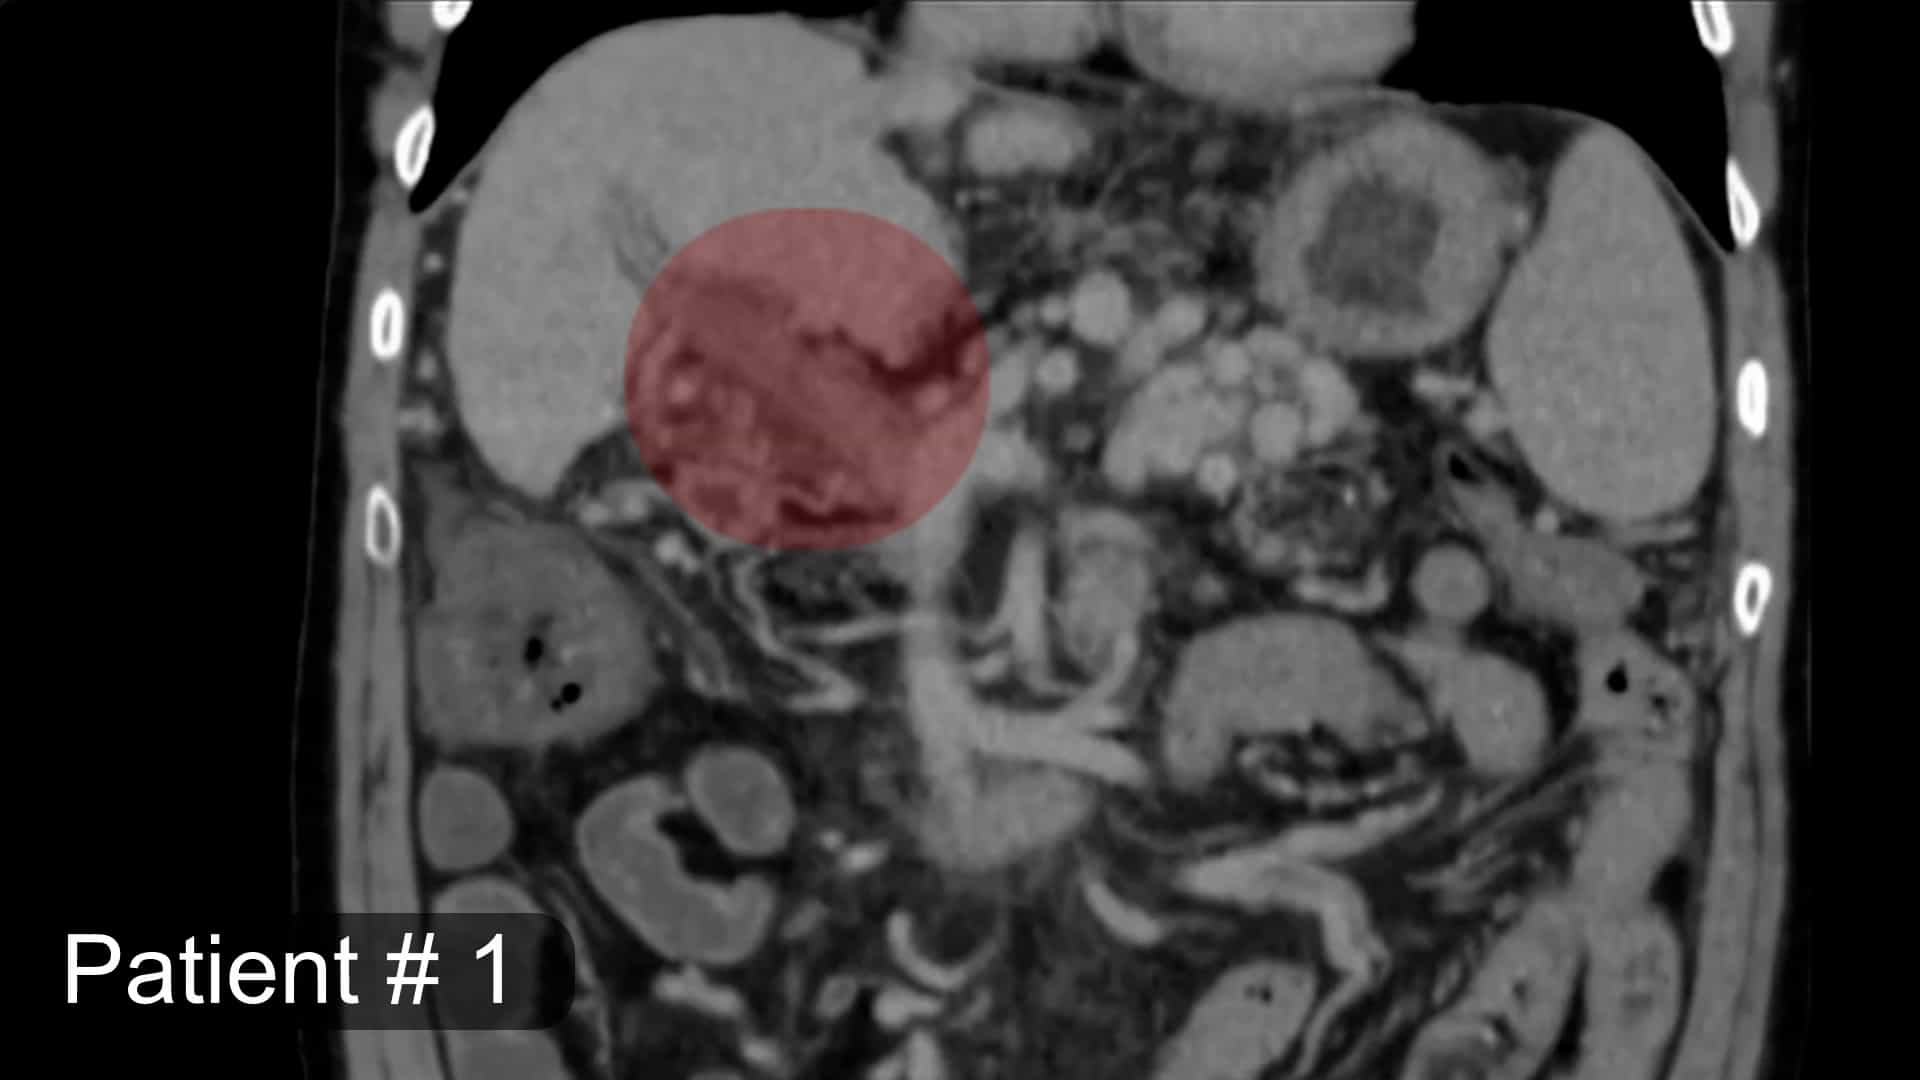
New Thrombectomy Technique for Total Portal Vein Thrombosis in Liver Transplantation
Published on: June 27, 2025
Rebalanced Hemostasis, Bleeding, and Thrombosis in Liver Disease: A Comprehensive Review of Pathophysiology,
1Surgical Research Laboratory and Section of Hepatobiliary Surgery and Liver Transplantation, Department of Surgery, University of Groningen, University Medical Center Groningen, Groningen, The Netherlands.

Patients with liver disease exhibit complex changes in the hemostatic system that are often presumed to drive bleeding and thrombosis. Historically, liver disease was considered a bleeding disorder based on thrombocytopenia, prolonged routine coagulation tests, and reports of fulminant bleeding. Present evidence, however, indicates that antihemostatic changes are compensated for by simultaneous prohemostatic changes, resulting in a rebalanced hemostatic system. Further hemostatic changes may be induced by liver disease progression and extrahepatic factors, such as systemic inflammation, acute kidney injury, and cardiometabolic diseases. Despite extensive hemostatic changes in liver disease, current evidence does not consistently show that they increase bleeding risk, although this has been suggested repeatedly in published literature. Indeed, hemostatic changes appear largely unrelated to most bleeding complications, and specific thrombotic complications also appear unrelated to hemostatic changes. Major bleeding is common but predominantly reflects portal hypertension-related acute variceal bleeding and mechanical injury-related procedural bleeding. A proportion of bleedings, however, may be hemostasis-related, but the vast majority of such events do not require prohemostatic intervention. In contrast, a large proportion of thrombotic complications, including venous thromboembolism, portal vein thrombosis (PVT), and intrahepatic thrombosis, may in part be related to prohemostatic changes, although the role of hypercoagulability in PVT is increasingly questioned. Despite greater attention for thrombotic complications in liver disease, robust studies on optimal anticoagulant strategies are currently lacking. Studies evaluating the pharmacokinetics, pharmacodynamics, and efficacy for prevention of thrombosis and liver decompensation of direct oral anticoagulants and factor XIa inhibitors are therefore urgently needed.
Patients with liver disease exhibit complex changes in the hemostatic system that are often presumed to drive bleeding and thrombosis. Historically, liver disease was considered a bleeding disorder based on thrombocytopenia, prolonged routine coagulation tests, and reports of fulminant bleeding. Present evidence, however, indicates that antihemostatic changes are compensated for by simultaneous prohemostatic changes, resulting in a rebalanced hemostatic system. Further hemostatic changes may be induced by liver disease progression and extrahepatic factors, such as systemic inflammation, acute kidney injury, and cardiometabolic diseases. Despite extensive hemostatic changes in liver disease, current evidence does not consistently show that they increase bleeding risk, although this has been suggested repeatedly in published literature. Indeed, hemostatic changes appear largely unrelated to most bleeding complications, and specific thrombotic complications also appear unrelated to hemostatic changes. Major bleeding is common but predominantly reflects portal hypertension-related acute variceal bleeding and mechanical injury-related procedural bleeding. A proportion of bleedings, however, may be hemostasis-related, but the vast majority of such events do not require prohemostatic intervention. In contrast, a large proportion of thrombotic complications, including venous thromboembolism, portal vein thrombosis (PVT), and intrahepatic thrombosis, may in part be related to prohemostatic changes, although the role of hypercoagulability in PVT is increasingly questioned. Despite greater attention for thrombotic complications in liver disease, robust studies on optimal anticoagulant strategies are currently lacking. Studies evaluating the pharmacokinetics, pharmacodynamics, and efficacy for prevention of thrombosis and liver decompensation of direct oral anticoagulants and factor XIa inhibitors are therefore urgently needed.

Related Concept Videos
 01:24
Disorders of Hemostasis
Thromboembolic Disorders
Two factors primarily cause thromboembolic conditions.
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:30
Venous Thrombosis IV: Nursing Management
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:20
Extrinsic and Intrinsic Pathways of Hemostasis
The Extrinsic Pathway
The extrinsic pathway of coagulation is typically initiated by tissue damage that exposes blood to tissue factor (TF), a protein released by the damaged tissue cells outside the blood vessels—this interaction with TF triggers biochemical reactions involving specific clotting factors. The key player here is Factor VII, which...
 01:05
Introduction to Hemostasis
The three phases of hemostasis involve many clotting factors present in plasma and several substances released by platelets and injured tissue cells. It is a fast, localized,...