Related Experiment Video
Updated: Apr 10, 2026
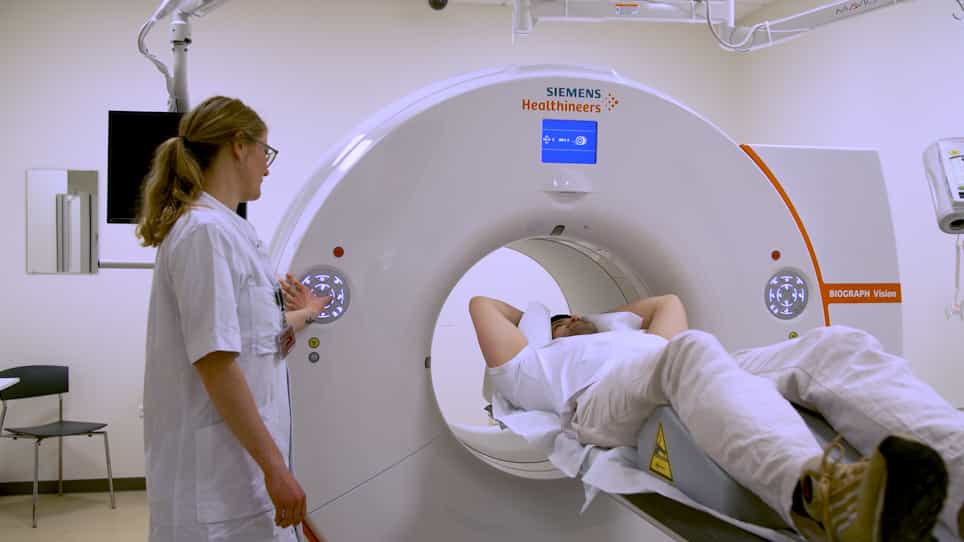

Positron Emission Tomography Using 64-Copper as a Tracer for the Study of Copper-Related Disorders
Published on: April 28, 2023
Diagnostic Accuracy of Exchangeable Copper for Grading the Severity of Wilson Disease
Clément Desjardins1,2, Nouzha Oussedik-Djebrani1,3, Mickael Alexandre Obadia1,2
1National Reference Center for Wilson's Disease and Other Copper-Related Rare Diseases, Rothschild Foundation Hospital, Paris, France.

Abstract:
Wilson disease (WD) diagnosis remains challenging due to variable biomarker performance across clinical presentations. Exchangeable copper (CuEXC) directly quantifies non-ceruloplasmin-bound copper (NCC), the pathogenic copper fraction. We assessed the diagnostic accuracy of CuEXC across WD phenotypes and its utility for evaluating disease severity. In this prospective study (NCT05231876) at the French National Reference Center for WD, we enrolled 158 treatment-naïve patients (48% female; mean age 20 ± 14 years; 44% ≤ 18 years) referred between 2009 and 2025. Clinical presentations included asymptomatic (n = 11), hepatic (n = 87), and neurologic (n = 60). CuEXC was measured at diagnosis and compared against ceruloplasmin, total copper, relative exchangeable copper (REC), and 24-h urinary copper using ROC analysis. Seven patients with hemolytic anemia uniformly associated with acute liver failure had extreme CuEXC elevations (median 11.0 μmol/L) and were excluded from ROC analyses. CuEXC increased stepwise across phenotypes (0.8, 1.6, and 2.9 μmol/L; p < 0.001). CuEXC distinguished advanced from mild-to-moderate liver disease (AUC 0.86; 95% CI, 0.82-0.89; optimal threshold 1.8 μmol/L: sensitivity 83%, specificity 87%) and differentiated neurologic from hepatic presentations (AUC 0.87; 95% CI, 0.80-0.93; optimal threshold 2.07 μmol/L: sensitivity 88%, specificity 81%; pragmatic cutoff 2.0 μmol/L: sensitivity 91%, specificity 80%). Performance was consistent across age groups. CuEXC outperformed other biomarkers in head-to-head comparisons. After excluding hemolysis, CuEXC ≥ 1.8 μmol/L supports screening for advanced liver disease, even without clinical or laboratory liver abnormalities. CuEXC ≥ 2.0 μmol/L warrants expedited neurologic assessment and may help distinguish neuro Wilson from hepatic encephalopathy. CuEXC enhances early risk stratification for timely intervention in WD.
More Related Videos
 11:04
Ion Mobility-Mass Spectrometry Techniques for Determining the Structure and Mechanisms of Metal Ion Recognition and Redox Activity of Metal Binding Oligopeptides
Published on: September 7, 2019
 06:57
Author Spotlight: Advancing Cardiovascular Imaging - Introducing the Spatially Weighted Calcium Score for Early Disease Detection
Published on: September 22, 2023
Related Concept Videos
 01:25
Imaging Studies for Cardiovascular System VI: Calcium -Scoring CT
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:18
Effects of EDTA on End-Point Detection Methods
In the visual method, metal-ion indicators (metallochromic dyes), which have distinct colors in their free and complex forms, are added to the mixture to signal the titration's end point. They form stable complexes with metal ions, but these complexes are weaker than the corresponding metal–EDTA complexes. As a...