Related Experiment Video For Carpal tunnel syndrome
Updated: Apr 10, 2026

Metacarpal Small Incision for Carpal Tunnel Syndrome
Published on: April 5, 2024
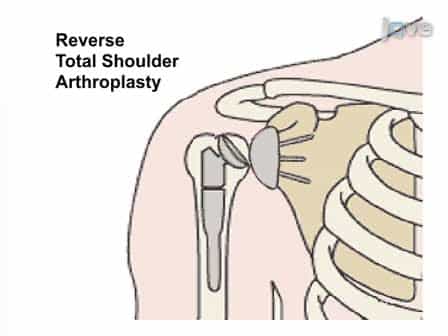
Rate of Ipsilateral Carpal Tunnel Syndrome Increases After Shoulder Arthroplasty
Roberto Gonzalez1, Owen Dean2, Erik R Nakken1
1Department of Orthopaedic Surgery, University of Michigan, Ann Arbor, MI.

Purpose:
Emerging evidence suggests that there may be a link between upper-extremity surgeries and carpal tunnel syndrome (CTS), but whether shoulder arthroplasty is associated with a greater risk of CTS remains unknown. This study investigates the 1-year incidence of ipsilateral CTS following shoulder arthroplasty using the incidence of contralateral CTS as an internal control.
Methods:
This retrospective cohort study used Medicare claims from 2016 to 2022 to evaluate adults ≥18 years old undergoing shoulder arthroplasty. The incidence rate of ipsilateral CTS and contralateral CTS up to 1-year following surgery was estimated for the entire cohort and by subgroups based on the indication for the shoulder arthroplasty. The incidence rate ratio comparing ipsilateral to contralateral incidence of CTS was estimated before and after adjusting for covariates. Among those that developed ipsilateral CTS, the rate of operative CTS and injection to treat CTS was estimated up to 1-year following the incident ipsilateral CTS event.
Results:
There were 4,261 adults identified. For the entire cohort, the ipsilateral incidence of CTS was 46% higher than the contralateral side. A higher CTS incidence on the ipsilateral versus contralateral side was consistent across the subgroups before and after adjusting for covariates. Of 136 beneficiaries who developed ipsilateral CTS, 44.9% received operative carpal tunnel release or injection to treat CTS within 1-year of their CTS diagnosis.
Conclusions:
This analysis found a significantly increased incidence of ipsilateral CTS within 1 year of shoulder arthroplasty, with consistent findings for both degenerative and traumatic indications.
Type Of Study/Level Of Evidence:
Differential diagnosis/symptom prevalence study II.