Related Experiment Video
Updated: Apr 11, 2026
Non-invasive Optical Measurement of Cerebral Metabolism and Hemodynamics in Infants
Published on: March 14, 2013
Clinical application of regional cerebral oxygen saturation with disturbance coefficient in children with brain
Shuai Liu1, Lihong Hu1, Meixian Xu1
1Department of Intensive Care Medicine, Hebei Children's Health and Disease Clinical Medical Research Center, Hebei Children's Hospital, Hebei Medical Key Discipline, Shijiazhuang, Hebei, China.

Insights
Monitoring disturbance coefficient (DC) and cerebral oxygen saturation (rSO₂) in children with brain injury reveals lower levels correlate with injury severity. These non-invasive measures aid in assessing clinical status and predicting outcomes.
Area of Science:
- Pediatric critical care medicine
- Neuroscience
- Biomedical engineering
Background:
- Brain injury in children presents complex diagnostic and prognostic challenges.
- Non-invasive monitoring of cerebral hemodynamics and oxygenation is crucial for timely intervention.
Purpose of the Study:
- To evaluate the clinical utility of monitoring disturbance coefficient (DC) and regional cerebral oxygen saturation (rSO₂) in pediatric brain injury.
- To assess the correlation of DC and rSO₂ with Glasgow Coma Scale (GCS) scores and clinical outcomes.
Main Methods:
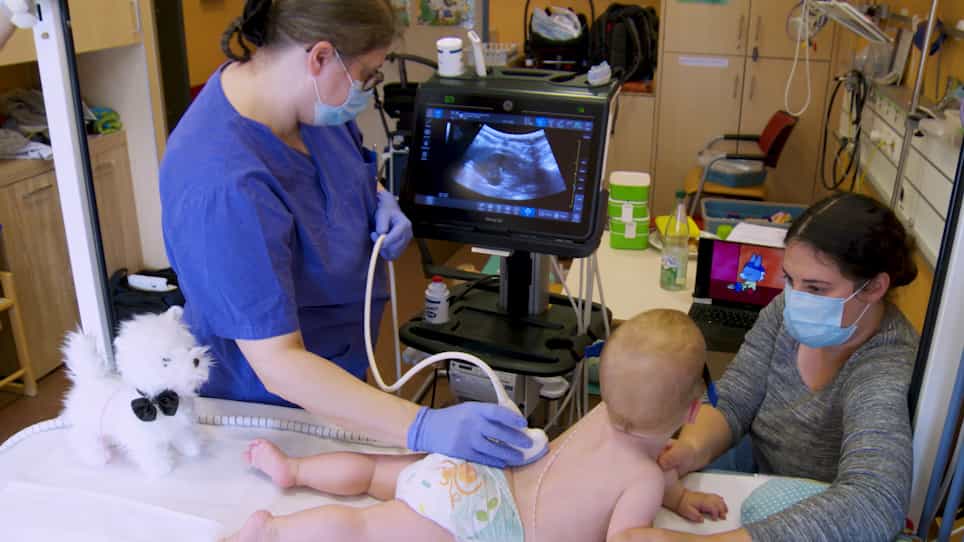
- Ninety-two children with brain dysfunction were monitored for DC and rSO₂ within 24 hours of admission.
- Comparison was made with 150 healthy children serving as controls.
- Correlation analysis with GCS scores and receiver operating characteristic (ROC) curve analysis were performed.
Main Results:
- Children with brain injury exhibited significantly lower DC and rSO₂ levels compared to controls.
- Both DC and rSO₂ showed a positive correlation with GCS scores, indicating lower values with increased injury severity.
- DC demonstrated utility in identifying children at risk for cerebral edema (AUC=0.834), while rSO₂ was associated with poor clinical outcomes (AUC=0.765).
Conclusions:
- Disturbance coefficient (DC) and regional cerebral oxygen saturation (rSO₂) are valuable non-invasive tools for assessing pediatric brain injury.
- These parameters provide complementary information for evaluating clinical status and predicting prognosis in affected children.
- The dynamic and non-invasive nature of DC and rSO₂ monitoring enhances their clinical applicability.
Objective:
To explore the clinical value of monitoring cerebral oxygen saturation and disturbance coefficient in children with brain injury.
Methods:
This study enrolled 92 children with brain dysfunction admitted to the Intensive Care Medicine Department of Hebei Children's Hospital from March 2024 to May 2025 as the research group. They were divided into three subgroups based on age: 1-3, 3-6, and 6-16 years old. During the same period, 150 children who underwent outpatient health examinations were selected as the control group. General information (age, gender, etc.) was collected for both groups. Within 24 h of admission, the research group monitored and recorded DC and rSO2 using non-invasive brain edema and cerebral oxygen saturation monitors, while the control group was monitored DC and rSO2 during outpatient visits. This study aims to compare different DC and rSO₂ groups, examine their correlation with GCS scores, and evaluate the utility of DC and rSO₂ in assessing clinical status and predicting prognosis in children with brain injury.
Results:
There was no statistically significant difference in age and gender between the two groups of patients (P > 0.05). The DC and rSO2 levels in the research group were lower than those in the control group, and the difference was statistically significant (P < 0.05). There was no statistically significant difference (P > 0.05) in DC and rSO2 levels among children of different genders and etiologies in the research group. There is a positive correlation between DC, rSO2, and GCS scores in the research group (rDC = 0.540, P < 0.01; rrSO2 = 0.509, P < 0.01), indicating that the more severe the brain injury, the lower the DC and rSO2 levels. In the 3-6 year old group of children, DC may be useful in identifying children at risk for cerebral edema, with an area under the curve of 0.834 (95% CI 0.695-0.973, P = 0.001). The optimal cutoff value for DC is 75, with a sensitivity of 75% and a specificity of 78.6%. rSO2 was associated with poor clinical outcomes, with an area under the curve of 0.765 (95% CI 0.630-0.899, P = 0.003), an optimal cut-off point of 73.5%, a sensitivity of 70.7%, and a specificity of 83.3%.
Conclusion:
DC and rSO2 may provide complementary information in the evaluation of the condition and prognosis of children with brain injury, as they are non-invasive, dynamic, and have a wider range of clinical applications.