Related Experiment Video
Updated: Apr 12, 2026


Author Spotlight: Scope of LE-ULBD as a Safe, Effective, and Minimally Invasive Approach to Treat Lumbar Spinal Stenosis
Published on: February 9, 2024
Keyhole Foraminotomy Combined With Unilateral Laminotomy for Bilateral Decompression Under Biportal Endoscopic Spinal
Lejian Jiang1, Xiaowei Jing1, Xiaowen Qiu1
1Department of Orthopedics, The Fourth Affiliated Hospital of School of Medicine, and International School of Medicine, International Institutes of Medicine, Zhejiang University, Yiwu, China.

Objectives:
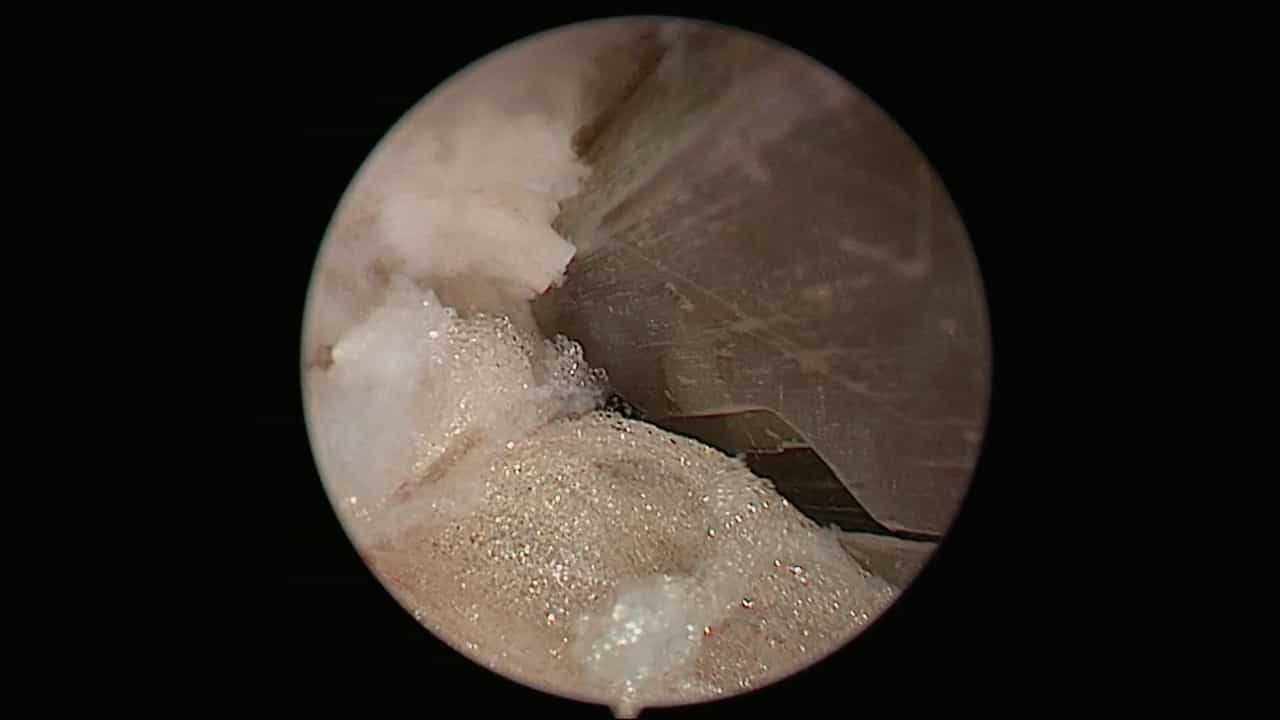
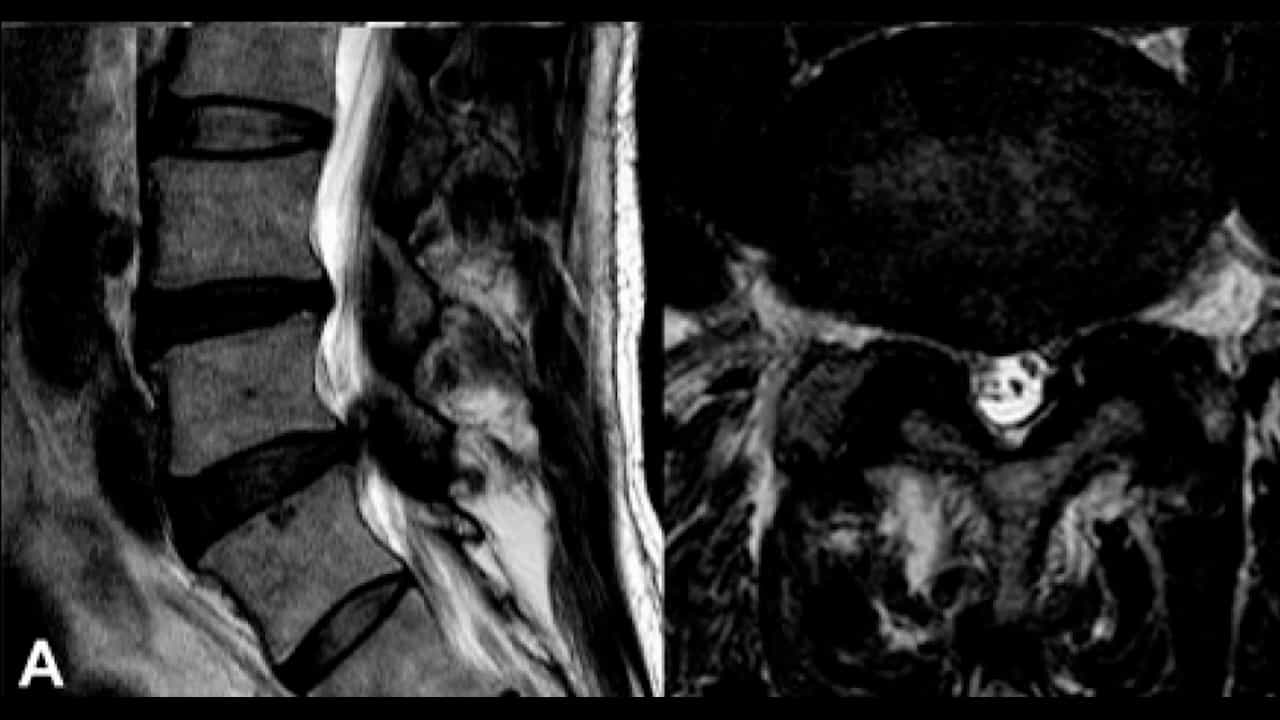
Mixed-type cervical spondylosis (MCS) refers to a degenerative disease in which multiple structures of the cervical spine are affected. Achieving adequate multi-site decompression with minimal muscle dissection is technically demanding in cervical spine surgery. This study aims to evaluate the feasibility of one-stage decompression for MCS with multi-site lesions utilizing biportal endoscopic spinal surgery (BESS). A combined approach involving keyhole foraminotomy and unilateral laminotomy for bilateral decompression (Keyhole-ULBD) was proposed and applied in clinical practice.
Methods:
This study was designed as a technical descriptive study. Patients diagnosed with MCS who underwent Keyhole-ULBD using the BESS technique between October 2022 and June 2024 were enrolled. Demographic characteristics and baseline clinical data were collected. Clinical outcomes were evaluated using the Visual Analog Scale (VAS) and modified Japanese Orthopedic Association (mJOA) scores at 1, 6, and 12 months postoperatively. Radiological parameters were measured to assess the extent of decompression and cervical stability. Paired t-test and Wilcoxon signed-rank test were applied to compare preoperative and postoperative measurements, with statistical significance set at p < 0.05.
Results:
A total of 12 MCS patients were enrolled. Compared with preoperative values, there was a significant increase in foraminal area (from 0.19 ± 0.06 to 0.25 ± 0.06 cm2) and spinal canal area (from 1.36 ± 0.21 to 2.75 ± 0.48 cm2), as well as a marked improvement in VAS-neck scores (from 5.00 ± 1.67 to 1.50 ± 0.55) and mJOA scores (from 12.01 ± 2.19 to 15.83 ± 1.83) at 1 month postoperatively. At the 1-year follow-up, both radiological decompression and improvements in pain and functional outcomes were sustained, demonstrating stable long-term clinical efficacy.
Conclusion:
The Keyhole-ULBD technique offers a safe and effective approach for one-stage decompression in MCS.