Related Experiment Video
Updated: Apr 14, 2026
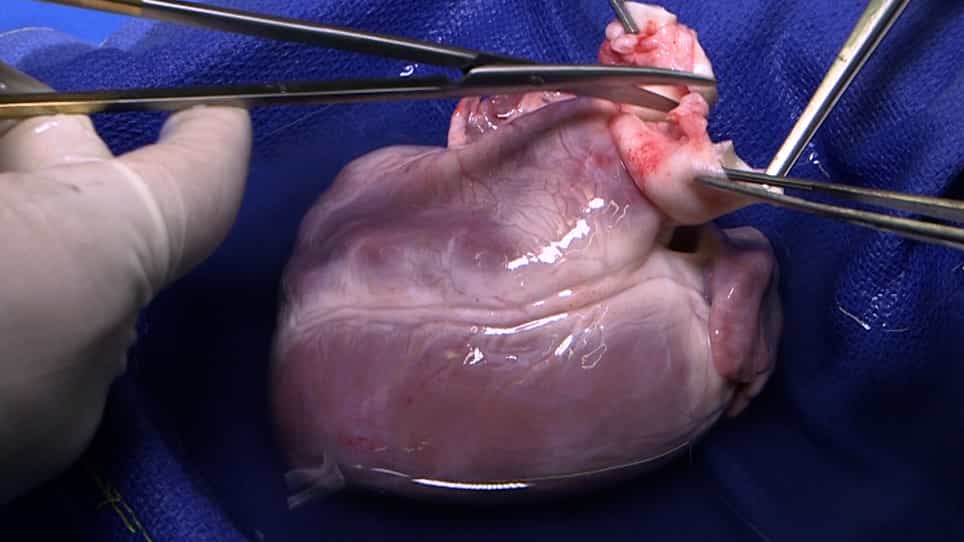

Functional Assessment of the Donor Heart During Ex Situ Perfusion: Insights from Pressure-Volume Loops and Surface Echocardiography
Published on: October 11, 2022
Direct assessment of total cavopulmonary connection power loss with interventional cardiac magnetic resonance in
Hamza Dahshi1, Tarique Hussain2, Surendranath Veeram Reddy2
1Division of Pediatric Cardiology, Department of Pediatrics, UT Southwestern Medical Center, Dallas, Texas, USA; Medical Scientist Training Program, School of Medicine, Case Western Reserve University, Cleveland, Ohio, USA.

Background:
Fontan physiology, reliant on a single ventricle and a passive total cavopulmonary connection (TCPC) flow, is vulnerable to inefficiency. Linking TCPC power loss to cardiac function can provide valuable insights into Fontan hemodynamics. This study quantifies direct TCPC power loss from invasive cardiovascular magnetic resonance (iCMR) data and its relationship to conduit geometry, fenestration flow, and myocardial contractility pre- and post-Fontan fenestration test occlusion (FFTO).
Methods:
Twenty post-Fontan patients underwent iCMR, with 9 also having a FFTO. iCMR catheter-based pressures were combined with phase-contrast CMR flow in the vena cavae and pulmonary arteries. Three-dimensional (3D) whole-heart imaging provided conduit cross-sectional areas (CSA). A patient-specific biomechanical model estimated myocardial contractility from iCMR data. In-vivo TCPC blood flow indexed power loss (iPL) was calculated at baseline in 20 patients, and post-FFTO in 9.
Results:
Mean (±SD) at baseline was 0.24 ± 0.15 and decreased significantly from 0.27 ± 0.14 to 0.13 ± 0.10 in 9 patients post-FFTO (p = 0.010). Fenestration flow explained 46.5% of variation in iPL at baseline. Higher iPL was associated with higher myocardial contractility (R2 = 0.216, p = 0.004) pre-FFTO, and with lower myocardial contractility (R2 = 0.43, p = 0.054) post-FFTO. Higher iPL correlated with smaller conduit CSA (R2 = 0.26, p = 0.030) at baseline.
Conclusion:
Increased iPL was related to increased fenestration flow, increased contractility, and decreased conduit narrowing at baseline. Post-FFTO, increased iPL was associated with decreased contractility, suggesting that acute fenestration closure might cause preload suppression in the ventricle. This study offers a clinically relevant framework to obtain mechanistic insights into Fontan physiology and guide personalized strategies for fenestration management.
More Related Videos
 06:29
Wireless Telemetry Device Implantation in a Fontan Ovine Model for Continuous and Long-Term Hemodynamic Monitoring
Published on: May 2, 2025
 08:01
Semi-Minimal Invasive Method to Induce Myocardial Infarction in Rats and the Assessment of Cardiac Function by an Isolated Working Heart System
Published on: June 11, 2020