Related Experiment Video
Updated: Apr 14, 2026

Author Spotlight: Advanced Ex Vivo Model for Investigating Cancer-Adipose Microenvironment Interaction
Published on: January 26, 2024
Ileocecal and Small Bowel Involvement Are Independently Associated with Inferior Survival Despite Complete
Ingo B Runnebaum1,2,3, Angela Kather4,5, Clara Evangelia Goerdt4
1Department of Gynecology and Reproductive Medicine, Jena University Hospital, Friedrich- Schiller-University Jena, Jena, Germany. ingo.runnebaum@med.uni-jena.de.

Background:
Complete macroscopic tumor resection is the strongest prognostic factor in advanced epithelial tubo-ovarian and primary peritoneal cancer, yet benefit from maximum-effort cytoreductive surgery may vary with tumor distribution and site-specific resections. We aimed to identify predictors of long-term survival, considering postoperative morbidity, to inform preoperative stratification.
Patients And Methods:
This study had a retrospective single-center cohort of 302 all-comers patients with International Federation of Gynecology and Obstetrics/American Joint Committee on Cancer (FIGO/AJCC) IIIC-IV epithelial tubo-ovarian or primary peritoneal cancer undergoing maximum-effort cytoreductive surgery in a European Society of Gynecological Oncology (ESGO)-certified high-volume tertiary referral center (2006-2021). Major complications (Clavien-Dindo ≥ IIIb) were analyzed using multivariable logistic regression; progression-free and overall survival (PFS/OS) using Cox regression. Subgroup analyses explored site-specific bowel resections.
Results:
Complete resection was achieved in 259 (85.8%) patients, requiring high surgical complexity in 221 (73.2%, Surgical Complexity Score ≥ 8). Intestinal segment resections were performed in 71.5% of patients, including ileocecal resection in 24.5%. Large bowel resection (OR 2.708, p = 0.002) significantly increased major postoperative morbidity. Anastomotic leakage occurred in 6.0%, independent of transitory stoma formation (p = 0.759). Small bowel resection independently predicted impaired long-term survival (3-year OS 31.8% versus 57.0%, p < 0.001). Ileocecal resections were associated with poorest outcome (3-year OS 24.2%, p < 0.001). Complete macroscopic resection remained prognostically beneficial. Neoadjuvant chemotherapy (13.9%) and high surgical complexity did not negatively affect long-term survival.
Conclusions:
Ileocecal and small bowel involvement are independently associated with inferior survival despite complete cytoreduction in FIGO IIIC-IV disease. These findings support preoperative triage and counseling by the multidisciplinary tumor board, with selective consideration of primary systemic therapy with planned interval cytoreduction for extensive small bowel/ileocecal disease, particularly in frail or complex patients.

Related Concept Videos
 01:27
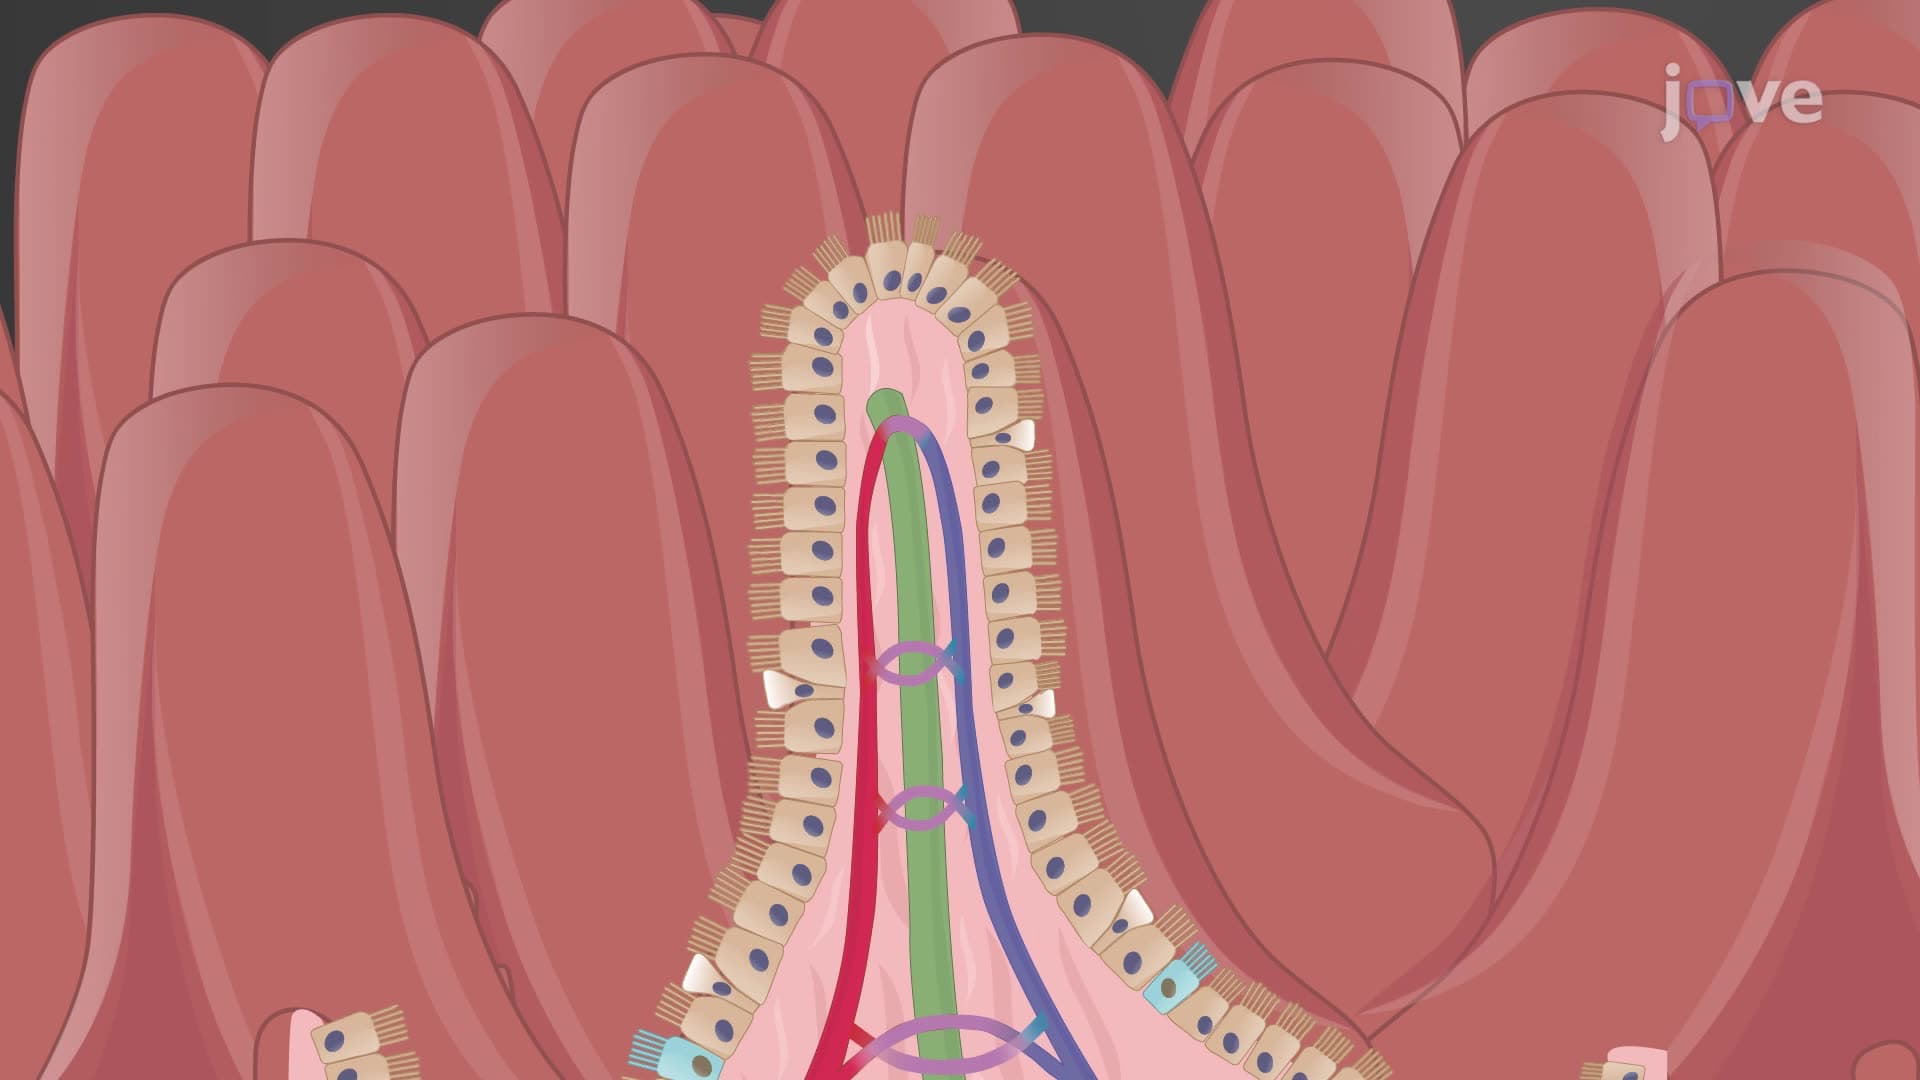
Histology of the Small Intestine
The intestinal lining features transverse folds called circular folds, each housing fingerlike projections known as intestinal villi. These villi are covered by a layer of simple columnar epithelium, also referred to as...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD: