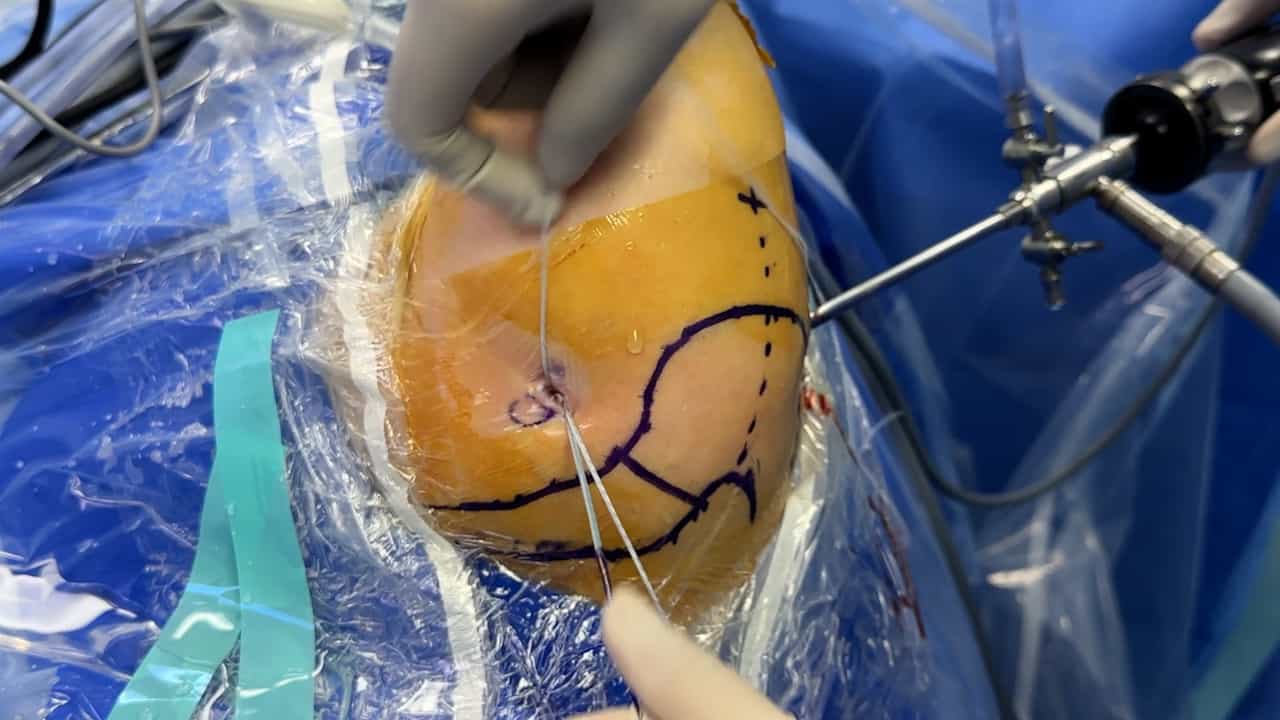
Related Experiment Video
Updated: Apr 14, 2026


The Transition to an Anterior-Based Muscle Sparing Approach Improves Early Postoperative Function but is Associated with a Learning Curve
Published on: September 7, 2022
Estimation of safe zones for suture anchor placement in arthroscopic hip labral repair
Xinkun Han1,2, Xinyu Tang1,2, Liping Li3
1Department of Sports Medicine, The Affiliated Hospital of Qingdao University, Qingdao University, Qingdao, Shandong, China.

Background:
During arthroscopic labral repair, anchors are inserted into the acetabular rim between 10- and 4-o'clock via multiple portals. This study evaluates in situ bone quality along each trajectory and precisely defines the spatial relationships between the drill path and adjacent neurovascular, capsular, and chondral structures, thereby establishing an evidence-based safety envelope for acetabular anchor placement.
Methods:
In stage one, 11 patients (22 hips) underwent skin marking of surface portals followed by 0.625 mm CT acquisition; Mimics reconstructed the bony model, and Autodesk Maya simulated anchor trajectories to define a preliminary safety zone. In stage two, six formalin-fixed specimens (12 hips) were equipped with 3-D-printed, patient-specific guides after portal marking, dissected, and instrumented at 10-4 o'clock positions. Anchors inserted via anterior, anterolateral, and DALA portals validated the virtual safety map, after which the refined data were applied prospectively in clinical application.
Results:
Virtual anchoring revealed marked, position-dependent differences: the DALA portal at 12-o'clock achieved only 50.0% success, significantly below the anterolateral (86.4%) and anterior (90.9%) portals (P = 0.004); the anterior portal at 1-o'clock reached 95.5%, exceeding both anterolateral (46.7%) and DALA (27.3%) (P < 0.001); DALA at 3-o'clock yielded 77.3%, surpassing anterolateral (27.3%) and anterior (13.6%) (P < 0.001); and anterolateral at 4-o'clock fell to 18.2%, well below DALA (86.4%) and anterior (72.7%) (P < 0.001). Success rates at 10-, 11-, and 2-o'clock did not differ among portals. Cadaveric validation closely mirrored these trends: no significant inter-portal differences were observed at 10-, 11-, 12-, 1-, 2-, or 3-o'clock, whereas 4-o'clock showed a significant disparity (χ² = 8.222, P = 0.016), with the anterior portal (75.0%) outperforming the anterolateral (16.7%); DALA (50.0%) did not differ significantly from either. Adherence to these validated trajectories enhances procedural safety and anchor reliability.
Conclusion:
For arthroscopic labral repair, anchor placement should follow these portal-specific safe corridors: anterior portal-10, 11, 12, 1, 2, and 4 o'clock; anterolateral portal-10, 11, 12, and 2 o'clock; DALA portal-10, 11, 2, 3, and 4 o'clock.