Related Experiment Video
Updated: Apr 14, 2026
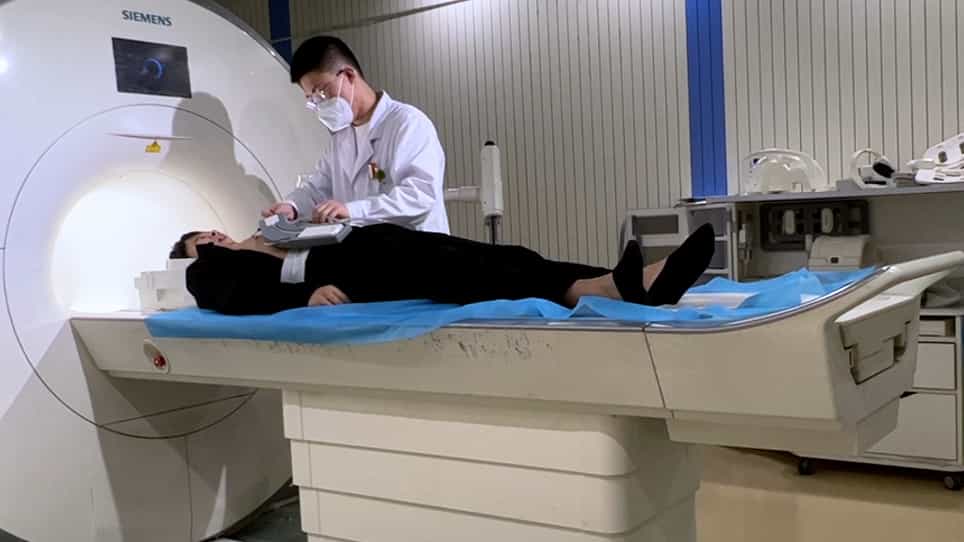
Estimating Bilateral Atrial Function by Cardiovascular Magnetic Resonance Feature Tracking in Patients with Paroxysmal Atrial Fibrillation
Published on: July 20, 2022
Comparative analysis of right atrial function in arrhythmogenic right ventricular cardiomyopathy and dilated
Wenqi Liu1,2, Yiyuan Gao1,3, Wanzhen Li1,4
1Department of Radiology, The First Affiliated Hospital of Zhejiang Chinese Medical University (Zhejiang Provincial Hospital of Chinese Medicine), Hangzhou, China.

Background:
Although the importance of right atrial (RA) function is being increasingly acknowledged, comparative studies investigating RA dysfunction in patients with arrhythmogenic right ventricular cardiomyopathy (ARVC) and dilated cardiomyopathy (DCM) remain limited. This study aimed to compare RA function between ARVC and DCM using cardiac magnetic resonance-feature tracking (MR-FT).
Methods:
This retrospective study (June 2018 to December 2022) included 38 patients with ARVC, 98 patients with DCM, and 72 sex- and age-matched healthy controls (HC). RA deformation parameters, including RA reservoir strain (εs), conduit strain (εe), and booster strain (εa), as well as RA peak positive strain rate (SRs), peak early negative strain rate (SRe), and peak late negative strain rate (SRa), were assessed using the MR-FT technique. Group differences in RA deformation parameters were analyzed using one-way analysis of variance (ANOVA) and Kruskal-Wallis test. Pearson and Spearman correlation methods were performed to explore the correlation between RA deformation parameters and RA emptying fractions (RAEFs).
Results:
Patients with ARVC exhibited greater right ventricular (RV) end-diastolic volumes than those with DCM (P<0.001). Compared with HC, both ARVC and DCM patient cohorts had lower RA εs {49.5%±14.4% vs. 26.6% [interquartile range (IQR, 15.8-29.8%)] vs. 19.0% (IQR, 14.0-27.7%)}, εe [32.7%±12.9% vs. 17.7% (IQR, 11.9-22.1%) vs. 8.9% (IQR, 5.6-13.3%)], SRs [2.1 (IQR, 1.7-2.8) vs. 1.7±0.8 vs. 1.1 (IQR, 0.8-1.6) s-1], and SRe [-2.6±1.2 vs. -1.3 (IQR, -1.9 to -0.9) vs. -0.7 (IQR, -1.3 to -0.5) s-1] (all P<0.05), with DCM demonstrating lower values than those with ARVC (all P<0.05). RA deformation parameters were notably correlated to RAEFs among the three groups (HC, ARVC, and DCM, RA εs and RAEF total: r=0.73, 0.81, and 0.74; RA εe and RAEF passive: r=0.66, 0.76, and 0.77; RA εa and RAEF booster: r=0.55, 0.73, and 0.61) (all P<0.001). MR-FT-derived RA strain and SR measurements showed excellent reproducibility, with interclass correlation coefficients ranging from 0.913 to 0.987.
Conclusions:
Despite the more pronounced RV dilation in patients with ARVC, those with DCM exhibited significantly greater impairment in RA function with lower MR-FT-derived RA strain and SR values. ARVC and DCM showed different pathological patterns in RA dysfunction.
More Related Videos
Related Concept Videos
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy