Related Experiment Video
Updated: Apr 14, 2026


Fecal Microbiota Transplantation via Colonoscopy for Recurrent C. difficile Infection
Published on: December 8, 2014
Training and Comfort in the Management of Fecal Incontinence
Lei A Qin1, Melissa A Ardizzone2, Uduak U Andy1
1Division of Urogynecology and Reconstructive Pelvic Surgery at Penn Medicine, Philadelphia, PA.

Importance:
Fecal incontinence (FI) is common, underdiagnosed, and often undertreated. Understanding gaps in training, comfort, and confidence in managing FI among urogynecology fellows and attending physicians (attendings) may improve patient access to high-quality care.
Objective:
The objective of this study was to assess clinical exposure, didactic training, and self-reported comfort with FI management among urogynecology fellows and fellowship-trained attendings in the United States.
Study Design:
A cross-sectional, anonymous electronic survey was distributed to physician members of the American Urogynecologic Society (AUGS) in 2025. The survey evaluated demographic characteristics, exposure to FI during fellowship and current practice, availability of diagnostic and procedural tools, didactic education, and comfort with medical and procedural management. Responses were summarized using descriptive statistics, and 1-way analyses of variance (ANOVA) were used to assess associations between level of training and overall comfort.
Results:
A total of 202 respondents completed the survey (35 fellows, 167 attendings; response rate 14.3%). More than half of fellows (54.3%) and two thirds of attendings (66.5%) completed a colorectal surgery rotation, while gastroenterology rotations were less common. Most respondents evaluated patients with FI weekly (60.0% of fellows; 51.5% of attendings). Fewer than half felt comfortable performing or interpreting anorectal manometry or endoanal ultrasound. Only 8.6% of fellows and 31.1% of attendings reported feeling very comfortable with FI management. Overall comfort increased with advancing training stage and years in practice ( P <0.001) but was not associated with colorectal or gastroenterology rotations. Most respondents (80.0% of fellows; 63.5% of attendings) believed that improving clinician comfort would enhance patient outcomes and access to care.
Conclusions:
Clinical and didactic exposure to FI varies widely across urogynecology training and practice. Despite frequent encounters, limited procedural experience contributes to persistent discomfort with FI management. Standardizing fellowship education and expanding interdisciplinary, longitudinal training may improve clinician confidence and patient care.


Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:30
Irritable Bowel Syndrome III: Medical and Nursing Management
 01:17
Urinary Tract Infection IV: Nursing Management
 01:21
Drugs for Treatment of Constipation-Predominant IBS
 01:26
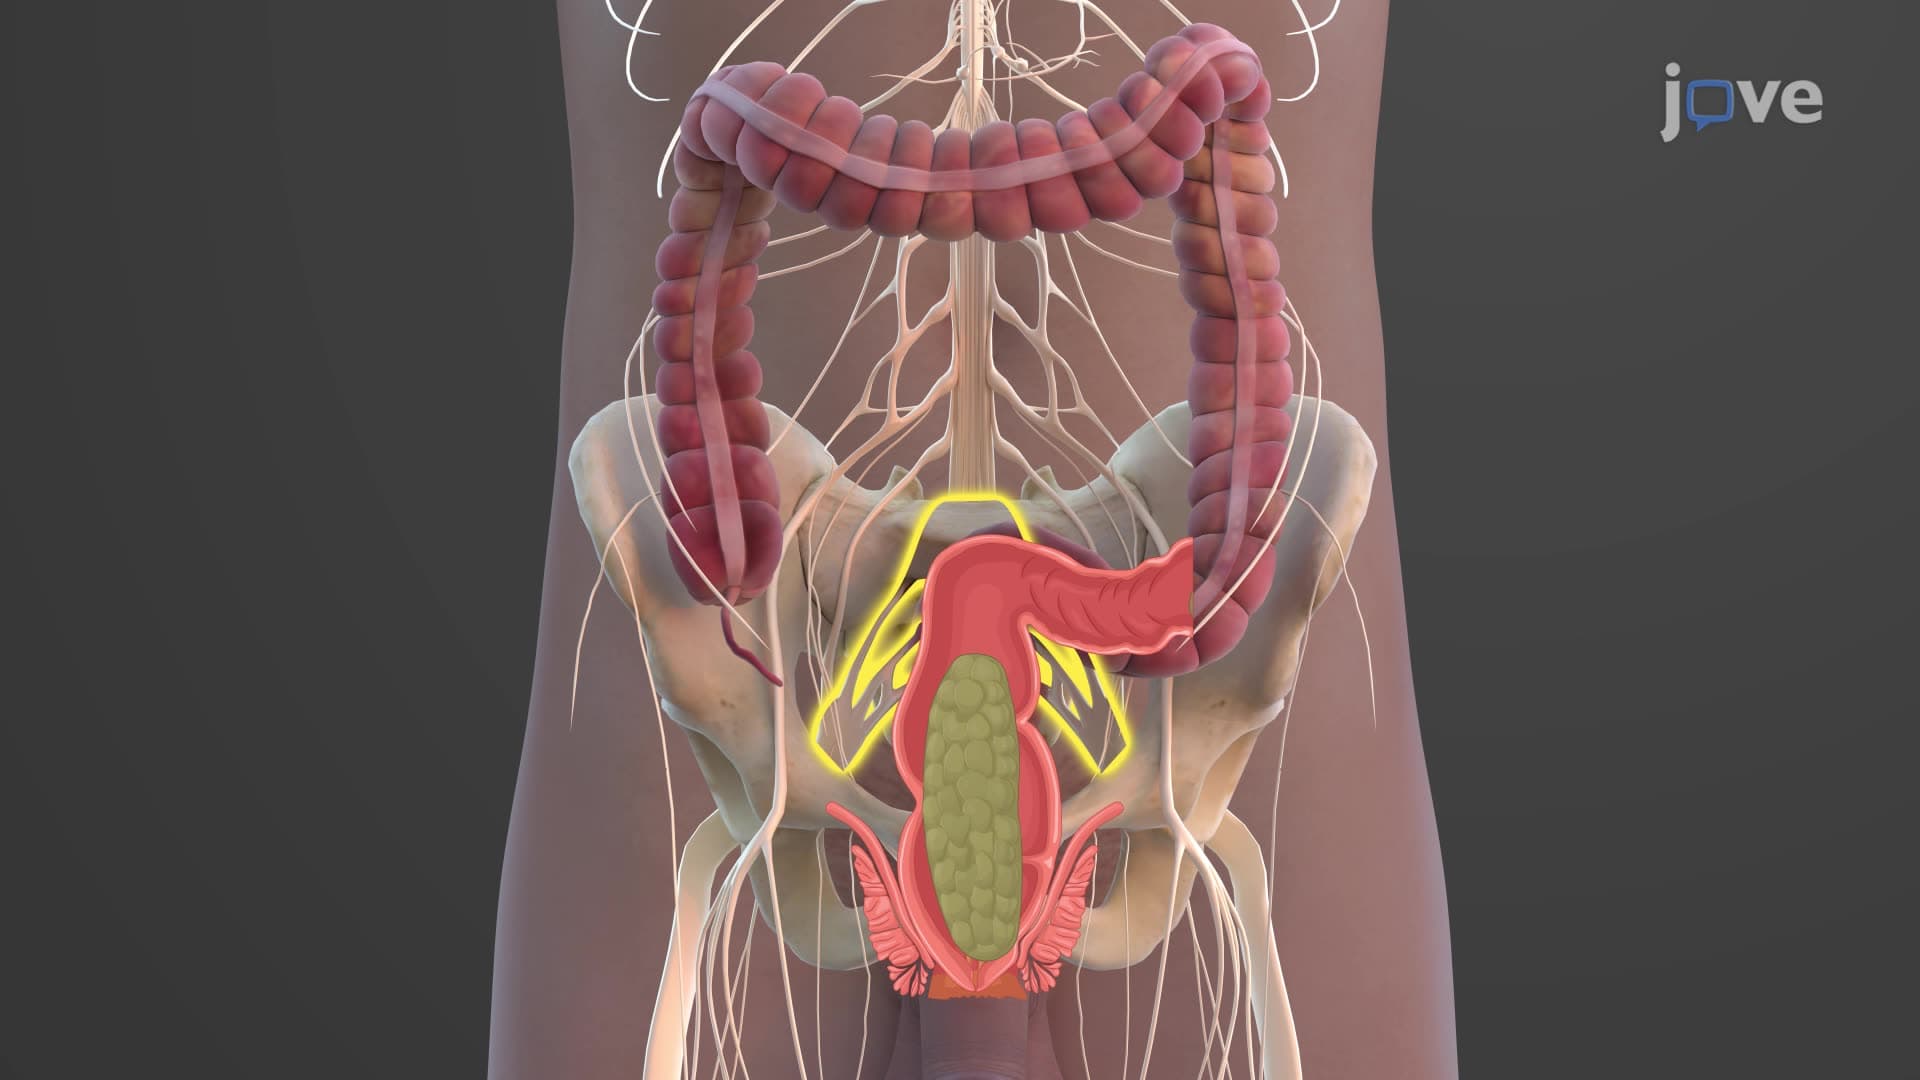
Feces Formation and Defecation
The mass peristalsis then pushes the feces into the rectum, which stretches the rectal walls to activate...
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...