Related Experiment Video
Updated: Apr 16, 2026

Segmentation and Linear Measurement for Body Composition Analysis using Slice-O-Matic and Horos
Published on: March 21, 2021
Preoperative non-contrast CT-derived adiposity quantity and attenuation predict recurrence-free survival after
Zhongwei Ma1, Le Kang1, Yanghuang Zheng1
1Department of Urology, Lanzhou University Second Hospital, Lanzhou, Gansu, China.

Purpose:
To assess whether preoperative non-contrast CT-derived adiposity quantity and attenuation are independently associated with recurrence-free survival (RFS) after surgery for localized clear cell renal cell carcinoma (ccRCC).
Methods:
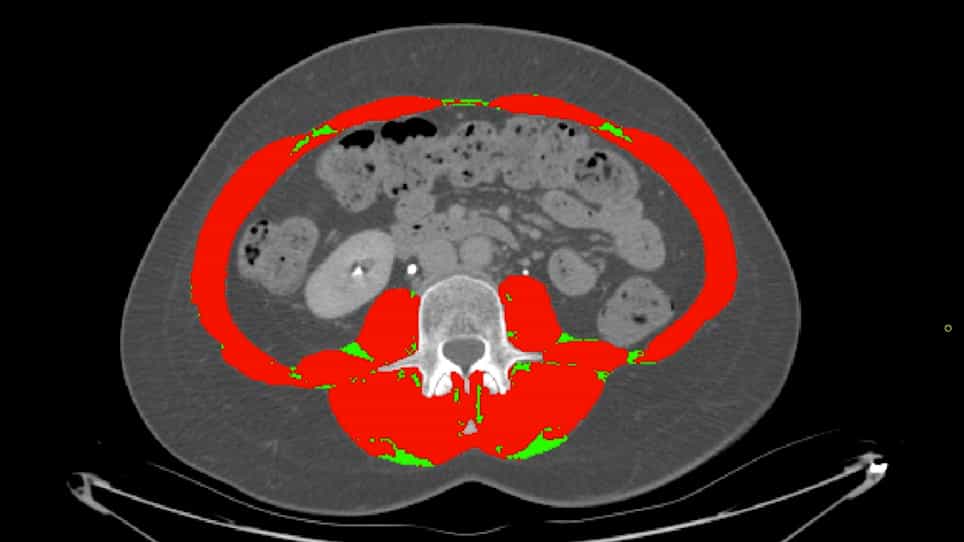
We performed a single-center retrospective cohort study of adults with pathologically confirmed ccRCC who underwent upfront partial or radical nephrectomy and had preoperative non-contrast abdominal CT within 30 days. A single mid-L3 axial slice was segmented for subcutaneous (SAT) and visceral adipose tissue (VAT) using predefined thresholds (SAT-190 to -30 HU; VAT-150 to-50 HU). Adiposity indices were normalized by height squared (SATI, VATI), and mean SAT/VAT attenuation (HU) was recorded. RFS was defined as time from surgery to first documented local/regional recurrence or distant metastasis. Multi-variable Cox models were adjusted for age, sex, chronic disease history, tumor diameter, surgery type, and WHO/ISUP grade; continuous predictors were standardized (per 1-SD). Incremental prognostic performance beyond the clinicopathologic base model was assessed using Harrell's C-index.
Results:
Among 598 patients, 151 (25.3%) developed recurrence/metastasis. Higher SATI and VATI were associated with longer RFS in separate adjusted models (per 1-SD: SATI HR 0.55, 95% CI 0.44-0.68; VATI HR 0.63, 0.53-0.76). Higher (less negative) attenuation was associated with shorter RFS in separate adjusted models (SAT HU HR 1.29, 1.12-1.48; VAT HU HR 1.40, 1.21-1.60). In joint models, the SATI association remained robust, whereas VATI and VAT attenuation were attenuated. The apparent C-index of the clinicopathologic base model improved from 0.667 to 0.707 after adding SATI and to 0.713 after adding SATI + VATI.
Conclusion:
Routine preoperative non-contrast CT measures of adiposity quantity, and to a lesser extent attenuation, provide prognostic information for postoperative RFS in localized ccRCC. In this localized surgery-treated cohort, SATI was the most stable independent marker and modestly improved discrimination beyond clinicopathologic factors.