Related Experiment Video
Updated: Apr 16, 2026


ADSC-sheet Transplantation to Prevent Stricture after Extended Esophageal Endoscopic Submucosal Dissection
Published on: February 10, 2017
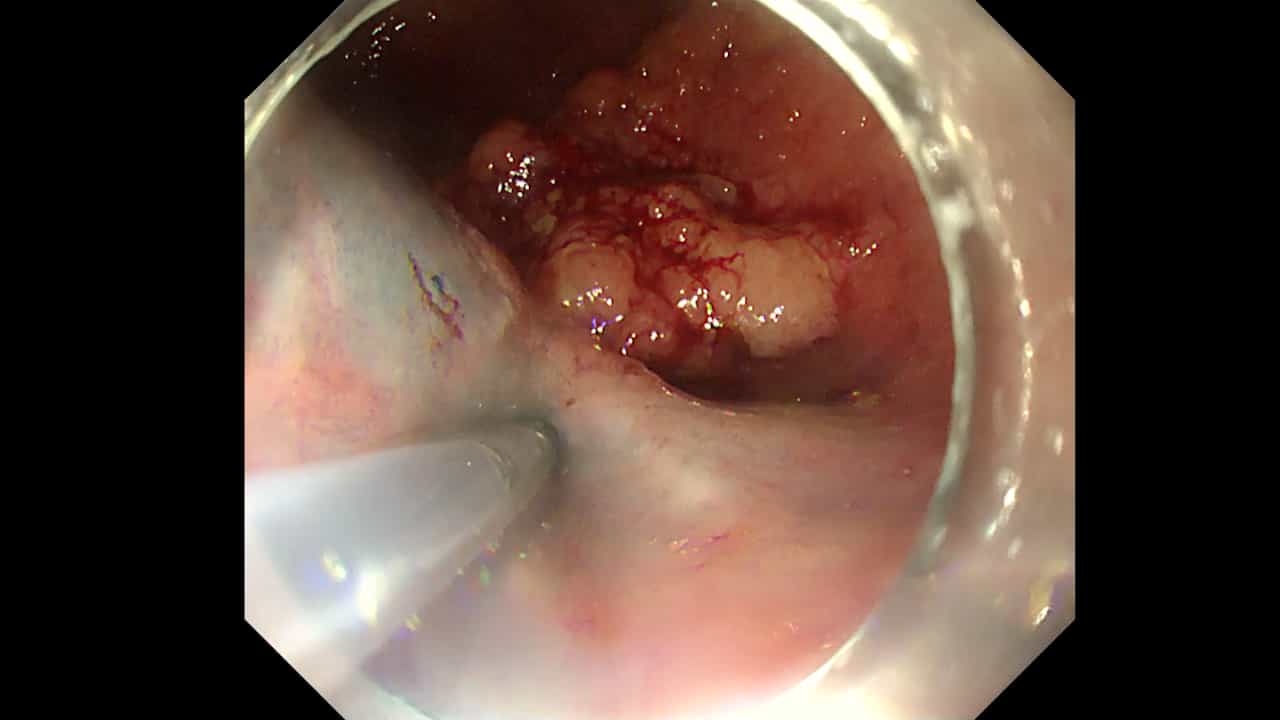
Enlarging Inflammatory Granulation Tissue After Endoscopic Submucosal Dissection at the Esophageal Inlet During
Chihiro Tsurita1,2, Naoya Tada1, Akira Dobashi1
1Department of Endoscopy The Jikei University School of Medicine Tokyo Japan.

Abstract:
Surveillance endoscopy in a 47-year-old woman with previous hypopharyngeal chemoradiotherapy and esophageal endoscopic submucosal dissection (ESD) revealed a 12-mm superficial squamous cell carcinoma at the cervical esophagus near the inlet. ESD achieved en bloc resection with a half-circumferential mucosal defect, and histopathology showed pT1a lamina propria mucosae with negative margins. For stricture prophylaxis, triamcinolone was injected into the post-ESD defect, oral prednisolone was tapered over several months, and prophylactic endoscopic balloon dilation was performed three times at 3-4-week intervals. Three months after ESD, a 10-mm white-coated lesion appeared at the inlet and progressively enlarged. Under intravenous sedation, detailed endoscopic assessments and biopsies were limited by the complex location, and the biopsy suggested neoplastic cells with marked degeneration. Due to progressive odynophagia and poor oral intake, endoscopic re-evaluation under general anesthesia was performed. Using Sato's curved laryngoscope, the lesion was clearly visualized as a semipedunculated mass arising from the post-ESD site and was completely resected for diagnosis and symptom relief. Histopathology revealed inflammatory granulation tissue without malignancy. Symptoms resolved promptly with no recurrence during 6 months of follow-up. This case highlights the development of exuberant granulation tissue at the post-ESD site in the cervical esophagus during intensive stricture prophylaxis. Although this rare finding likely reflects multiple overlapping factors, endoscopic evaluation and treatment were successfully performed while avoiding overtreatment.
More Related Videos
 04:09
The Pocket-Creation Procedure of Endoscopic Submucosal Dissection for Large Rectal Laterally Spreading Tumors
Published on: February 13, 2026
 04:05
Endoscopic Vacuum Therapy for the Treatment of Anastomotic Leakage after Total Gastrectomy with Esophagojejunostomy
Published on: August 22, 2025
Related Concept Videos
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to:
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...