Related Experiment Video
Updated: Apr 17, 2026
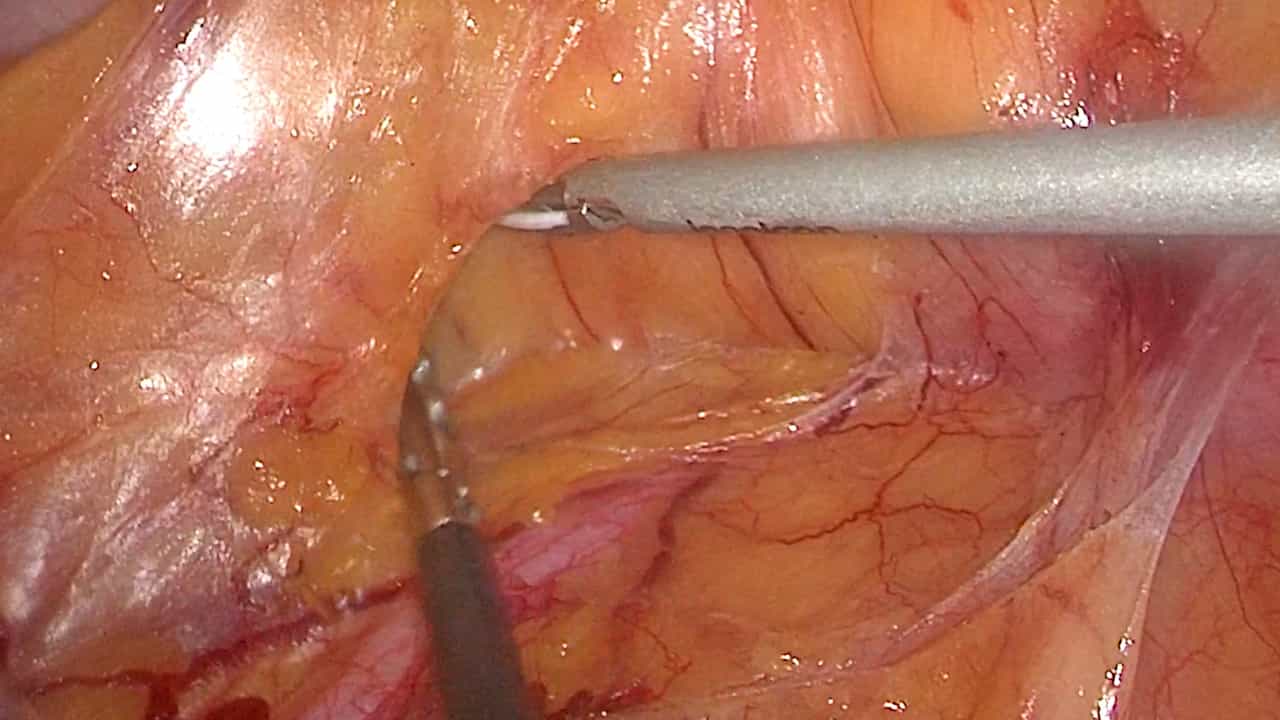

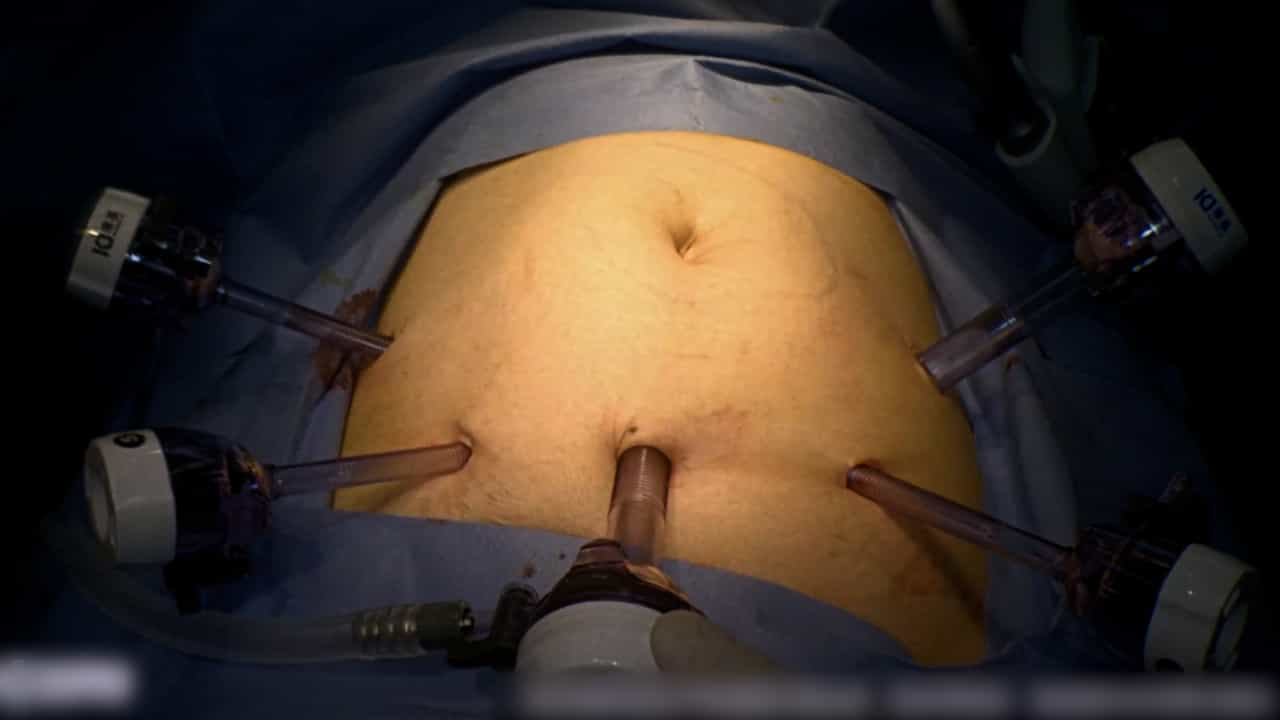
Caudal-to-cranial Approach in Laparoscopic Right Hemicolectomy with Complete Mesocolon Excision and D3 Lymph Node Dissection
Published on: January 9, 2026
Is Complete Mesocolic Excision with Central Vascular Ligation Necessary for Suspected Early-stage Right-sided Colon
Mi Jeong Choi1, Duck-Woo Kim1,2, Yu Kyung Jun3
1Department of Surgery, Seoul National University Bundang Hospital, Seongnam, Korea.

Purpose:
To assess lymph node status in patients undergoing additional surgery after endoscopic resection to evaluate the need for complete mesocolic excision with central vascular ligation for clinically suspected early-stage right-sided colon cancer.
Materials And Methods:
This retrospective study, conducted at a single institution using a prospectively collected database, comprised patients who underwent additional surgery following endoscopic intervention between May 2003 and March 2022. The primary outcomes were the rate and location of lymph node metastases, including peritumoral, pericolic, and superior mesenteric lymph nodes. The secondary outcome was recurrence-free survival.
Results:
Among 119 patients, pathological examination identified 5 (4.2%) with Tis requiring surgery owing to uncheckable margins or tumor depth, 106 (89.1%) with stage T1 tumors, and 8 (6.7%) with stage T2 tumors. The nodal stage was N0 in 107 patients (89.9%) and N1 in 12 (10.1%) patients. The mean number of harvested lymph nodes was 39.7, including 7.6 ± 6.9 peritumoral, 31.5 ± 14.4 pericolic, and 4.0 ± 3.8 superior mesenteric nodes. All metastatic lymph nodes were in the peritumoral and pericolic regions. At a mean follow-up of 48.2 months, recurrence occurred in one (0.8%) patient, who developed liver metastases 24 months postoperatively.
Conclusion:
For patients with clinically suspected early-stage right-sided colon cancer who initially underwent endoscopic resection, the risk of superior mesenteric node metastases is very low. D2 lymph node dissection alone may be sufficient rather than routine application of complete mesocolic excision with central vascular ligation, which might be reconsidered in these patients.