Related Experiment Video
Updated: Jul 3, 2026
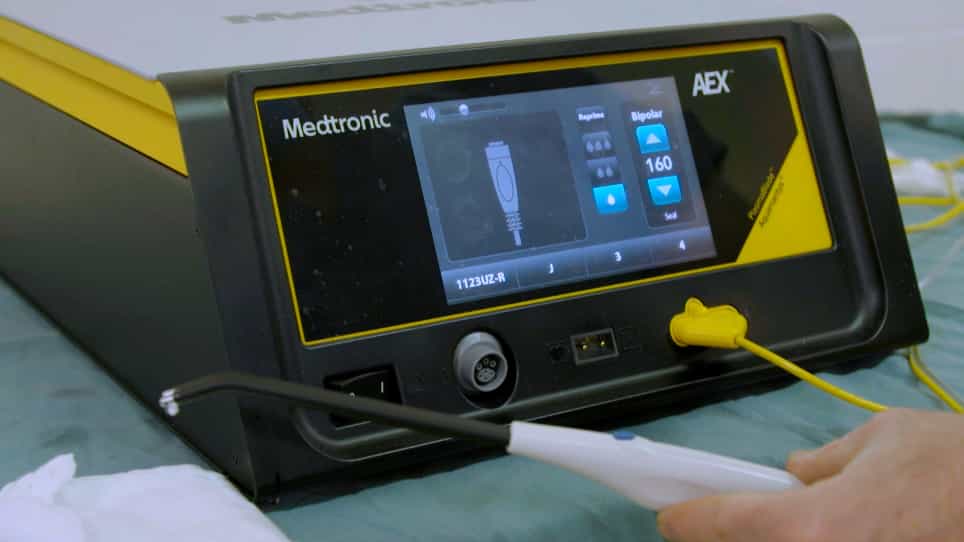

A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
Sonorheometry to detect traumatic induced coagulopathy during initial management of trauma patients: an
Gary Duclos1, Pierre Antoine Seube Remy2, Mathieu Willig3
1Department of Anesthesiology, Traumatology and Critical Care, Hôpital Nord, Aix-Marseille Université, Marseille, France. gary.duclos@ap-hm.fr.

Background:
In severe trauma 30% of the patients develop a trauma-induced coagulopathy (TIC), which is associated with higher mortality, massive transfusion and prolonged intensive care stay. Conventional coagulation assays present limitations to detect TIC, primarily due to delayed turnaround time. To enhance early management of TIC viscoelastic tests have been included into guidelines as a standard of care. The Quantra device, based on sonorheometry analysis, offers a rapid bedside assessment of coagulation but lacks validation in a trauma population. The aim of this study was to validate Quantra to detect TIC compared with standard blood coagulation test in severe trauma patients.
Methods:
We performed a multicenter analysis of prospectively collected data (January 1, 2022-December 31, 2024) across four level-1 trauma centers. Trauma patients > 16 years underwent simultaneous Quantra and standard laboratory testing at hospital admission. Diagnostic performance for prespecified thresholds-activated partial thromboplastin time (aPTT) ratio > 1.5, prothrombin time ratio (PTr) > 1.5, fibrinogen ≤ 1.5 g/L, and platelet concentration ≤ 50, ≤ 100, and ≤ 150 G/L-was assessed by receiver operating characteristic curves in a derivation cohort, with Youden-optimized cutoffs applied to an external validation cohort to determine their specific positive and negative predictive values.
Results:
The derivation and validation cohorts included 285 and 219 patients, respectively. In the derivation cohort, the areas under the curve (AUCs) were 0.91 [0.84-0.98] for clot time to predict an aPTT ratio > 1.5 with a best cutoff of 144.5s; 0.82 [0.75-0.90] for clot stiffness to predict a PTr > 1.5 (best cutoff 15.4hPa); 0.87 [0.81-0.93] for fibrinogen contribution to clot stiffness to predict a fibrinogen concentration < 1.5g/L (best cutoff 1.1hPa); 0.90 [0.84-0.95] for platelet contribution to clot stiffness to predict a platelets count ≤ 100G/L (best cutoff 12.4hPa). In the validation cohort, positive predictive and negative predictive values for best cutoffs were 0.67 [0.50-0.80] and 1.00 [0.98-1.00] for clot time, 0.50 [0.39-0.61] and 0.88 [0.80-0.93] for clot stiffness, 0.58 [0.44-0.70] and 0.91 [0.85-0.95] for fibrinogen contribution to clot stiffness, 0.13 [0.24-0.99] and 0.99 [0.96-1.00] for platelets contribution to clot stiffness.
Conclusion:
Early Quantra analysis seems to provide rapid and reliable exclusion of TIC. Prospective investigations remain required to determine usefulness in TIC management.

Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention