Related Experiment Video
Updated: Apr 18, 2026


Detection of Residual Donor Erythroid Progenitor Cells after Hematopoietic Stem Cell Transplantation for Patients with Hemoglobinopathies
Published on: September 6, 2017
Pernicious Anemia Resulting in Intramedullary Hemolysis, Masking Underlying Polycythemia Vera and Mild
Amanda Rohner1, Annatina Sarah Schnegg-Kaufmann2, Yara Banz3,4
1Department of General Internal Medicine, Inselspital, Bern University Hospital, University of Bern, Bern, Switzerland, unibe.ch.

Background:
Vitamin B12 deficiency can cause severe intramedullary hemolysis and cytopenias. Myeloproliferative neoplasms (MPNs), particularly polycythemia vera (PV), are typically characterized by hyperproliferation but may remain undetected when masked by concomitant deficiencies.
Case Presentation:
A 48-year-old woman presented with fatigue, weight loss, and pancytopenia. Laboratory tests showed severe macrocytic anemia, hemolysis, and markedly reduced vitamin B12 levels. Gastroscopy and antibody testing confirmed autoimmune atrophic gastritis with pernicious anemia. Bone marrow biopsy revealed hypercellularity, panmyelosis, and myelofibrosis (MF-2), initially interpreted as reactive. After vitamin B12 supplementation, cytopenias resolved; however, follow-up demonstrated polycythemia, leukocytosis, and thrombocytosis. Molecular analysis identified a JAK2 V617F mutation (variant allele fraction 40%), confirming PV with progression toward myelofibrosis. The patient was treated with phlebotomy, low-dose aspirin, and hydroxyurea, alongside continued vitamin B12 replacement. In addition, mild alpha-thalassemia was diagnosed in the course of an increasingly microcytic hypochromic blood count.
Conclusion:
Severe vitamin B12 deficiency may mask an underlying MPN, as well as other hematologic disorders like alpha-thalassemia. Close follow-up after hematologic recovery is essential to avoid delayed diagnosis of coexisting hematologic malignancies and disorders. This case presents a combination of complex and extremely rare hematological scenarios, where various hematological disorders exert conflicting influences on red blood cell indices, making diagnosis challenging.
Insights
Severe vitamin B12 deficiency can mask myeloproliferative neoplasms (MPNs) and alpha-thalassemia. Prompt diagnosis and monitoring are crucial for managing these complex hematologic disorders and ensuring optimal patient outcomes.
Area of Science:
- Hematology
- Oncology
- Internal Medicine
Background:
- Vitamin B12 deficiency can cause hemolysis and cytopenias.
- Myeloproliferative neoplasms (MPNs) may be masked by deficiencies.
- Polycythemia vera (PV) is a type of MPN.
Purpose of the Study:
- To present a case where vitamin B12 deficiency masked an underlying MPN.
- To highlight the diagnostic challenges posed by coexisting hematologic disorders.
- To emphasize the importance of follow-up after treating deficiencies.
Main Methods:
- Case report of a 48-year-old woman with fatigue and pancytopenia.
- Laboratory tests including vitamin B12 levels, hemolysis markers, and bone marrow biopsy.
- Molecular analysis for JAK2 V617F mutation.
- Diagnosis of autoimmune atrophic gastritis, pernicious anemia, PV, myelofibrosis, and alpha-thalassemia.
Main Results:
- Initial presentation of severe vitamin B12 deficiency with anemia, hemolysis, and pancytopenia.
- Resolution of cytopenias after vitamin B12 supplementation.
- Subsequent development of polycythemia, leukocytosis, thrombocytosis, and myelofibrosis.
- Confirmation of PV with JAK2 V617F mutation and progression to myelofibrosis.
- Co-diagnosis of mild alpha-thalassemia.
Conclusions:
- Severe vitamin B12 deficiency can mask underlying MPNs and other hematologic disorders like alpha-thalassemia.
- Close follow-up after hematologic recovery is essential for diagnosing coexisting conditions.
- This case illustrates complex hematologic scenarios with conflicting influences on red blood cell indices, complicating diagnosis.
More Related Videos
 07:24
A Precision Medicine Tool for Measurement and Monitoring of Hemoglobin S in Sickle Cell Disease Patients Receiving Transfusion Therapy
 05:23
Continuous Manual Exchange Transfusion for Patients with Sickle Cell Disease: An Efficient Method to Avoid Iron Overload
Published on: March 14, 2017
Related Concept Videos
 01:27
Disorders of Erythrocytes
Erythrocyte disorders can be broadly categorized into two main types: anemic and polycythemic conditions.
A low oxygen-carrying capacity of the blood due to the loss, lower production, or destruction of erythrocytes is termed anemia. Hemorrhagic anemia, for example, occurs when bleeding from an external wound or internal ulcer reduces erythrocyte counts.
On the other...
 01:14
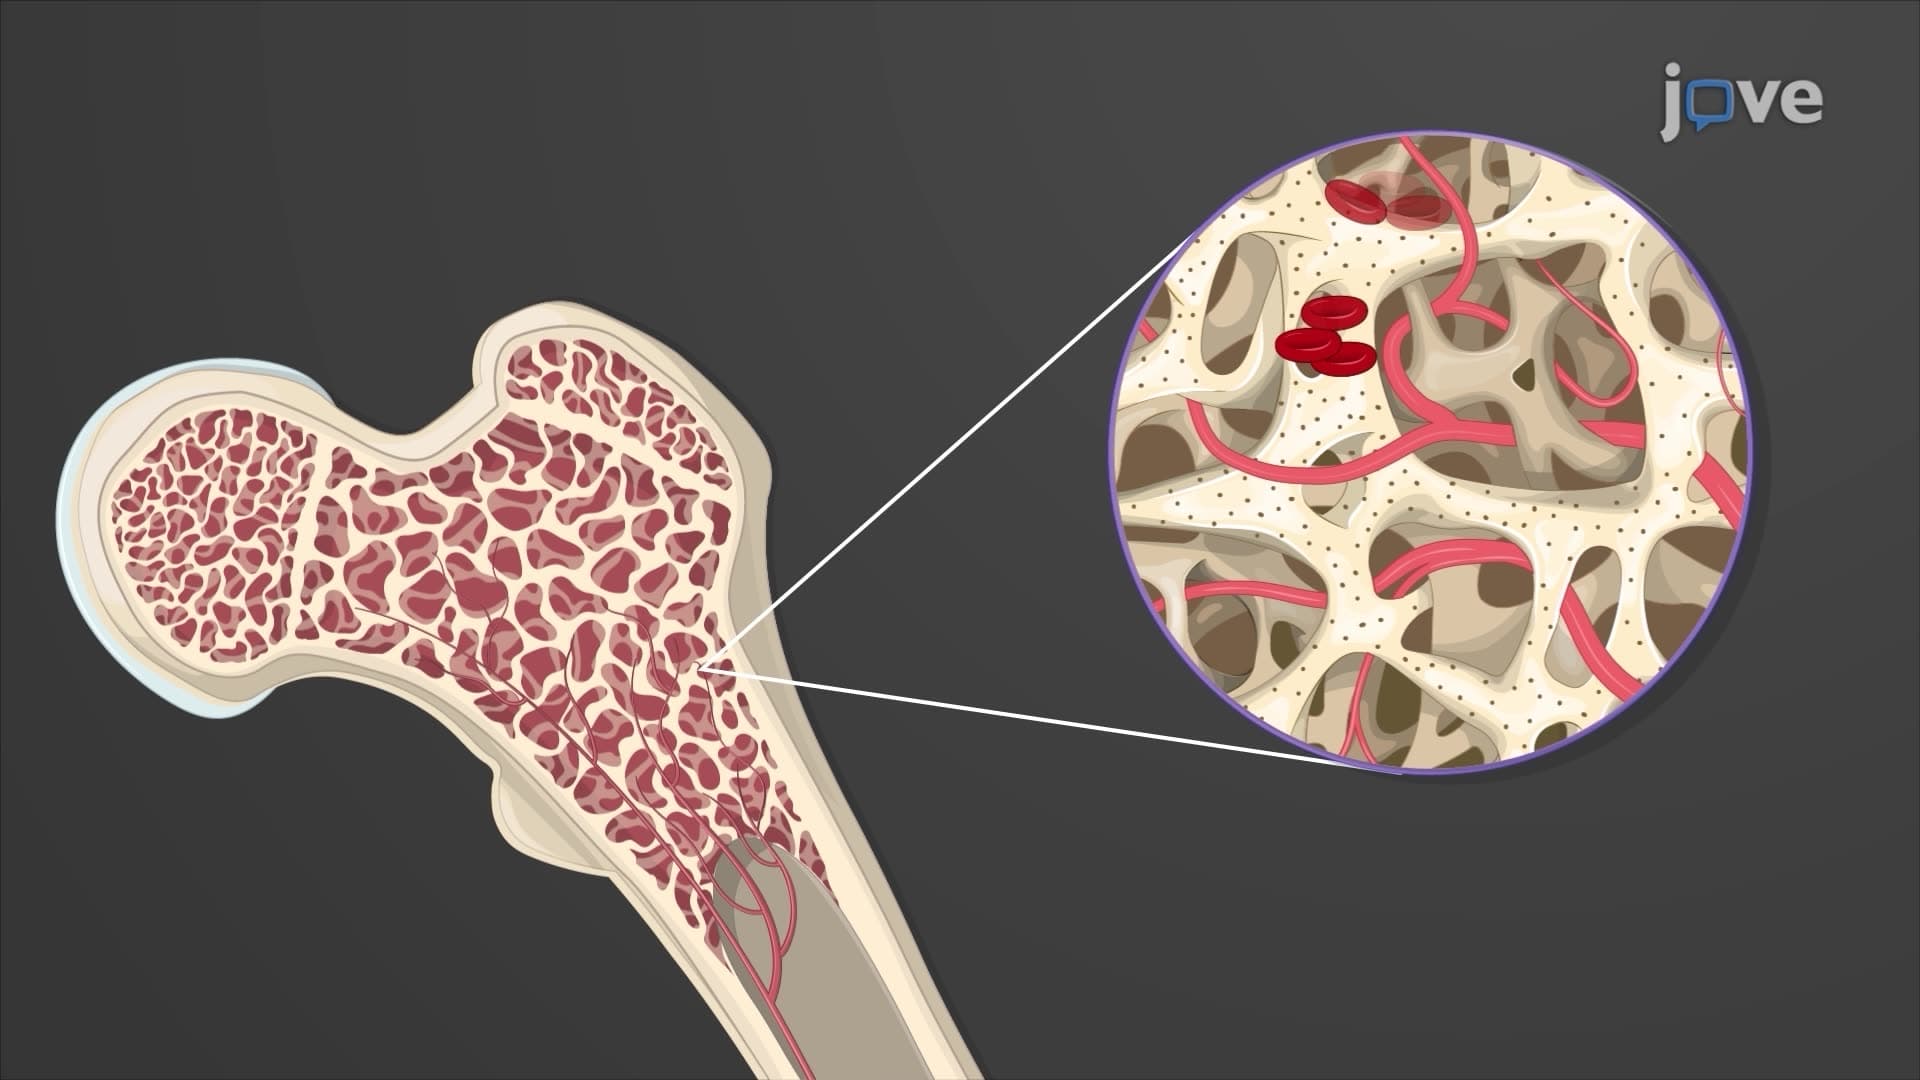
Erythropoiesis
 01:24
Disorders of Hemostasis
Thromboembolic Disorders
Two factors primarily cause thromboembolic conditions.
 01:22
Lifecycle of Erythrocytes
The resident phagocytic macrophages deal with these damaged cells by engulfing them and separating their globin and heme groups....
 01:24
Factors Affecting Erythropoiesis
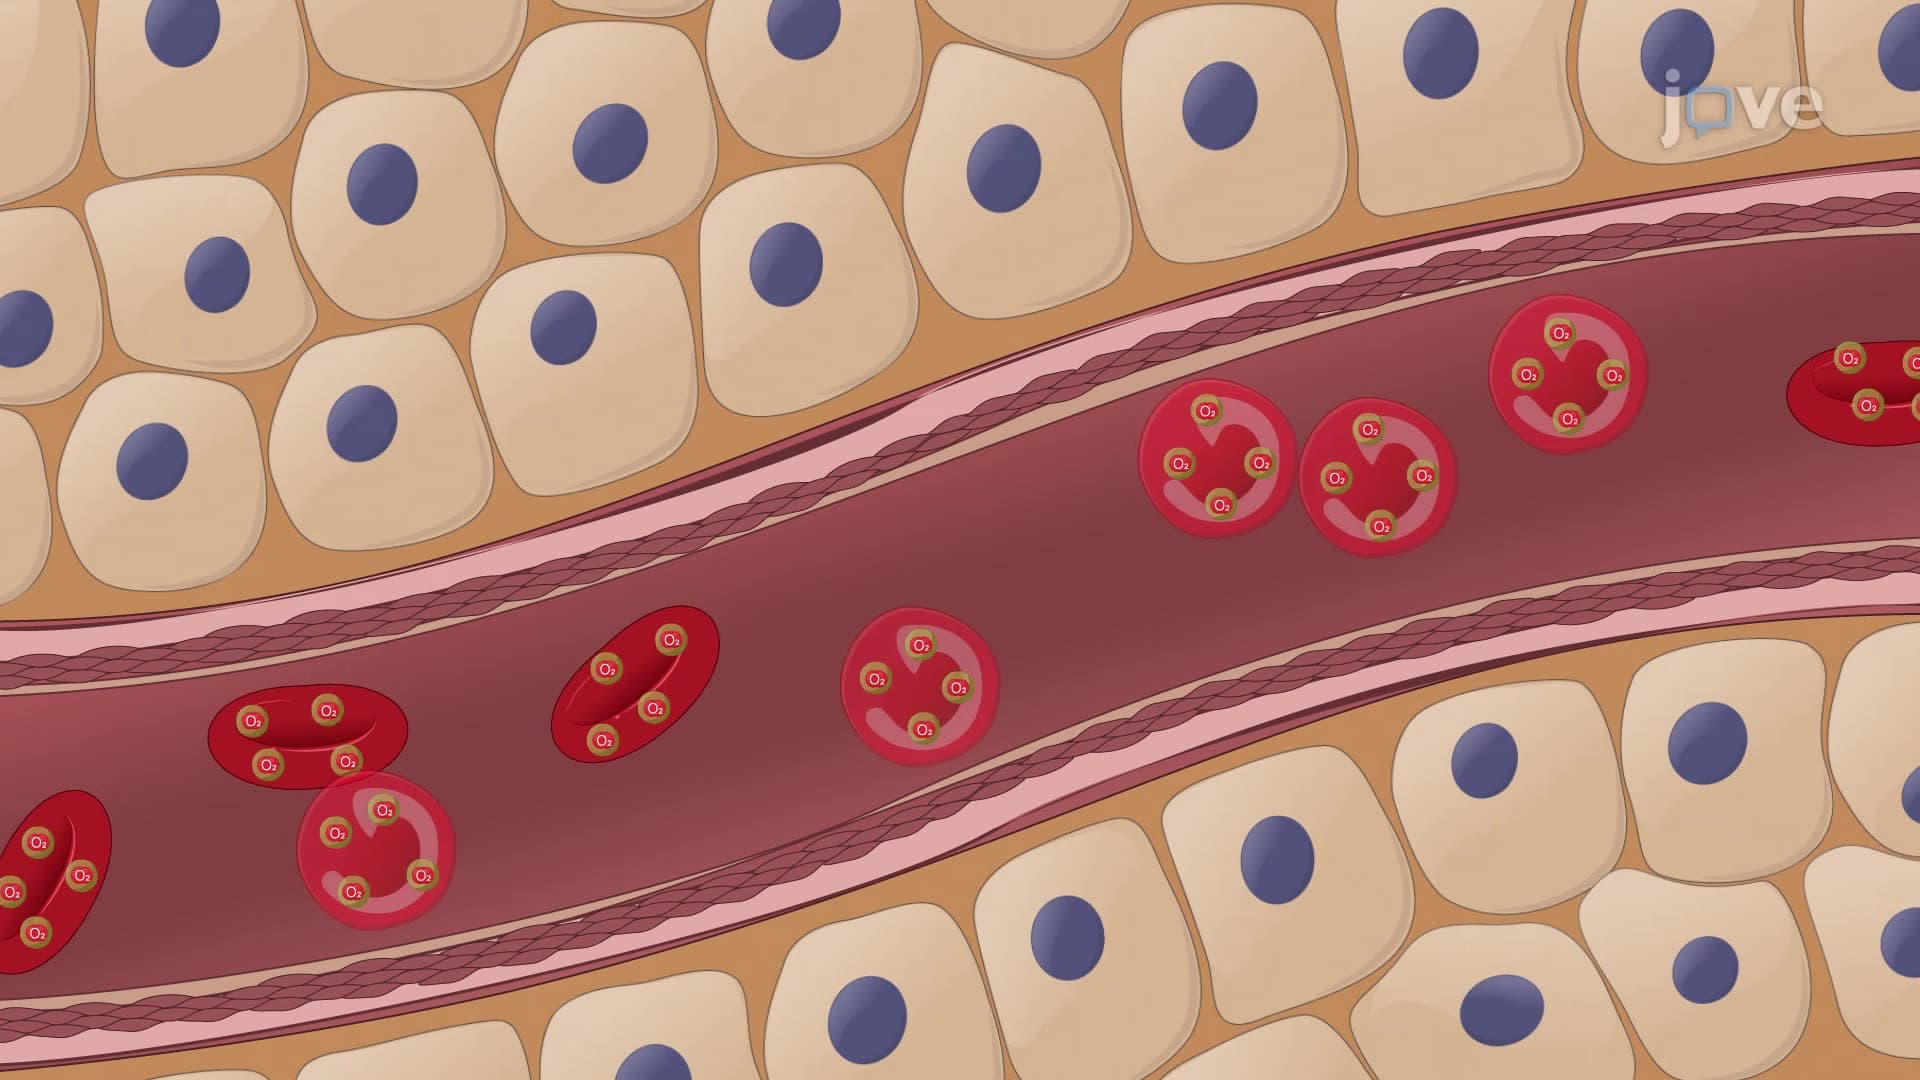
Several factors influence the erythrocyte production rate, with tissue oxygen level being among the most critical. Intense exercise or high altitudes can cause tissue hypoxia, which triggers the kidneys to release more erythropoietin (EPO) into the bloodstream.
EPO then...
 01:20
Inborn Errors of Metabolism