Related Experiment Video
Updated: Apr 19, 2026
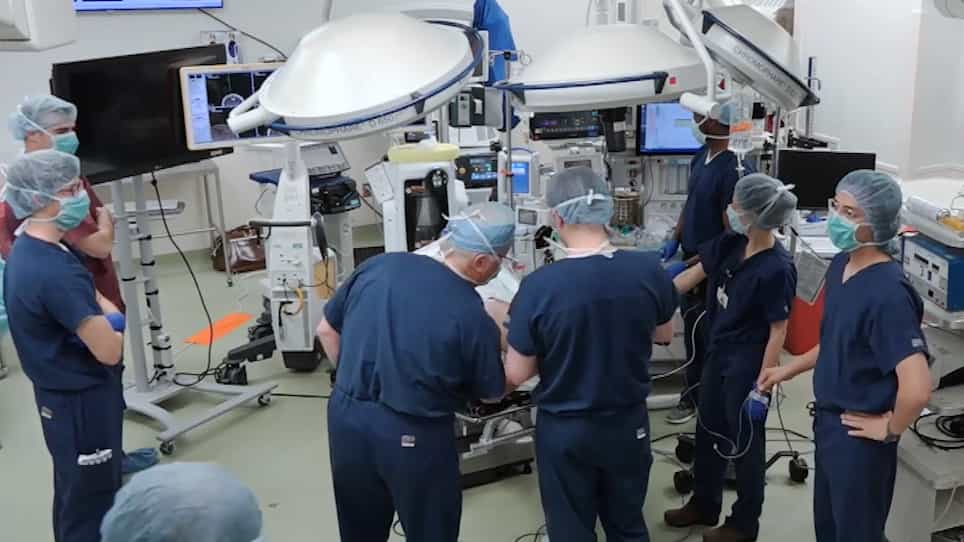
Translational Brain Mapping at the University of Rochester Medical Center: Preserving the Mind Through Personalized Brain Mapping
Published on: August 12, 2019
Awake versus general anesthesia mapping in adult glioma resection: A systematic review of functional outcomes at ≥12
Eric M Kunz1, Ivelina P Kioutchoukova2, Devon T Foster1
1Herbert Wertheim College of Medicine, Florida International University, Miami, FL, USA.

Background:
Maximizing resection while preserving function is vital in adult glioma surgery, especially in the eloquent cortex. We examined how intraoperative functional mapping-performed during awake craniotomy or under anesthesia-relates to long-term neurological, functional, and neurocognitive outcomes beyond the immediate postoperative period.
Methods:
Data sources were MEDLINE (PubMed), Embase, and Cochrane CENTRAL (January 1, 1990 to August 1, 2025). Eligibility criteria included original clinical studies of adult supratentorial glioma resections that (1) used intraoperative mapping, (2) compared ≥2 anesthetic approaches, and (3) reported neurological, functional (i.e., Karnofsky Performance Status), and/or cognitive outcomes at ≥12 weeks. Additionally, studies were selected based on the anesthetic paradigm, including some that compared awake mapping with resections under GA without equivalent mapping. Exclusions were reviews, case reports, conference abstracts without a peer-reviewed full text, non-English, inaccessible full text, studies without mapping, or without a comparator. Two reviewers independently screened and extracted data with consensus adjudication. Risk of bias was assessed using the ROBINS-I tool. This review was not prospectively registered, and it did not receive external funding.
Results:
Of 655 records identified, 464 were screened, 109 underwent full-text review, and 10 studies met inclusion criteria (total n = 1,562; designs: 1 prospective, 1 retrospective case series, 4 retrospective comparatives, 2 matched case-controls, 2 propensity-matched cohorts). Nine of the 10 included studies were retrospective (including matched and propensity-matched cohorts), which limits causal inference and increases risk of bias and confounding. Notably, functional outcomes beyond 3 months post-operatively were sparse; only 4 studies reported data at ≥6 months. Propensity-matched analyses suggested awake approaches may reduce late (≥3-6 months) neurological deficits and, in selected populations, improve overall and progression-free survival relative to asleep resections. At the same time, other controlled cohorts reported comparable extents of resection across paradigms. Sparse and inconsistent evidence suggested the preservation of higher-order cognition and performance status after awake mapping; however, cognitive endpoints, test batteries, and time points were heterogeneous, and patient-reported outcomes were underreported. Comparative data isolating specific anesthetic regimens and their contribution to durable outcomes were sparse.
Conclusions:
In adults undergoing glioma resection with intraoperative mapping, durable neurologic and functional outcomes at 12 weeks are possible with both awake and general anesthesia. However, evidence is limited and varied. Studies show awake procedures may lead to fewer late neurologic deficits and better survival in some cases, but heterogeneity and confounding factors prevent clear conclusions about long-term neurocognitive benefits of specific anesthetic strategies.

Related Concept Videos
 01:22
Stages of General Anesthesia
 01:24
General Anesthesia: Overview
General anesthesia induces unconsciousness in the whole body, while the others target specific areas or sensations. It is administered to minimize adverse effects, maintain...